Related Experiment Video
Updated: Apr 3, 2026

Multiplexed Fluorescent Immunohistochemical Staining of Four Endometrial Immune Cell Types in Recurrent Miscarriage
Published on: August 4, 2021
Defining safe criteria to diagnose miscarriage: prospective observational multicentre study
Jessica Preisler1, Julia Kopeika2, Laure Ismail3
1Queen Charlotte's and Chelsea Hospital, Imperial College, London W12 0HS, UK.

Objectives:
To validate recent guidance changes by establishing the performance of cut-off values for embryo crown-rump length and mean gestational sac diameter to diagnose miscarriage with high levels of certainty. Secondary aims were to examine the influence of gestational age on interpretation of mean gestational sac diameter and crown-rump length values, determine the optimal intervals between scans and findings on repeat scans that definitively diagnose pregnancy failure.)
Design:
Prospective multicentre observational trial.
Setting:
Seven hospital based early pregnancy assessment units in the United Kingdom.
Participants:
2845 women with intrauterine pregnancies of unknown viability included if transvaginal ultrasonography showed an intrauterine pregnancy of uncertain viability. In three hospitals this was initially defined as an empty gestational sac <20 mm mean diameter with or without a visible yolk sac but no embryo, or an embryo with crown-rump length <6 mm with no heartbeat. Following amended guidance in December 2011 this definition changed to a gestational sac size <25 mm or embryo crown-rump length <7 mm. At one unit the definition was extended throughout to include a mean gestational sac diameter <30 mm or embryo crown-rump length <8 mm.
Main Outcome Measures:
Mean gestational sac diameter, crown-rump length, and presence or absence of embryo heart activity at initial and repeat transvaginal ultrasonography around 7-14 days later. The final outcome was pregnancy viability at 11-14 weeks' gestation.
Results:
The following indicated a miscarriage at initial scan: mean gestational sac diameter ≥ 25 mm with an empty sac (364/364 specificity: 100%, 95% confidence interval 99.0% to 100%), embryo with crown-rump length ≥ 7 mm without visible embryo heart activity (110/110 specificity: 100%, 96.7% to 100%), mean gestational sac diameter ≥ 18 mm for gestational sacs without an embryo presenting after 70 days' gestation (907/907 specificity: 100%, 99.6% to 100%), embryo with crown-rump length ≥ 3 mm without visible heart activity presenting after 70 days' gestation (87/87 specificity: 100%, 95.8% to 100%). The following were indicative of miscarriage at a repeat scan: initial scan and repeat scan after seven days or more showing an embryo without visible heart activity (103/103 specificity: 100%, 96.5% to 100%), pregnancies without an embryo and mean gestational sac diameter <12 mm where the mean diameter has not doubled after 14 days or more (478/478 specificity: 100%, 99.2% to 100%), pregnancies without an embryo and mean gestational sac diameter ≥ 12 mm showing no embryo heartbeat after seven days or more (150/150 specificity: 100%, 97.6% to 100%).
Conclusions:
Recently changed cut-off values of gestational sac and embryo size defining miscarriage are appropriate and not too conservative but do not take into account gestational age. Guidance on timing between scans and expected findings on repeat scans are still too liberal. Protocols for miscarriage diagnosis should be reviewed to account for this evidence to avoid misdiagnosis and the risk of terminating viable pregnancies.
More Related Videos
 07:46
Author Spotlight: Advancing Reproductive Immunology with a Protocol for the Quantitative Evaluation of Endometrial Immune Cells
Published on: October 13, 2023
 07:04
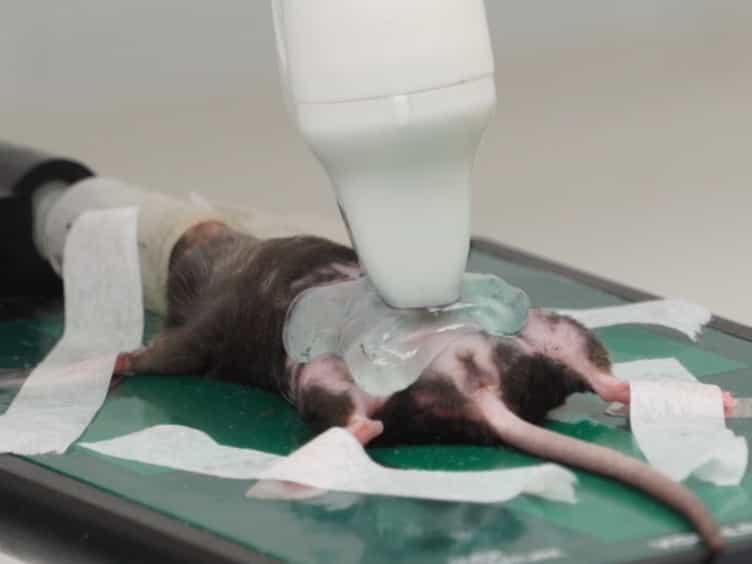
A Novel Use of Three-dimensional High-frequency Ultrasonography for Early Pregnancy Characterization in the Mouse
Published on: October 24, 2017
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies