Computerized respiratory sounds: a comparison between patients with stable and exacerbated COPD

Cristina Jácome1,2, Ana Oliveira2, Alda Marques2,3
1Research Centre in Physical Activity, Health and Leisure (CIAFEL), Faculty of Sports, University of Porto, Portugal.

Introduction:
Diagnosis of acute exacerbations of chronic obstructive pulmonary disease (AECOPD) is often challenging as it relies on patients' clinical presentation. Computerized respiratory sounds (CRS), namely crackles and wheezes, may have the potential to contribute for the objective diagnosis/monitoring of an AECOPD.
Objectives:
This study explored if CRS differ during stable and exacerbation periods in patients with COPD.
Methods:
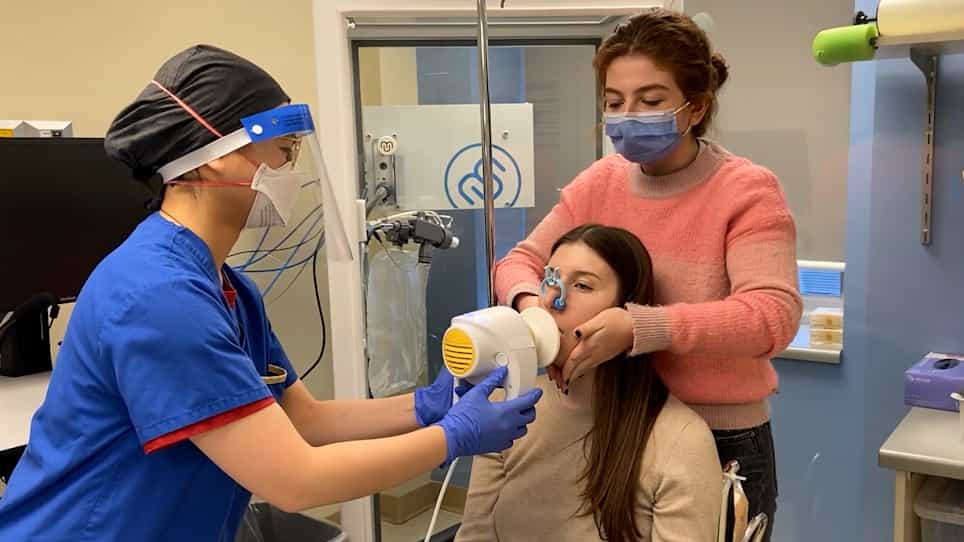
13 patients with stable COPD and 14 with AECOPD were enrolled. CRS were recorded simultaneously at trachea, anterior, lateral and posterior chest locations using seven stethoscopes. Airflow (0.4-0.6l/s) was recorded with a pneumotachograph. Breathing phases were detected using airflow signals; crackles and wheezes with validated algorithms.
Results:
At trachea, anterior and lateral chest, no significant differences were found between the two groups in the number of inspiratory/expiratory crackles or inspiratory wheeze occupation rate. At posterior chest, the number of crackles (median 2.97-3.17 vs. 0.83-1.2, P < 0.001) and wheeze occupation rate (median 3.28%-3.8% vs. 1.12%-1.77%, P = 0.014-0.016) during both inspiration and expiration were significantly higher in patients with AECOPD than in stable patients. During expiration, wheeze occupation rate was also significantly higher in patients with AECOPD at trachea (median 3.12% vs. 0.79%, P < 0.001) and anterior chest (median 3.55% vs. 1.28%, P < 0.001).
Conclusion:
Crackles and wheezes are more frequent in patients with AECOPD than in stable patients, particularly at posterior chest. These findings suggest that these CRS can contribute to the objective diagnosis/monitoring of AECOPD, which is especially valuable considering that they can be obtained by integrating computerized techniques with pulmonary auscultation, a noninvasive method that is a component of patients' physical examination.
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:28
Physical Assessment of the Respiratory Tract IV: Auscultation
Breath Sounds
Breath sounds are categorized into vesicular, bronchovesicular, and bronchial.
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities: