Related Experiment Video
Updated: Apr 3, 2026


Author Spotlight: Assessment of Cardiac Output Calculation by Thermodilution in Pigs for Effective Perfusion Flow During EVLP
Published on: June 28, 2024
Addressing Assumptions for the Use of Non-invasive Cardiac Output Measurement Techniques During Exercise in COPD
Hélène Perrault1,2, Ruddy Richard2,3, Sophia Kapchinsky2,4
1a Faculty of Health Sciences , University of Ottawa , Ottawa Ontario , Canada.

Abstract:
The multifactorial functional limitation of COPD increasingly demonstrates the need for an integrated circulatory assessment. In this study cardiac output (Qc) derived from non-inert (CO2-RB), inert (N2O-RB) gas rebreathing approaches and bioimpedance were compared to examine the limitations of currently available non-invasive techniques for exercise Qc determination in patients with chronic lung disease. Thirteen COPD patients (GOLD II-III) completed three constant cycling bouts at 20, 35, and 50% of peak work on two occasions to assess Qc with bioimpedance as well as using CO2-RB and N2O-RB for all exercise tests. Results showed significantly lower Qc using the N2O-RB or end-tidal CO2-derived Qc compared to the PaCO2-derived CO2-RB or the bioimpedance at rest and for all exercise intensities. End-tidal CO2-derived values are however not statistically different from those obtained using inert-gas rebreathing. This study show that in COPD patients, CO2-rebreathing Qc values obtained using PaCO2 contents which account for any gas exchange impairment or inadequate gas mixing are similar to those obtained using thoracic bioimpedance. Alternately, the lower values for N2O rebreathing derived Qc indicates the inability of this technique to account for gas exchange impairment in the computation of Qc. These findings indicate that the choice of a gas rebreathing technique to measure Qc in patients must be dictated by the ability to include in the derived computations a correction for either gas exchange inadequacies and/or a vascular shunt.
More Related Videos
 04:20
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
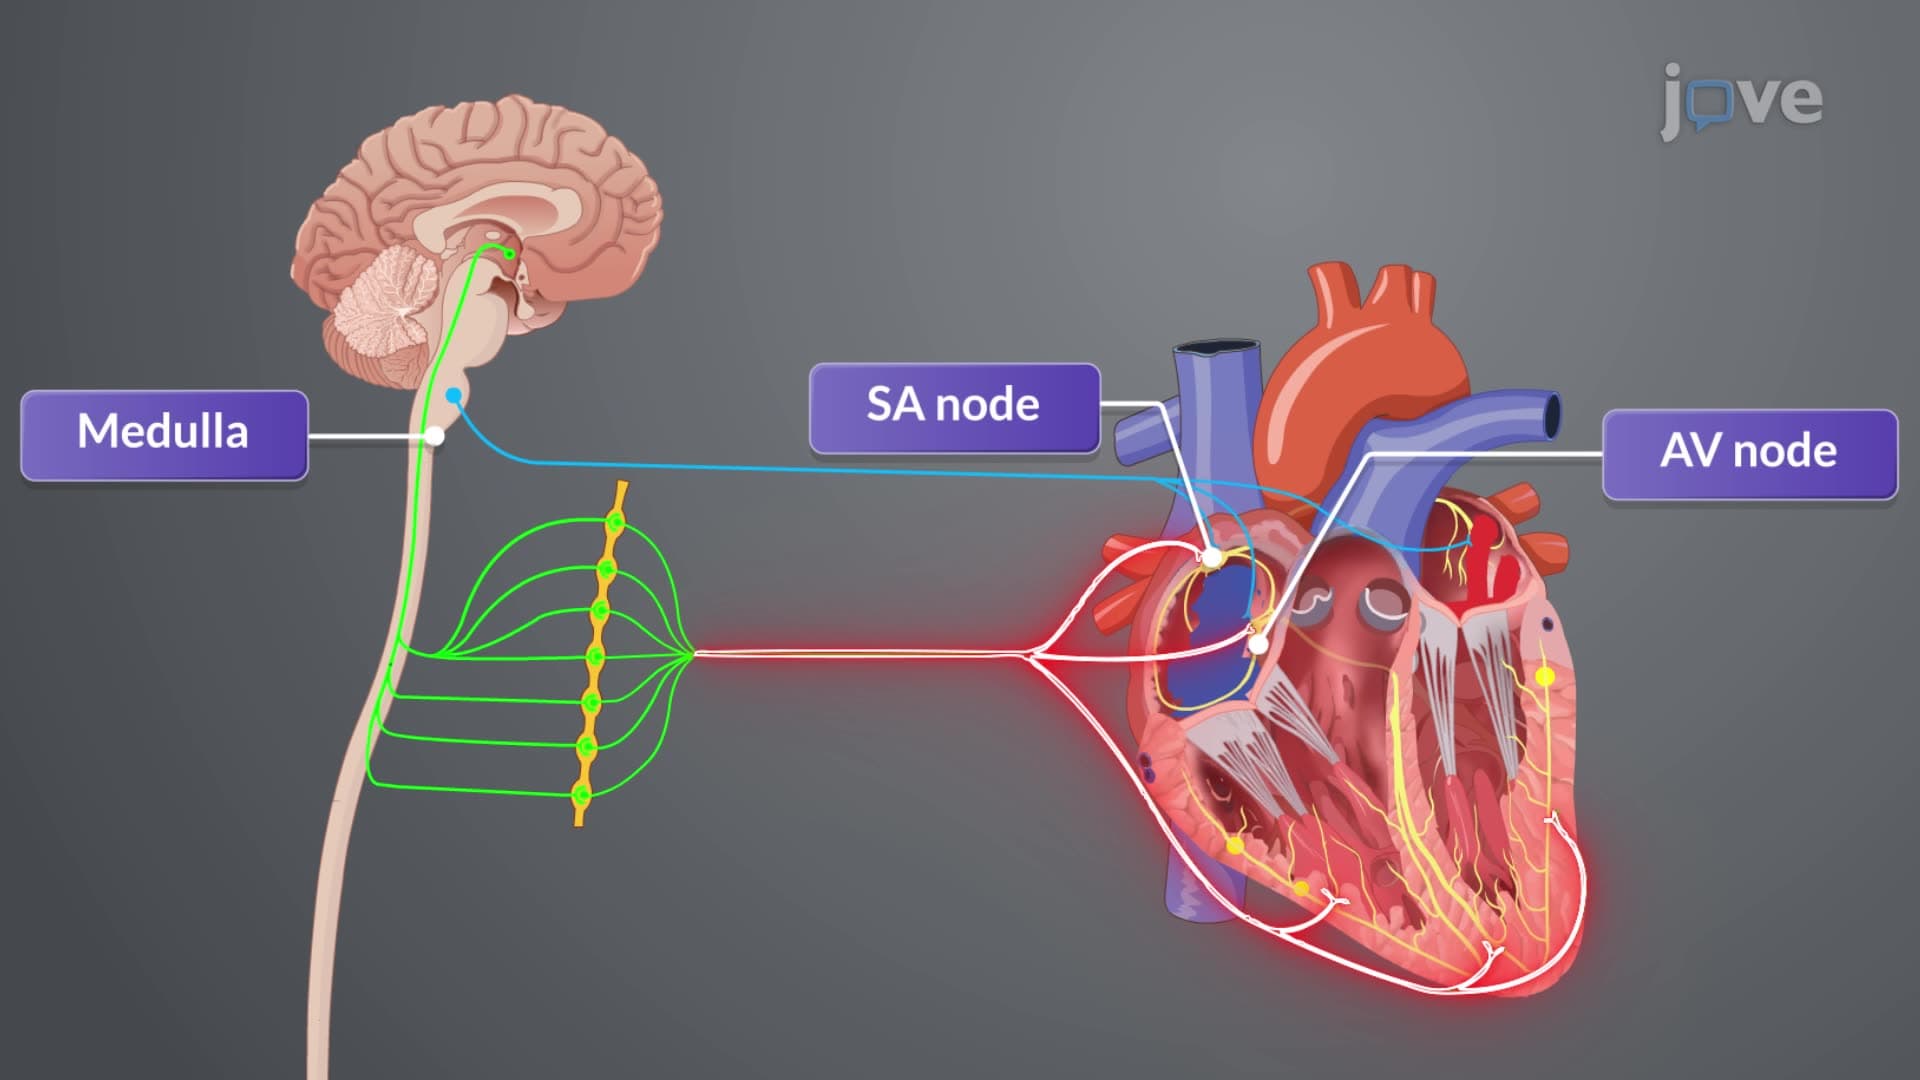
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...