Predicting fluid responsiveness in 100 critically ill children: the effect of baseline contractility
Related Experiment Video
Updated: Apr 2, 2026
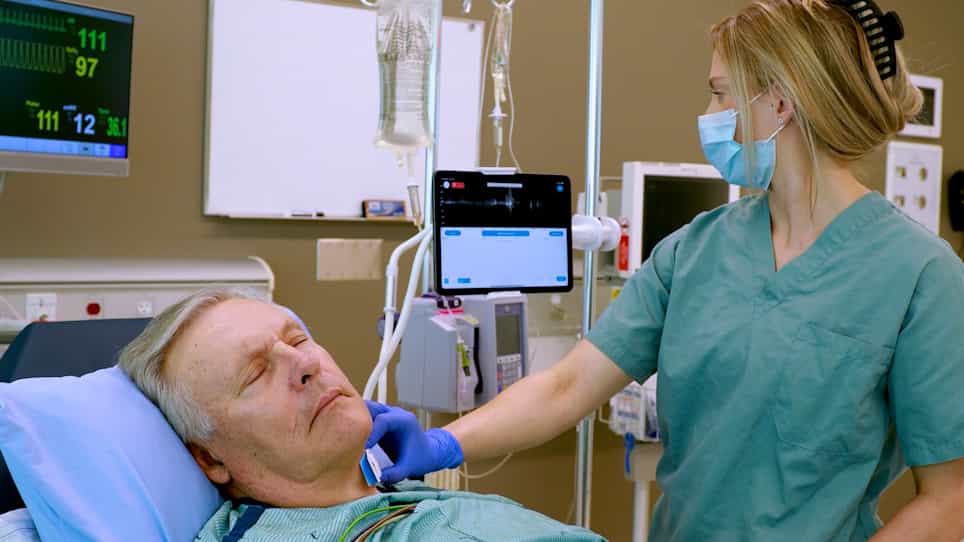
Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Rohit Saxena1, Andrew Durward1, Sarah Steeley1
1Paediatric Intensive Care Unit, Evelina Children's Hospital, Guy's and St Thomas' NHS Foundation Trust, Westminster Bridge Road, London, SE1 7EH, UK.

Insights
Predicting fluid responsiveness in critically ill children is challenging. Baseline heart contractility significantly impacts stroke volume response to fluid boluses, suggesting its importance for personalized fluid management.
Area of Science:
- Pediatric critical care medicine
- Hemodynamic monitoring
- Fluid resuscitation
Background:
- Fluid overload is a significant risk factor for adverse outcomes in intensive care settings.
- Tailoring fluid administration to patients likely to increase stroke volume is crucial for improving outcomes.
- Accurate prediction of fluid responsiveness is essential for optimizing hemodynamic management in critically ill children.
Purpose of the Study:
- To evaluate the predictive ability of established and novel hemodynamic variables for fluid responsiveness in pediatric patients.
- To assess the impact of baseline cardiac contractility on stroke volume increase after fluid bolus administration.
- To determine if incorporating contractility improves the prediction of fluid responsiveness in critically ill children.
Main Methods:
- Assessed 142 fluid loading episodes (10 ml/kg crystalloid) in 100 critically ill, ventilated children.
- Measured eight advanced hemodynamic variables using two commercial devices.
- Quantified systemic ventricular contractility as the maximum rate of systolic arterial pressure rise.
Main Results:
- Overall predictive ability of fluid responsiveness was poor; volumetric variables outperformed dynamic variables.
- Total end-diastolic volume index was the best predictor but showed inconsistent increases with fluid loading.
- Baseline contractility significantly influenced fluid response; low contractility required larger end-diastolic volume increases.
Conclusions:
- Current methods for predicting fluid responsiveness in pediatric intensive care have limited accuracy.
- Incorporating baseline cardiac contractility into predictive models may enhance the accuracy of fluid responsiveness assessment.
- Personalized fluid management strategies considering contractility are needed for critically ill children.
Purpose:
Fluid overload is a risk factor for poor outcome in intensive care; thus volume loading should be tailored towards patients who are likely to increase stroke volume. We aimed to evaluate the paediatric predictive ability (stroke volume increase of at least 15 % after fluid bolus) of novel and established volumetric and dynamic haemodynamic variables, and assess the influence of baseline contractility on response.
Methods:
We assessed 142 volume loading episodes (10 ml/kg crystalloid) in 100 critically ill ventilated children, median (interquartile) weight 10 (5.6-15) kg. Eight advanced haemodynamic variables were assessed using two commercially available devices. Systemic ventricular contractility was measured as the maximum rate of systolic arterial pressure rise.
Results:
Overall, predictive ability was poor, with volumetric variables performing better than dynamic (area under receiver operating characteristic curves ranged from 0.53 to 0.67). The best predictor was total end-diastolic volume index; however, this did not increase in a consistent way with volume loading, with change post volume being weakly related to baseline values (r = -0.19, p = 0.02). A multivariable model quantified the importance of contractility in stroke volume response. Children with high baseline contractility (≥75th centile) typically achieved a positive stroke volume response when end-diastolic volume values changed by 10-15 ml/m(2.6), whereas patients with low contractility (≤25th centile) typically required end-diastolic volume increases of 35-40 ml/m(2.6).
Conclusions:
Current paediatric predictors of volume response perform poorly; prediction may be improved if baseline contractility is taken into account.

Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:22
Acute Kidney Injury VI: Nursing Management
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:30
Heart Failure VII: Nursing Interventions