Related Experiment Video
Updated: Apr 1, 2026
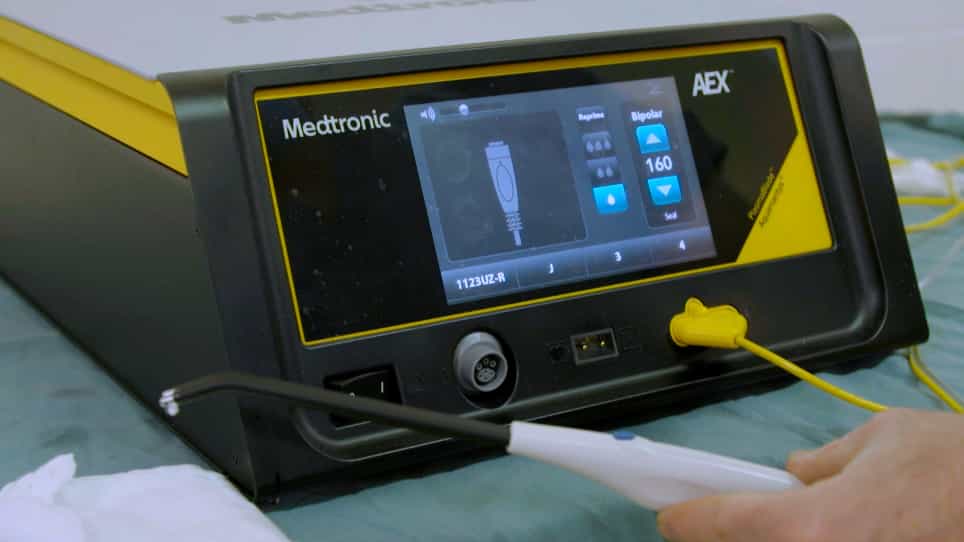

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Pediatric blunt abdominal trauma: current management
1aDepartment of Surgery and Level 1 Pediatric Trauma Center, Phoenix Children's Hospital bUniversity of Arizona College of Medicine - Phoenix cMayo Medical School, Phoenix, Arizona, USA.

Insights
Pediatric blunt abdominal injury management now prioritizes hemodynamic status over injury grade. Stable children receive less invasive care, shorter hospital stays, and earlier school return, guided by new evidence-based algorithms.
Area of Science:
- Pediatric Surgery
- Trauma Management
- Evidence-Based Medicine
Background:
- Nonoperative management (NOM) of pediatric blunt abdominal injury has evolved.
- Traditional approaches are being updated with recent clinical findings.
Purpose of the Study:
- To review recent advancements in the nonoperative management of pediatric blunt abdominal trauma.
- To highlight shifts in diagnostic and treatment paradigms.
Main Methods:
- Review of current literature and clinical practice guidelines.
- Analysis of factors influencing treatment decisions in pediatric abdominal injuries.
Main Results:
- Hemodynamic status is now the primary determinant of care, superseding injury grade.
- Stable pediatric patients benefit from reduced hospitalizations and earlier return to school.
- Intensive Care Unit (ICU) admission is reserved for specific high-risk cases, including ongoing bleeding or associated injuries.
- Emerging data identifies risk factors for NOM failure and adjuncts.
- Operative management may offer better outcomes for specific pancreatic injuries.
Conclusions:
- Robust evidence supports a paradigm shift in managing pediatric abdominal injuries.
- New evidence-based algorithms are being implemented for improved patient care and resource utilization.
Purpose Of Review:
Nonoperative management of pediatric blunt abdominal injury has changed significantly in the last few years.
Recent Findings:
Improved resource utilization in the diagnosis of pediatric abdominal injury has been described. Hemodynamic status, rather than grade of injury, now guides care. Stable patients spend less time in the hospital, return to school upon discharge, and are allowed lower hemoglobin levels prior to transfusion. ICUs are reserved for those with recent or ongoing bleeding, previously unstable patients, or children with concomitant injuries necessitating ICU. Risk factors for failure and evidence for adjuncts to nonoperative management are emerging. Operative management of certain pancreatic injuries may have more favorable outcomes than nonoperative management.
Summary:
Sufficient evidence has become available to radically change the management of pediatric abdominal injury, which is being incorporated into new evidence-based management algorithms.

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:28
Urinary Tract Calculi V: Nursing Management
 01:20
Acute Kidney Injury V: Interprofessional Care