Related Experiment Video
Updated: Apr 1, 2026
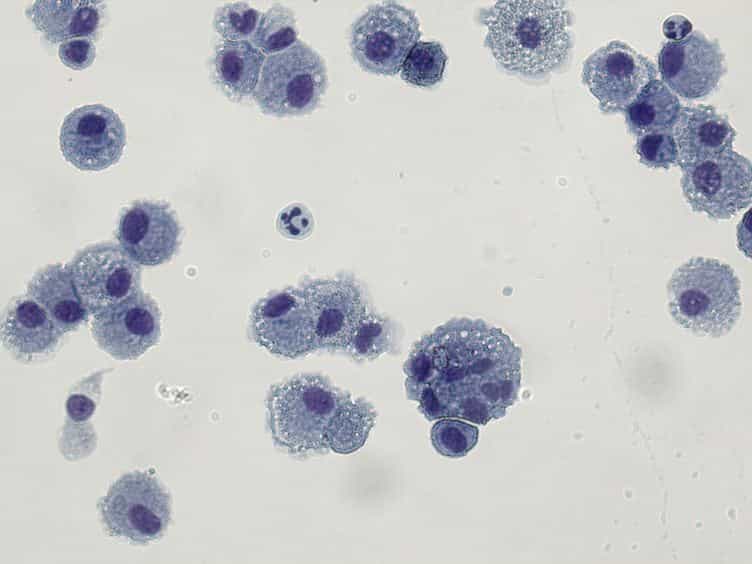
Bronchoalveolar Lavage BAL for Research; Obtaining Adequate Sample Yield
Published on: March 24, 2014
Clinical course and complications following diagnostic bronchoalveolar lavage in critically ill mechanically
R M Schnabel1, K van der Velden2, A Osinski3
1Department of Intensive Care Medicine, Maastricht University Medical Centre+, P. Debyelaan 25, PO Box 5800, 6202 AZ, Maastricht, The Netherlands. r.schnabel@mumc.nl.

Background:
Flexible, fibreoptic bronchoscopy (FFB) and bronchoalveolar lavage (BAL) have been used for diagnostic purposes in critically ill ventilated patients. The additional diagnostic value compared to tracheal aspirations in ventilator-associated pneumonia (VAP) has been questioned. Nevertheless, BAL can provide extra information for the differential diagnosis of respiratory disease and good antibiotic stewardship. These benefits should outweigh potential hazards caused by the invasiveness of this diagnostic technique. The focus of the present study was on the clinical course and complications of patients following BAL procedures up to 24 h.
Methods:
Hundred sixty-four FFB guided BAL procedures for suspected pneumonia were analysed in an observational study. The clinical course of patients was monitored by respiratory and haemodynamic data before BAL, 1 and 24 h after BAL. Complications were defined and registered. Factors associated with complications were analysed by logistic regression.
Clinical Course:
a decrease in average pO2/FiO2 ratio 1 h after BAL from 29 kPa (218 mmHg) to 25 kPa (189 mmHg) (p < 0.05) was observed which fully recovered within 24 h. Respiratory complications: the incidence of procedure related hypo-oxygenation (SaO2 ≤ 88 %) and/or bronchospasm was 9 %; a decrease of >25 % PaO2/FiO2 ratio 1 h after BAL was found in 29 % of patients; no bleeding or pneumothorax were registered. Haemodynamic complications: there were no cases of hypertension and cardiac rhythm disturbances; haemodynamic instability within the first 24 h after BAL was recorded in 22 %; this was correlated with a cardiovascular diagnosis at admission (OR 2.9; 95 % CI 1.2 - 6.7) and the presence of cardiovascular co-morbidity (OR 3.5; 95 % CI 1.5 - 8.3). The incidence of bacteraemia was 7 %. There was no case of procedure related death.
Discussion:
Frequently occurring haemodynamic and respiratory instability but no cases of cardiac rhythm disturbances, bleeding, pneumothorax or procedure related death were attributable to diagnostic FFB and BAL. The procedures should be conducted under careful supervision by experienced physicians. Only a randomized controlled trial that compares diagnostic FFB and BAL with a non-invasive strategy could ultimately establish the safety profile and clinical utility of these procedures in critically ill ventilated patients.
Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:30
Pneumonia III: Complications and Assessment
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:23
Acute Respiratory Failure-IV
 01:17
Pulmonary Cycle: Exhalation
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include: