Related Experiment Video
Updated: Apr 1, 2026


Analyses of Proteinuria, Renal Infiltration of Leukocytes, and Renal Deposition of Proteins in Lupus-prone MRL/lpr Mice
Published on: June 8, 2022
Hydroxychloroquine Blood Levels in Systemic Lupus Erythematosus: Clarifying Dosing Controversies and Improving
Laura Durcan1, William A Clarke1, Laurence S Magder1
1From the Department of Rheumatology, Johns Hopkins University School of Medicine; Department of Pathology, Clinical Chemistry, Johns Hopkins University Hospital, Baltimore; Department of Epidemiology and Public Health, University of Maryland, College Park, Maryland, USA.L. Durcan, MD, Department of Rheumatology, Johns Hopkins University School of Medicine; W.A. Clarke, PhD, Department of Pathology, Clinical Chemistry, Johns Hopkins University Hospital; L.S. Magder, MPH, PhD, Department of Epidemiology and Public Health, University of Maryland; M. Petri, MD, MPH, Department of Rheumatology, Johns Hopkins University School of Medicine.

Objective:
Hydroxychloroquine (HCQ) is used for its effect on systemic lupus erythematosus (SLE) disease activity and longterm benefits. This can be limited by adherence. One way to assess adherence is to measure blood levels. Conflicting data exist regarding blood levels and disease activity. There is disagreement about dosing; rheumatologists recommend weight-based dosing while some other specialists advocate height-based "ideal body weight" dosing.
Methods:
Patients were prescribed HCQ not exceeding 6.5 mg/kg (max 400 mg/day). In hemodialysis, the dose was 200 mg after each session, and in renal insufficiency it was 200 mg/day. Levels were measured at each visit with a therapeutic range of 500-2000 ng/ml. Patients were divided according to baseline blood level. To assess the effect of measurement and counseling on adherence, we compared the proportion of patients with a level of 500 ng/ml or higher based on the number of prior assessments.
Results:
The proportion of patients with HCQ levels in the therapeutic range differed significantly by age, sex, and Vitamin D level. There was a trend toward lower levels with renal failure. Blood levels were similar regardless of height and ideal body weight. Comparing those with undetectable, subtherapeutic, and therapeutic levels, disease activity decreased (SLE Disease Activity Index 2.92, 2.36, and 2.20, p = 0.04 for trend). At first, 56% were therapeutic, and by the third measurement this increased to 80% (p ≤ 0.0001).
Conclusion:
There was a trend toward higher disease activity with lower HCQ levels. Renal failure dosing led to suboptimum levels. We show that weight-based dosing (max 400 mg daily) is appropriate and that height does not appear to influence levels. Measurement, counseling, and repeated testing can increase adherence rates.


Related Concept Videos
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:25
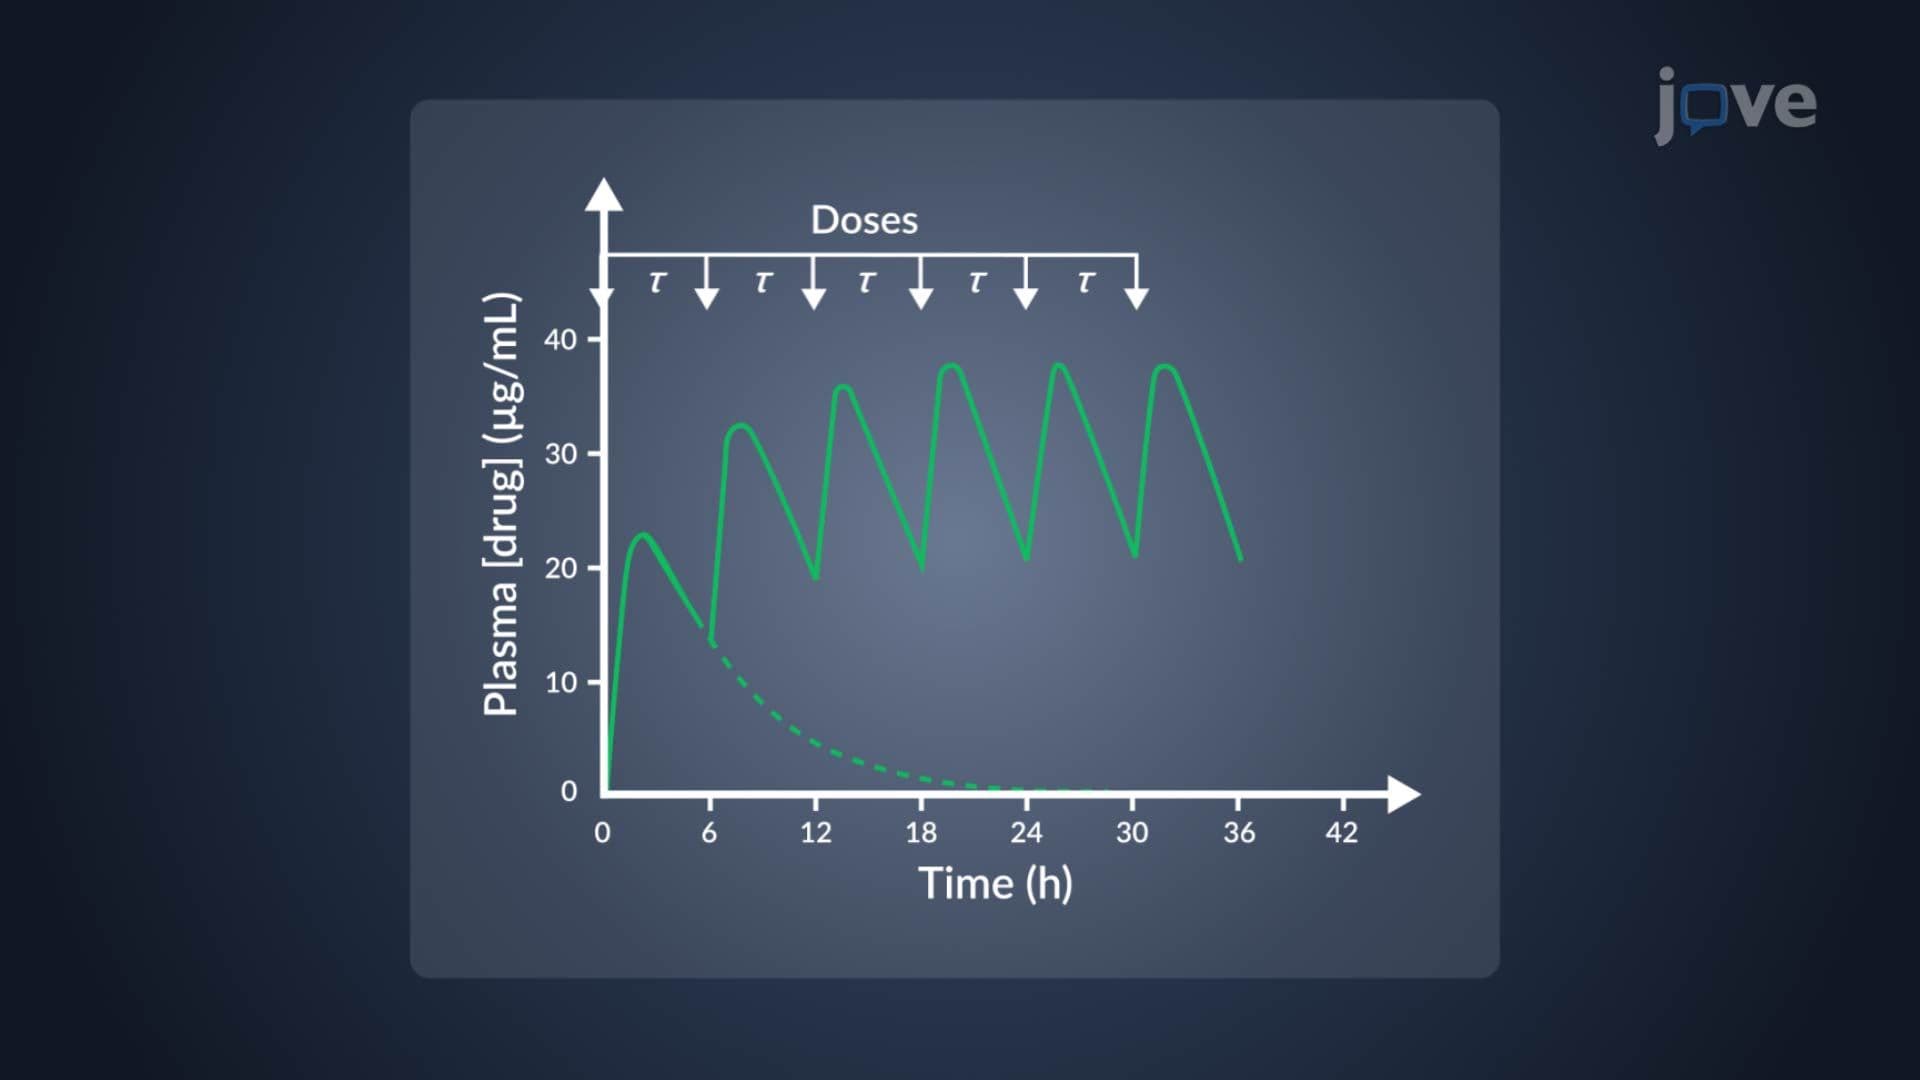
Dosage Regimen: Multiple Oral Dosage
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:25
Blood Studies for Cardiovascular System III: Serum Lipid Profile
Serum lipids are fats and fatty substances in the blood and are crucial for various bodily functions, including energy storage, cellular structure, and hormone production. Serum lipids consist of cholesterol, triglycerides, and phospholipids.
Cholesterol is a soft, fat-like substance found in all body cells. It is crucial for producing hormones, vitamin D, and substances that aid...
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance