Related Experiment Video
Updated: Apr 1, 2026
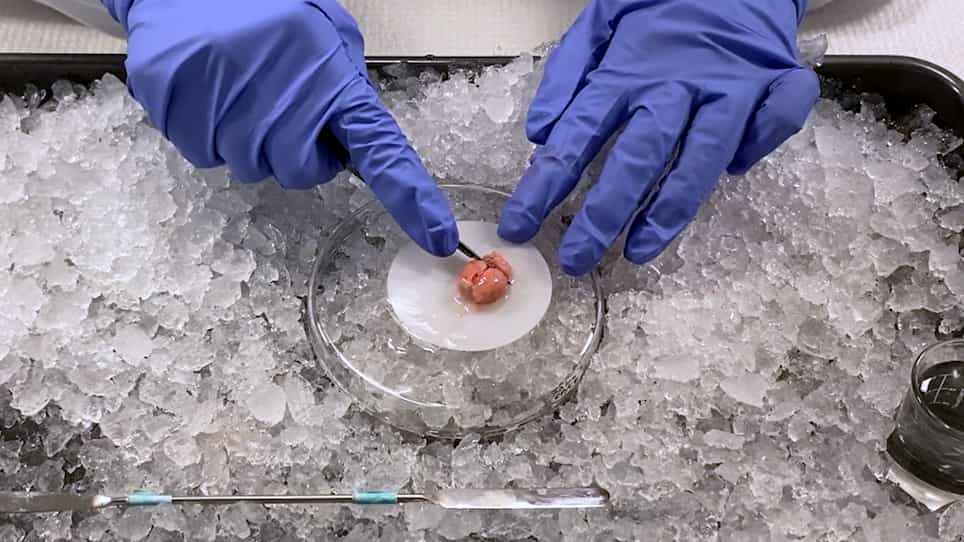

Assessing Changes in Synaptic Plasticity Using an Awake Closed-Head Injury Model of Mild Traumatic Brain Injury
Published on: January 20, 2023
The wrong and wounding road: Paediatric polytrauma admitted to a level 1 trauma intensive care unit over a 5-year
Natasha Naidoo1, David J J Muckart
1Department of Surgery, School of Clinical Medicine, College of Health Sciences, Nelson R Mandela School of Medicine, University of KwaZulu-Natal, Durban, South Africa. emmab@hmpg.co.za.

Insights
Pediatric trauma is frequently caused by motor vehicle collisions, particularly pedestrian-motor vehicle collisions (PMVCs). These injuries lead to significant morbidity and mortality, highlighting the need for improved road safety measures.
Area of Science:
- Pediatric Trauma Care
- Epidemiology of Injury
- Public Health & Safety
Background:
- Childhood injury is a significant cause of preventable morbidity and mortality.
- Epidemiological data on injury mechanisms and outcomes are crucial for developing effective prevention strategies.
Purpose of the Study:
- To assess the causes, severity, morbidity, and mortality of pediatric trauma patients admitted to a level 1 trauma intensive care unit (TICU).
Main Methods:
- A 5-year prospective study (2008-2012) of children (<16 years) admitted to a level 1 TICU.
- Data collected included referral source, injury mechanism, demographics, Injury Severity Score (ISS), anatomical injury distribution, and mortality.
- Analysis of 181 pediatric trauma admissions.
Main Results:
- Pedestrian-motor vehicle collisions (PMVCs) were the leading cause of severe pediatric trauma (58.0%), followed by motor vehicle passenger injuries (21.0%).
- The median Injury Severity Score (ISS) was 25, with 54.1% of patients having an ISS > 25.
- Head injuries were most common (61.9%), and mortality was highest among patients with an ISS > 25 (92% of deaths).
Conclusions:
- Motor vehicle-related injuries, especially PMVCs, are the primary cause of severe pediatric trauma.
- There is an urgent need for enhanced road traffic education and stringent safety measures to reduce the incidence and impact of pediatric trauma.
Background:
Injury in childhood is a major cause of potentially preventable morbidity and mortality. In order to implement effective preventive strategies, epidemiological data on mechanisms of injury and outcome are essential.
Objectives:
To assess the causation, severity of injury, morbidity and mortality of paediatric trauma admitted to a level 1 trauma intensive care unit (TICU).
Methods:
Children were defined as being <16 years of age. The study covered the 5-year period January 2008-December 2012. Eligible patients were identified from a prospective database maintained in the level 1 TICU at Inkosi Albert Luthuli Central Hospital, Durban, South Africa. Data extracted were referral source, mechanism of injury, age and gender distribution, injury severity score (ISS), anatomical distribution of injury and mortality.
Results:
A total of 181 patients admitted during the study period accounted for 15.9% of all admissions. There were 84 females (46.4%) and 97 males (53.6%), with a median age of 7 years (interquartile range (IQR) 4-10). Sources of admission were directly from the scene in 38 cases (21.0%), from a primary healthcare facility in 47 (26.0%), from a regional hospital in 56 (31.0%) and from a tertiary facility in 40 (22.0%). Mortality rates according to location of transfer were regional hospital 8 deaths (30.8%), tertiary facility 7 (26.9%), primary health clinic 7 (26.9%), and from the scene 4 (15.4%). Mechanisms of injury were pedestrian-motor vehicle collision (PMVC) in 105 cases (58.0%), motor vehicle passenger in 38 (21.0%), non-vehicular blunt trauma in 18 (10.0%), gunshot wounds (GSWs) in 12 (6.6%), stab wounds in 6 (3.3%), bull goring in 1 (0.5%) and bicycle accident 1 (0.5%). The median ISS for all admissions was 25 (IQR 16-38). ISSs were >25 in 98 patients (54.1%), 16-25 in 51 (28.2%), 9-15 in 9 (4.9%) and <9 in 13 (7.2%); 61.9% of patients had head injuries, 48.1% injuries to the extremities, 41.4% abdominal trauma, 40.3% thoracic trauma, 20.4% external soft-tissue trauma, 9.9% cervical injury and 9.4% facial trauma. There were 26 deaths (14.4%), of which PMVCs accounted for 16 (61.5%), motor vehicle passengers for 7 (26.9%), blunt trauma for 2 (7.7%) and GSWs for 1 (3.8%). The majority of deaths (92%) were of patients with an ISS>25. Of the 26 patients who died, 88.4% had a head injury, 46.2% an extremity injury, 38.5% an external injury, 34.6% abdominal or chest injuries, 19.2% neck injury and 11.5% facial injury.
Conclusions:
Motor vehicle-related injuries, especially PMVCs, dominate severe paediatric trauma and there is an urgent need for more road traffic education and stringent measures to decrease the incidence and associated morbidity and mortality.


Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:20
Acute Kidney Injury V: Interprofessional Care