Related Experiment Video
Updated: Apr 1, 2026
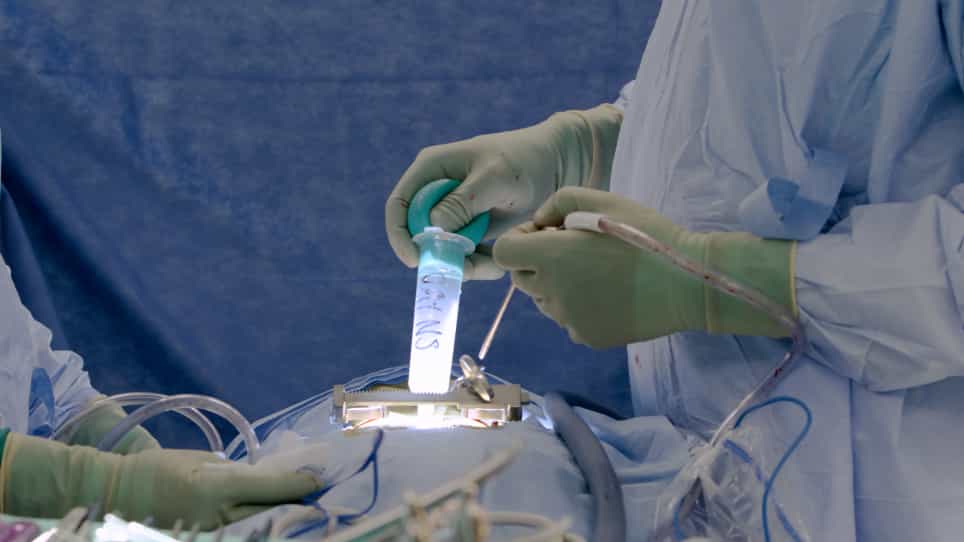

Intraoperative Ultrasound in Spinal Surgery
Published on: August 17, 2022
Navigated intraoperative ultrasound for resection of gliomas: Predictive value, influence on resection and survival
Aliasgar V Moiyadi1, Sadhana Kannan, Prakash Shetty
1Department of Neurosurgery, Advanced Centre for Training, Research and Education in Cancer (ACTREC), Tata Memorial Centre, Navi Mumbai, Maharashtra, India.

Background:
Navigable ultrasound (NUS) is a useful adjunct for controlling resection in intra-axial brain tumors. We investigated its role in predicting residual disease and thereby in influencing the intraoperative decision regarding additional resection as also its influence on survival in glioblastoma patients.
Methods:
A prospectively maintained database was accessed to retrieve the data regarding consecutive histologically verified gliomas operated using the NUS. We documented the number of times US images were obtained, the surgeon's impression of each scan and the subsequent decision regarding further resection. Survival (progression-free and overall) was calculated for patients with a glioblastoma, and univariate and multivariate analyses performed.
Results:
The NUS was used for resection control in 88 gliomas. In 66 cases, intermediate scans were performed resulting in further resection in 60 of them. Radiological gross total resection was obtained in 46 cases (44%). The US correctly predicted postoperative residue in 83% cases (sensitivity and specificity of 87 and 78% respectively; positive and negative predictive values of 82 and 84%). There were 9 false positives and 6 false negative cases. When the US was false positive, the resolution was more often good (7 of 9 cases); whereas when there were false negatives, it was more likely to be less than optimal (4 of 6). Morbidity was 17% and this was not related to the additional resections. In the subset of glioblastoma patients (n = 28) use of NUS was associated with significantly better progression-free as well as overall survival rates.
Conclusions:
NUS is a useful intraoperative adjunct in controlling resections. It positively and decisively influences the intraoperative course of the surgery. Understanding its correct technique and limitations, along with experience in image interpretation can help in maximizing its accuracy without compromising functional outcomes. Optimally utilized, it can improve survival.

