Related Experiment Video
Updated: Apr 1, 2026
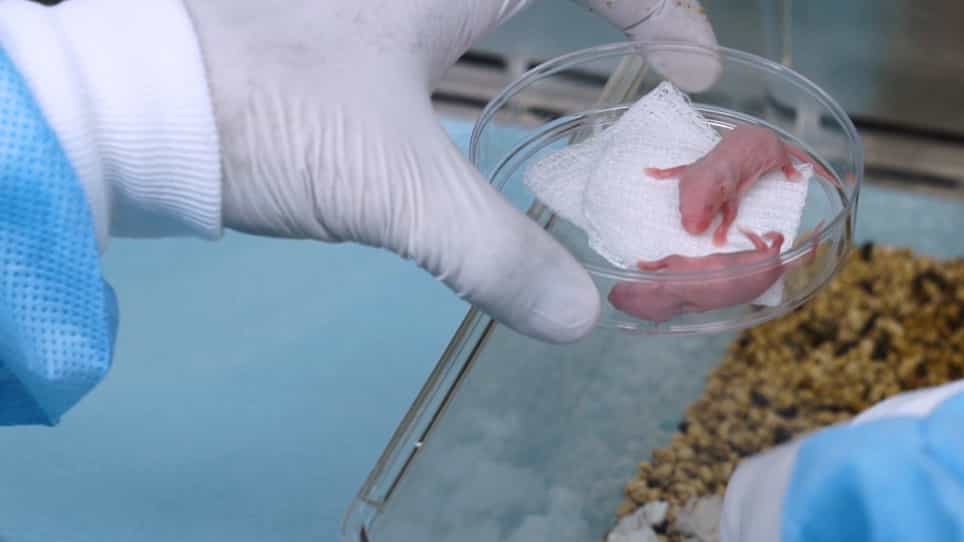

Chronic, Acute, and Reactivated HIV Infection in Humanized Immunodeficient Mouse Models
Published on: December 3, 2019
Haematological manifestations of human immune deficiency virus infection
Prakash Vishnu1, David M Aboulafia1,2
1Floyd & Delores Jones Cancer Institute at Virginia Mason Medical Center, Seattle, WA, USA.

Early in the human immunodeficiency virus (HIV) epidemic, infected patients presented to medical attention with striking abnormalities in each of the major blood cell lineages. The reasons for these derangements remain complex and multifactorial. HIV infects multipotent haematopoietic progenitor cells and establish latent cellular reservoirs, disturbs the bone marrow microenvironment and also causes immune dysregulation. These events lead to cytokine imbalances and disruption of other factors required for normal haematopoiesis. Activation of the reticulo-endothelial system can also result in increased blood cell destruction. The deleterious effects of medications, including first and second generation anti-retroviral agents, on haematopoiesis were well documented in the early years of HIV care; in the current era of HIV-care, the advent of newer and less toxic anti-retroviral drugs have had a more beneficial impact on haematopoiesis. Due to impaired regulation of the immune system and potential side effects of one or more anti-retroviral agents, there is also an increase in coagulation abnormalities such as thromboembolism, and less frequently, acquired disorders of coagulation including thrombotic thrombocytopenic purpura, immune thrombocytopenic purpura and acquired inhibitors of coagulation. In this article we review the epidemiology and aetiology of select non-oncological haematological disorders commonly seen in people living with HIV-acquired immune deficiency syndrome.
Early in the human immunodeficiency virus (HIV) epidemic, infected patients presented to medical attention with striking abnormalities in each of the major blood cell lineages. The reasons for these derangements remain complex and multifactorial. HIV infects multipotent haematopoietic progenitor cells and establish latent cellular reservoirs, disturbs the bone marrow microenvironment and also causes immune dysregulation. These events lead to cytokine imbalances and disruption of other factors required for normal haematopoiesis. Activation of the reticulo-endothelial system can also result in increased blood cell destruction. The deleterious effects of medications, including first and second generation anti-retroviral agents, on haematopoiesis were well documented in the early years of HIV care; in the current era of HIV-care, the advent of newer and less toxic anti-retroviral drugs have had a more beneficial impact on haematopoiesis. Due to impaired regulation of the immune system and potential side effects of one or more anti-retroviral agents, there is also an increase in coagulation abnormalities such as thromboembolism, and less frequently, acquired disorders of coagulation including thrombotic thrombocytopenic purpura, immune thrombocytopenic purpura and acquired inhibitors of coagulation. In this article we review the epidemiology and aetiology of select non-oncological haematological disorders commonly seen in people living with HIV-acquired immune deficiency syndrome.

Related Concept Videos
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency...
 01:26
Sexually Transmitted Infections
 01:27
Cytomegalovirus Disease
 01:10
Retrovirus Life Cycles
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...