Related Experiment Video
Updated: Apr 1, 2026


Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse POP Quantification System
Published on: September 20, 2018
Birth position and obstetric anal sphincter injury: a population-based study of 113 000 spontaneous births
Charlotte Elvander1, Mia Ahlberg2, Li Thies-Lagergren3
1Department of Medicine, Division of Clinical Epidemiology, T2, Karolinska University Hospital, 171 76, Stockholm, Sweden. charlotte.elvander@ki.se.

Background:
The association between birth position and obstetric anal sphincter injury (OASIS) in spontaneous vaginal deliveries is unclear.
Methods:
The study was based on the Stockholm-Gotland Obstetric Database (Sweden) from Jan 1(st) 2008 to Oct 22(nd) 2014 and included 113 279 singleton spontaneous vaginal births with no episiotomy. We studied risk of OASIS with respect to the following birth positions: a) sitting, b) lithotomy, c) lateral, d) standing on knees, e) birth seat, f) supine, g) squatting, h) standing and i) all fours. All analyses were stratified for parity. General linear models were used to calculate risk ratios (RR) adjusted for maternal, pregnancy and fetal characteristics.
Results:
The rates of OASIS among nulliparous women, parous women and women undergoing vaginal birth after a caesarean (VBAC) were 5.7%, 1.3% and 10.6%, respectively. The rates varied by birth position: from 3.7 to 7.1% in nulliparous women, 0.6% to 2.6% in parous women and 5.6% to 18.2% in women undergoing VBAC. Regardless of parity, the lowest rates were found among women giving birth in standing position and the highest rates among women birthing in the lithotomy position. Compared with sitting position, the lithotomy position involved an increased risk of OASIS among nulliparous (adjusted RR 1.17, 95% CI 1.06-1.29) and parous women (adjusted RR 1.66, 95% CI 1.35-2.05). Birth seat and squatting position involved an increased risk of OASIS among parous women (adjusted RR [95% CI] 1.36 [1.03-1.80] and 2.16 [1.15-4.07], respectively). Independent risk factors for OASIS were maternal age, head circumference ≥35 cm, birth weight ≥4000 g, length of gestation ≥ 40 weeks, prolonged second stage of labour, non-occiput anterior presentation and oxytocin augmentation.
Conclusions:
Compared with sitting position, lateral position has a slightly protective effect in nulliparous women whilst an increased risk is noted among women in the lithotomy position, irrespective of parity. Squatting and birth seat position involve an increase in risk among parous women.


Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:26
Psychosexual Stages of Personality: Anal
 01:28
Development of the Oral Microbiota
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:27
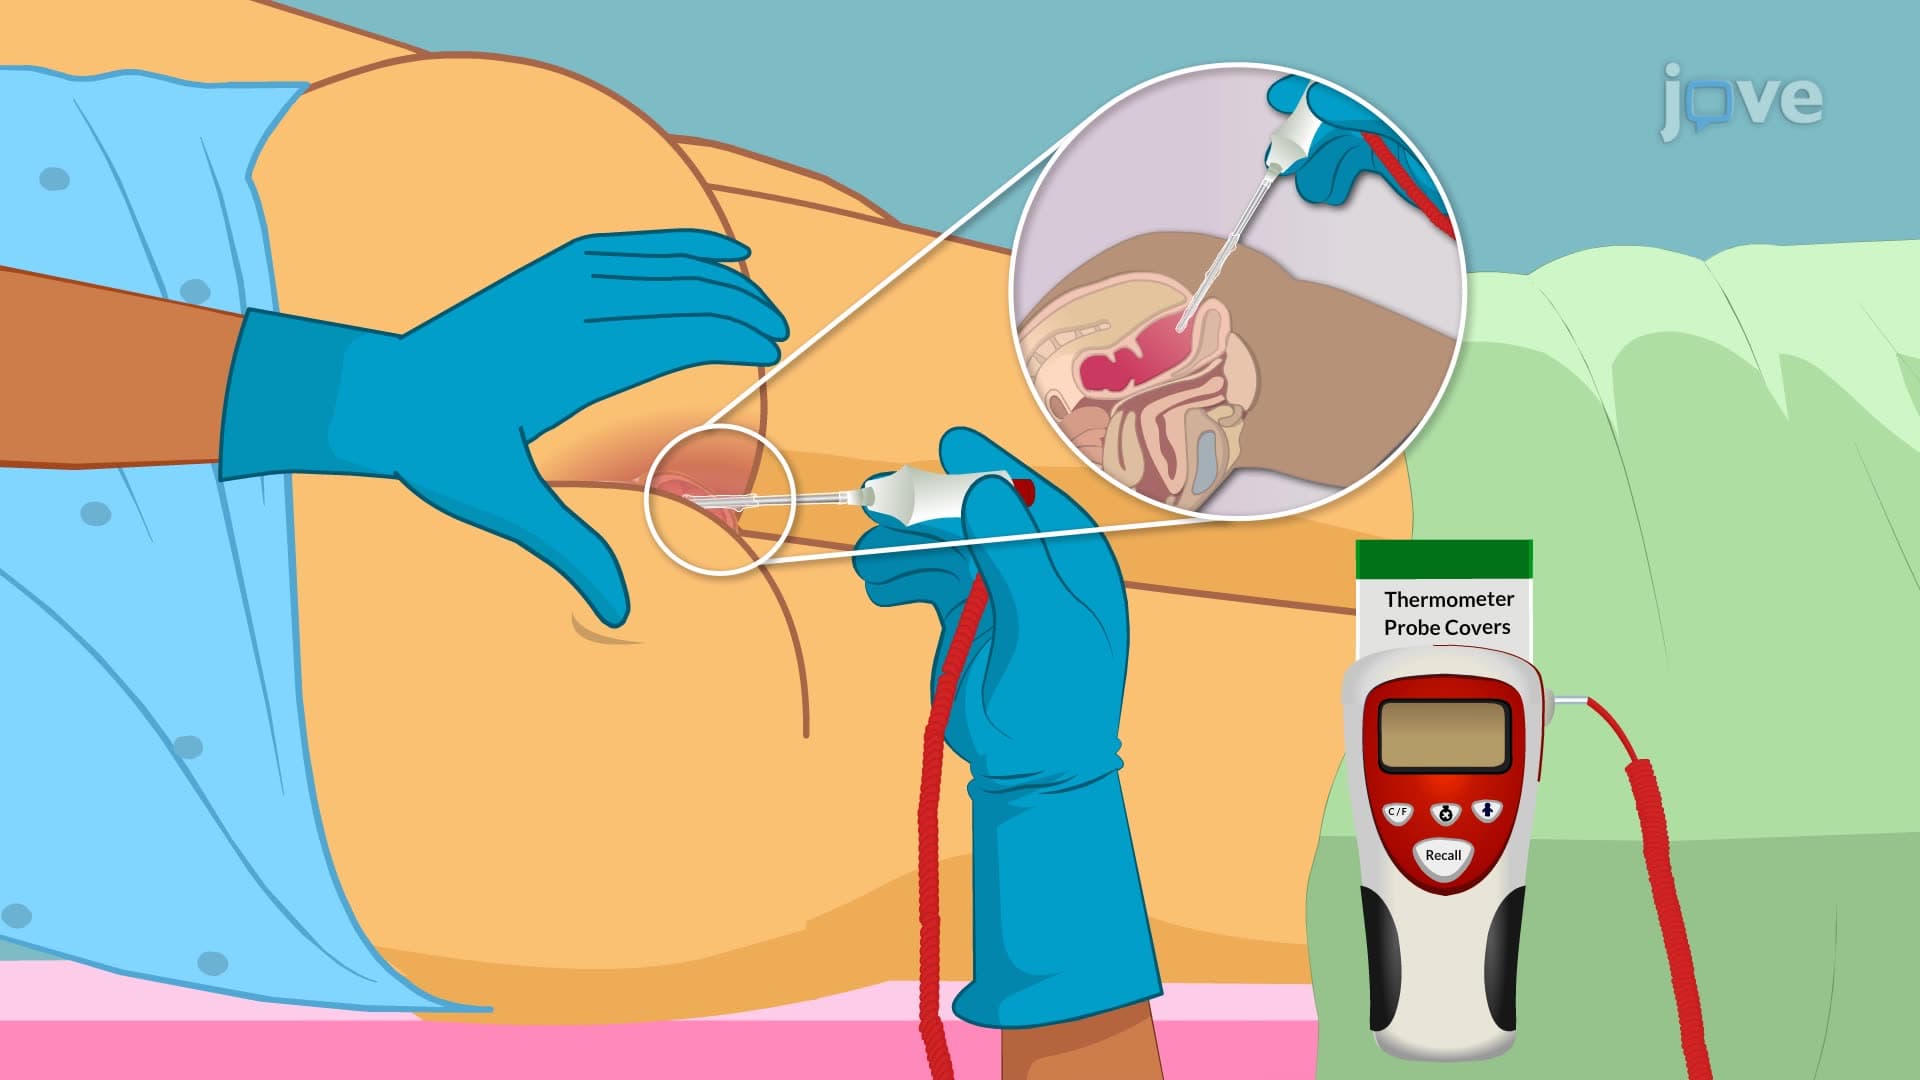
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...