QRS distortion in pre-reperfusion electrocardiogram is a bedside predictor of large myocardium at risk and infarct size (a METOCARD-CNIC trial substudy)
Related Experiment Video
Updated: Apr 1, 2026
Confirmation of Myocardial Ischemia and Reperfusion Injury in Mice Using Surface Pad Electrocardiography
Published on: November 24, 2016
Maria Jose Valle-Caballero1, Rodrigo Fernández-Jiménez2, Raquel Díaz-Munoz3
1Virgen Macarena University Hospital, Sevilla, Spain.

Background:
QRS distortion is an electrocardiographic (ECG) sign of severe ongoing ischemia in the setting of ST-segment elevation acute myocardial infarction (STEMI). We sought to evaluate the association between the degree of QRS distortion and myocardium at risk and final infarct size, measured by cardiac magnetic resonance (CMR).
Methods:
A total of 174 patients with a first anterior STEMI reperfused by primary angioplasty were prospectively recruited. Pre-reperfusion ECG was used to divide the study population into three groups according to the absence of QRS distortion (D0) or its presence in a single lead (D1) or in 2 or more contiguous leads (D2+). Myocardium at risk and infarct size were determined by CMR one week after STEMI. Multiple regression analysis was used to study the association of QRS distortion with myocardium at risk and infarct size, with adjustment for relevant clinical and ECG variables.
Results:
101 patients (58%) were in group D0, 30 (17%) in group D1, and 43 (25%) in group D2+. Compared with group D0, presence of QRS distortion (groups D2+ and D1) was associated with a significantly adjusted larger extent of myocardium at risk (group D2+: absolute increase 10.4%, 95% CI 6.1-14.8%, p<0.001; group D1: absolute increase 3.3%, 95% CI 1.3-7.9%, p=0.157) and larger infarct size (group D2+: absolute increase 10.1%, 95% CI 5.5-14.7%, p<0.001; group D1: absolute increase 4.9%, 95% CI 0.08-9.8%, p=0.046).
Conclusions:
Distortion in the terminal portion of the QRS complex on pre-reperfusion ECG in two or more leads is independently associated with larger myocardium at risk and infarct size in the setting of primary angioplasty-reperfused anterior STEMI. QRS distortion in only one lead is independently associated with larger infarct size in this setting. Our findings suggest that QRS distortion analysis could be included in risk-stratification of patients presenting with anterior STEMI.
Related Concept Videos
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:24
ECG Interpretation of Rhythms
Components of the Electrocardiogram
The primary components of a normal ECG waveform in Normal sinus rhythm(NSR) include the P wave, PR interval, QRS complex, ST segment, T wave, and occasionally a U wave.
ECG waveforms are divided by vertical and horizontal lines at standard intervals.
The horizontal axis measures time and rate, and the vertical axis measures amplitude or voltage....
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
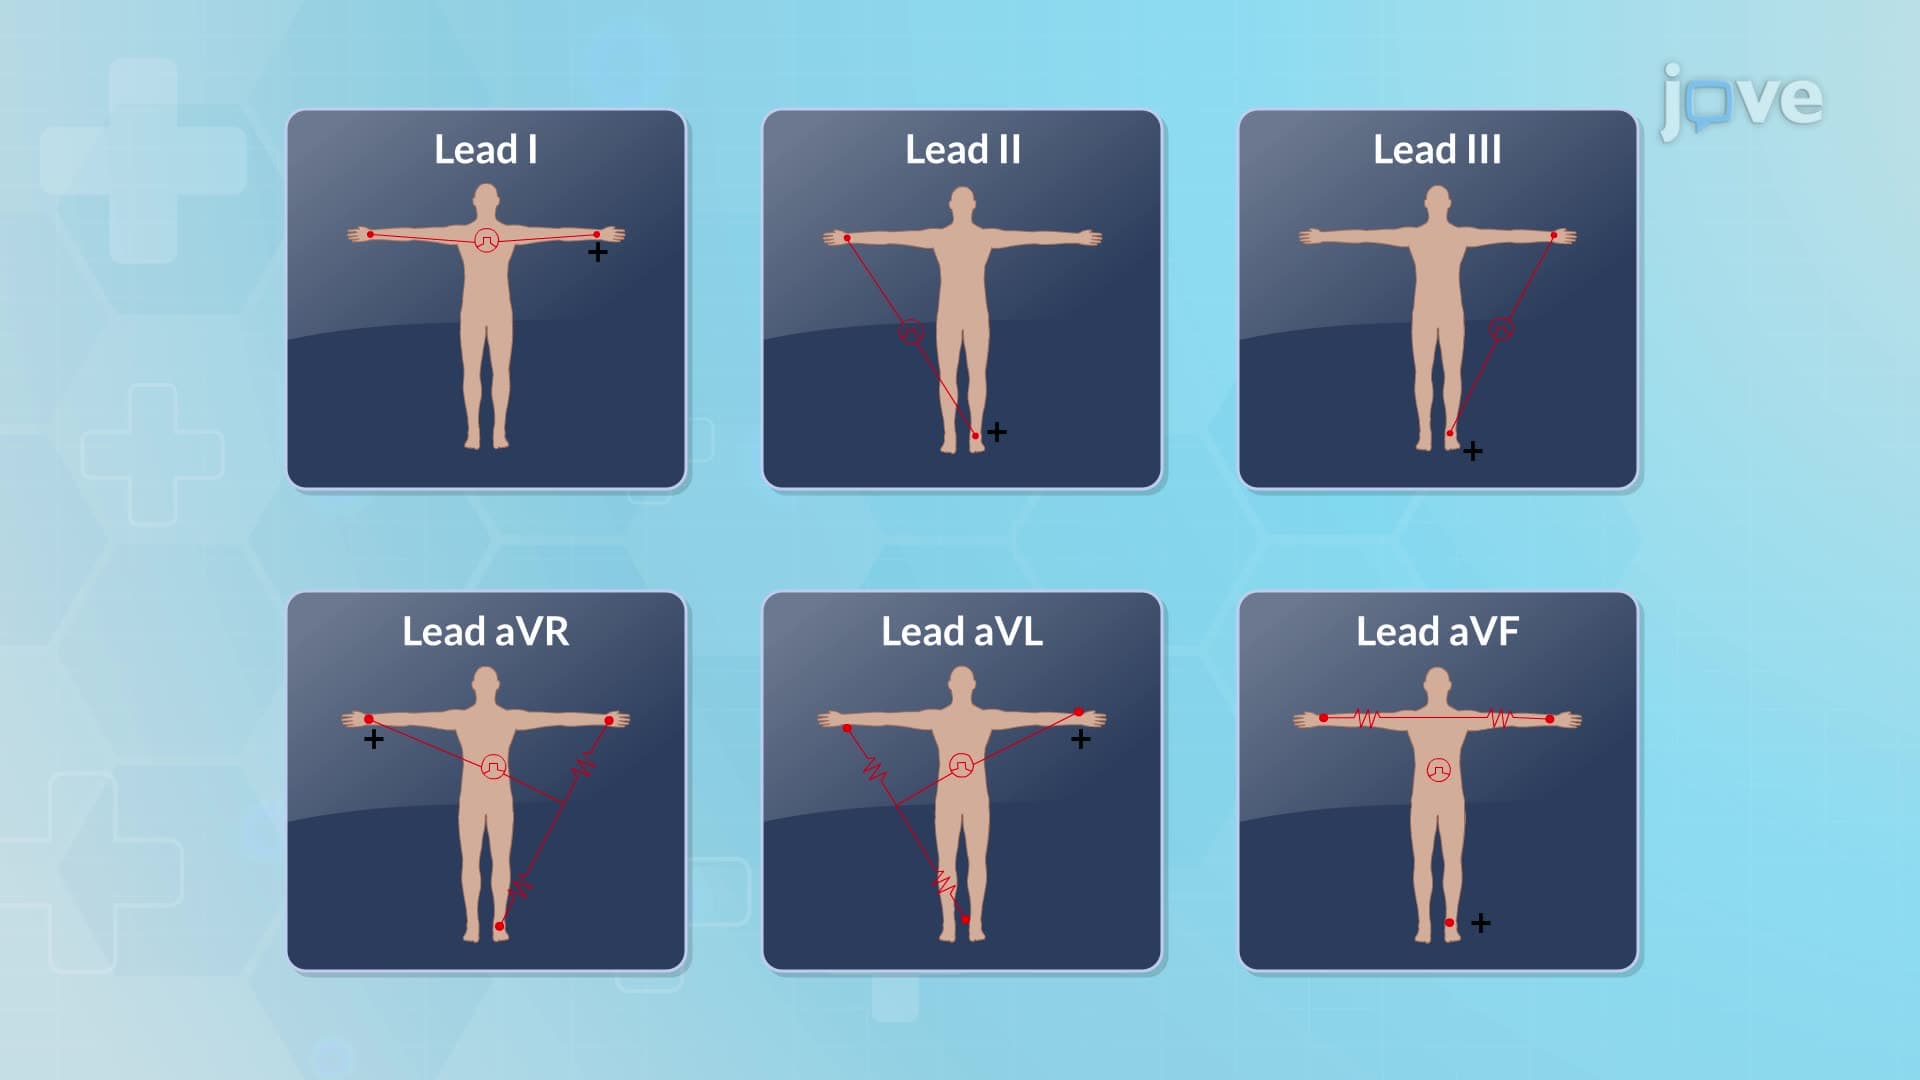 01:28
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations