Related Experiment Video
Updated: Mar 31, 2026
Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Surgical site infection following hysterectomy: adjusted rankings in a regional collaborative
Daniel M Morgan1, Carolyn W Swenson1, Kristin M Streifel2
1Department of Obstetrics and Gynecology, University of Michigan, Ann Arbor, MI.

Backround:
Surgical site infection after abdominal hysterectomy (defined as open and laparoscopic) will be a metric used to rank and penalize hospitals in the Hospital Acquired Condition Reduction program. Hospitals whose Hospital Acquired Condition Reduction score places them in the bottom quartile will lose 1% of reimbursement from the Centers of Medicaid and Medicare Services.
Objectives:
The objectives of this analysis were to develop a risk adjustment model for surgical site infection after hysterectomy, to calculate adjusted surgical site infection rates, to rank hospitals by the predicted to expected (P/E) ratio, and to compare the number of outlier hospitals with the number in the bottom quartile.
Study Design:
This was a retrospective analysis of hysterectomies from the Michigan Surgical Quality Collaborative performed between July 1, 2012, and July 1, 2014. Superficial, deep, and organ space surgical site infections were categorized according to Centers for Disease Control and Prevention criteria. Deep and organ space surgical site infections were considered 1 group for this analysis because these spaces are contiguous after hysterectomy. Hospital rankings focused on deep/organ space events because the Hospital Acquired Condition Reduction program will rank and penalize based on them, not superficial surgical site infection. Hierarchical multivariable logistic regression, which takes into account hospital effects, was used to identify risk factors for all surgical site infections and deep/organ space surgical site infections. Predicted to expected ratios for deep surgical site infection were calculated for each hospital and used to determine hospital rankings. Outliers were defined as those hospitals who predicted to expected confidence intervals crossed the reference line of 1. The number of outlier hospitals was compared with the number in the bottom quartile.
Results:
The overall surgical site infection rate following hysterectomy was 2.1% (351 of 16,548). Deep/organ space surgical site infection accounted for 1.0% (n = 167 of 16,548). Deep surgical site infection was associated independently with younger age, longer surgical times, gynecological cancer, and open hysterectomy. There was a marginal association with blood transfusion. After risk adjustment of rates and ranking by the predicted to expected ratio, there was a change in quartile rank for 42.8% of hospitals (21 of 49). Two hospitals were identified as outliers. However, if the bottom quartile was identified, as called for by the Hospital Acquired Condition Reduction program, 10 additional hospitals would be targeted for a penalty. Hospitals with < 300 beds were most likely to see their quartile rank worsen, whereas those > 500 beds were most likely to see their quartile rank improve (P = .01).
Conclusion:
After adjusting for patient-related factors and site variation, more than 40% of hospitals will change quartile rank with respect to deep surgical site infection. Identifying a quartile of hospitals that are statistically different from others was not feasible in our collaborative because only 2 of 12 hospitals were outliers. These findings suggest that under the Hospital Acquired Condition Reduction program, many hospitals will be unjustly penalized.
More Related Videos
 05:21
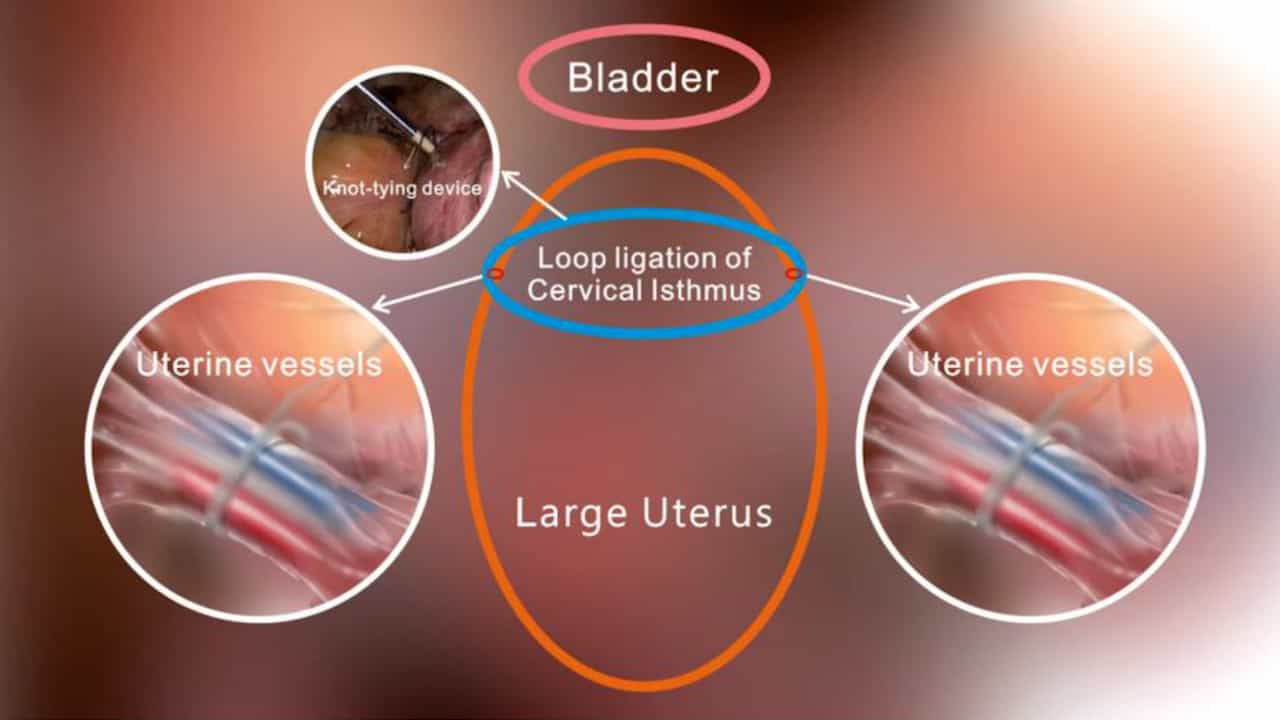
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
 07:48
Intraoperative Video Consultation Following Bile Duct Transection Facilitates Direct OR Transfer for Robotic Hepaticojejunostomy at Tertiary Center
Published on: January 9, 2026
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.