Related Experiment Video
Updated: Mar 31, 2026

Establishment of an Extracellular Acidic pH Culture System
Published on: November 19, 2017
Dietary Acid Load is Associated With Serum Bicarbonate but not Insulin Sensitivity in Chronic Kidney Disease
Halil O Ikizler1, Leila Zelnick2, John Ruzinski2
1University of Vermont College of Medicine, Burlington, Vermont; Kidney Research Institute, University of Washington, Seattle, Washington.

Objective:
In chronic kidney disease (CKD), dietary acid may promote metabolic acidosis and insulin resistance, which in turn may contribute to adverse clinical health outcomes. We examined associations between dietary acid load, serum bicarbonate, and insulin sensitivity in CKD.
Design:
In a cross-sectional study, we collected 3-day prospective food diaries to quantify dietary acid load as net endogenous acid production (NEAP, the nonvolatile acid load produced by the diet's acid balance) and potential renal acid load (PRAL). We measured urine net acid excretion (NAE) in 24-hour urine samples. Insulin sensitivity was measured by hyperinsulinemic euglycemic clamp.
Subjects:
Forty-two patients with CKD Stages 3 to 5 attending nephrology clinics in the Pacific Northwest and 21 control subjects (estimated glomerular filtration rate [eGFR] ≥ 60 mL/minute/1.73 m(2)).
Main Outcome Measures:
Serum bicarbonate and insulin sensitivity (SIclamp).
Results:
Mean age was 60.8 ± 13.6 years, and 54% of participants were men. Mean eGFR and serum bicarbonate concentrations were 34.4 ± 13.1 mL/minute/1.73 m(2) and 24.1 ± 2.9 mEq/L for participants with CKD and 88.6 ± 14.5 mL/minute/1.73 m(2) and 26.3 ± 1.8 mEq/L for control subjects, respectively. Mean NEAP, PRAL, and NAE were 58.2 ± 24.3, 9.7 ± 18.4, and 32.1 ± 19.8 mEq/day, respectively. Considering all participants, dietary acid load was significantly, inversely associated with serum bicarbonate, adjusting for age, gender, race, eGFR, body mass index, and diuretic use: -1.2 mEq/L per standard deviation (SD) NEAP (95% confidence interval [CI] -1.8 to -0.6, P < .0001); -0.9 mEq/L bicarbonate per SD PRAL (95% CI -1.5 to -0.4, P = .0005); -0.7 mEq/L bicarbonate per SD NAE (95% CI -1.2 to -0.1, P = .01). These associations were similar in participants with and without CKD. However, neither NEAP and PRAL nor NAE was significantly associated with SIclamp. Serum bicarbonate was also not significantly associated with SIclamp.
Conclusions:
In CKD, dietary acid load is associated with serum bicarbonate, suggesting that acidosis may be improved by dietary changes, but not with insulin sensitivity.
More Related Videos
 10:18
Real-Time, Semi-Automated Fluorescent Measurement of the Airway Surface Liquid pH of Primary Human Airway Epithelial Cells
Published on: June 13, 2019
 08:50
5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
Related Concept Videos
 01:29
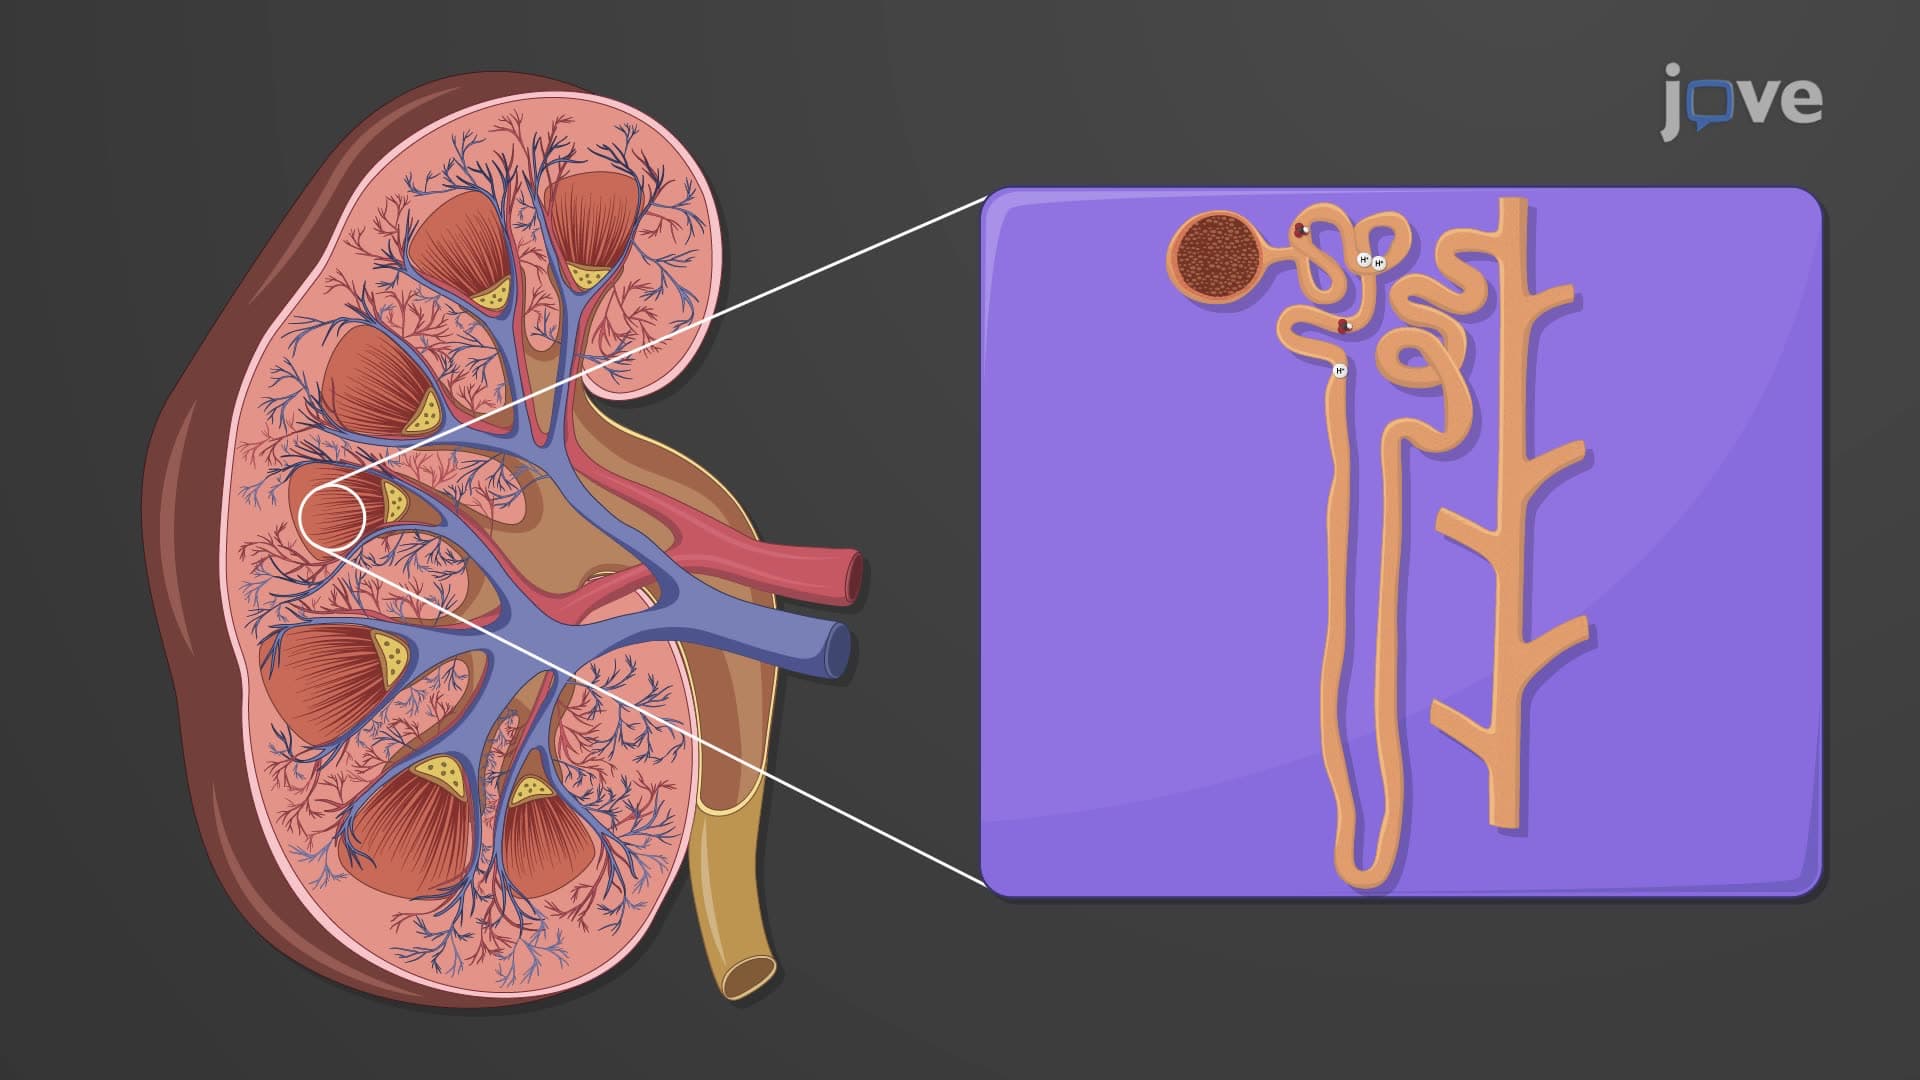
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:31
Acid Suppressive Drugs for Peptic Ulcer Disease: Antacids
However, this neutralization reaction between...