Related Experiment Video
Updated: Mar 31, 2026
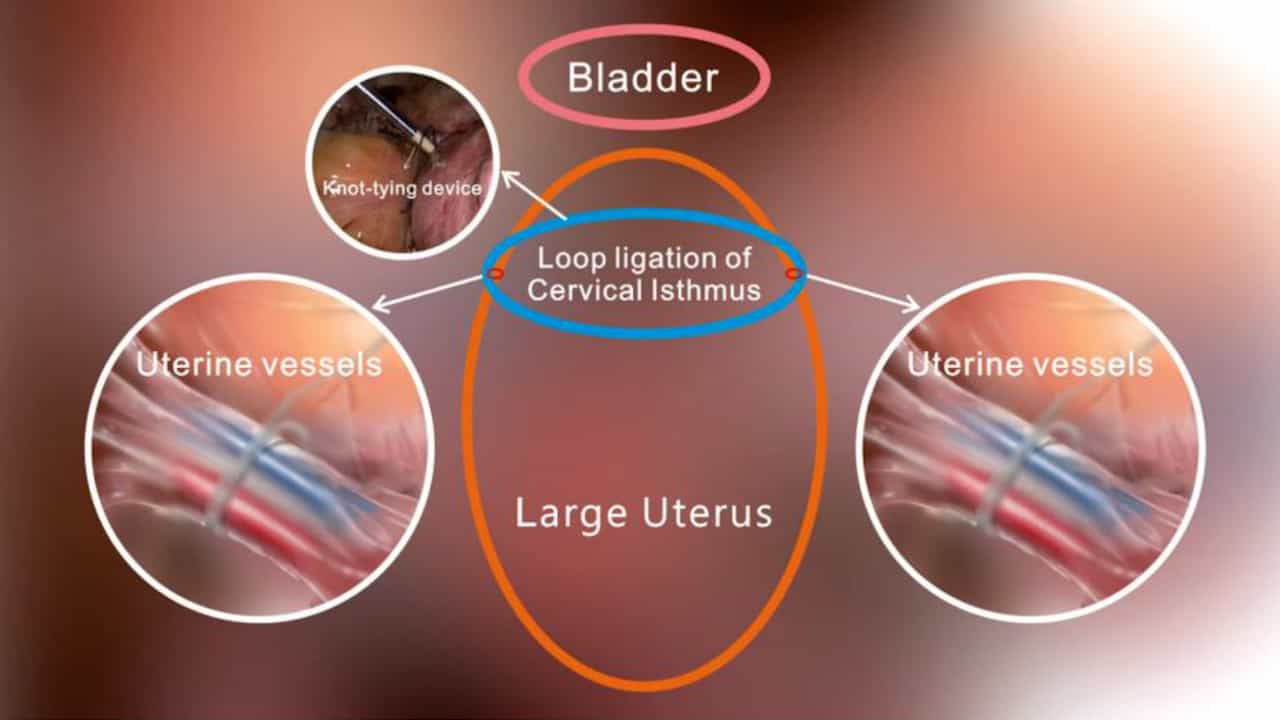

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Analysis of High-, Intermediate-, and Low-Volume Surgeons When Performing Hysterectomy for Uterovaginal Prolapse
Daniel M Morgan1, Samantha Pulliam, Rony A Adam
1From the *Department of Obstetrics and Gynecology, University of Michigan, Ann Arbor, MI; †Department of Obstetrics and Gynecology, Massachusetts General Hospital, Boston, MA; ‡Department of Obstetrics and Gynecology, Vanderbilt University, Nashville, TN; §School of Public Health, University of Michigan, Ann Arbor, MI; and ∥Department of Obstetrics and Gynecology, Southern California Permanente Medical Group, Irvine, CA.

Objectives:
To determine if surgeon volume is associated with differences in the use of apical colpopexy and cystoscopy and in the rate of intraoperative complications during hysterectomy for prolapse.
Methods:
We performed a multicenter retrospective review of hysterectomies done for uterovaginal prolapse at 4 hospital systems between January 1, 2008, and December 31, 2011. Low (≤10 cases)-, intermediate (11-49 cases)-, and high (≥50 cases)-volume surgeon groups for the 4-year period were established a priori. Rates of concomitant colpopexy, cystoscopy, and intraoperative complications were determined by chart review for 15% of the cases. Multivariate logistic regression models adjusted for site and other clinical and patient variables were used to estimate associations between surgeon case volume and the use of apical colpopexy and cystoscopy and the rate of intraoperative complications.
Results:
Three hundred one surgeons performed 4238 hysterectomies for prolapse during the study period. Six hundred thirty-eight patients were selected for chart review. The rates among high-, intermediate-, and low-volume surgeons for performing colpopexy were 85.2% versus 77.8% versus 61.1% (P < 0.001) and for cystoscopy were 96.8% versus 78.3% versus 74.7% (P < 0.001), respectively. Rates of intraoperative complications among the 3 groups were 4.4%, 11.6%, and 6.3% (P = 0.011), respectively. With adjustment, high-volume surgeons were more likely to do a colpopexy than low-volume surgeons (odds ratio [OR], 1.9; 95% confidence interval [CI], 1.1-3.1); however, the likelihood of colpopexy did not differ between high- and intermediate-volume surgeons (OR, 1.9; 95% CI, 0.84-4.3) or between intermediate- and low-volume surgeons (OR, 0.99; 95% CI, 0.50-2.0). High-volume surgeons were more likely than intermediate-volume (OR, 4.4; 95% CI, 1.7-11.0) and low-volume (OR, 4.5; 95% CI, 2.6-8.0) surgeons to do a cystoscopy. High-volume (OR, 0.42; 95% CI, 0.30-0.61) and low-volume (OR, 0.32; 95% CI, 0.15-0.66) surgeons were less likely than intermediate-volume surgeons to have intraoperative complications. The difference between high- and low-volume surgeons was not statistically significant (OR, 0.77; 95% CI, 0.5-1.2).
Conclusions:
Practice patterns with respect to hysterectomy for prolapse are complex when the use of colpopexy and cystoscopy and rates of intraoperative complications are analyzed by surgeon volume. The finding that intermediate-volume surgeons have the highest rates of intraoperative complications suggests a nonlinear relationship between surgeon volume and avoidance of injury.
More Related Videos
 03:30
Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
 05:46
Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Related Concept Videos
 01:19
Urodynamic Studies: Uroflowmetry
 01:25
Urinary Tract Calculi VI: Surgical Management