Related Experiment Video
Updated: Mar 31, 2026

The Supraclavicular Fossa Ultrasound View for Central Venous Catheter Placement and Catheter Change Over Guidewire
Published on: December 23, 2014
Defining the surface anatomy of the central venous system in children
Gregory P Tarr1, Neda Pak2, Kiarash Taghavi3
1Department of Radiology, Auckland City Hospital, Auckland, New Zealand.

Insights
Surface anatomy landmarks for central venous catheterization in children are unreliable. This study found significant variability in the superior vena cava (SVC) formation and SVC/right atrial (RA) junction, impacting catheter placement accuracy.
Area of Science:
- Pediatric anatomy
- Vascular access
- Medical imaging
Background:
- Central venous catheterization is frequently performed in children by various specialists.
- Complications associated with this procedure can be severe and life-threatening.
- A lack of evidence-based surface landmarks for pediatric central venous anatomy exists.
Purpose of the Study:
- To critically investigate the surface markings of the central venous system in children.
- To assess the anatomical variations of the superior vena cava (SVC)/right atrial (RA) junction, SVC formation, and brachiocephalic vein (BCV) formation.
Main Methods:
- Computed tomography (CT) scans of 300 children were analyzed.
- Scans were categorized into age groups: 0-3, 4-7, and 8-11 years.
- Scans with anatomical distortions due to pathology were excluded.
Main Results:
- Brachiocephalic vein (BCV) formation was consistently located behind the ipsilateral medial clavicular head.
- Superior vena cava (SVC) formation and SVC/right atrial (RA) junction levels showed significant variability with age.
- SVC formation shifted from the second costal cartilage (CC) in younger children to the first CC/first intercostal space (ICS) in older children.
- SVC/RA junction moved from the fourth CC to the third CC/third ICS with increasing age.
Conclusions:
- The anatomical landmarks for SVC formation and SVC/RA junction in children are highly variable relative to rib levels.
- Surface anatomical landmarks for the SVC/RA junction are unreliable for guiding central venous catheter tip placement.
- Further research may be needed to establish more reliable methods for accurate central venous catheter placement in pediatric patients.
Abstract:
Pediatric emergency physicians, pediatric critical care specialists, and pediatric surgeons perform central venous catheterization in many clinical settings. Complications of the procedure are not uncommon and can be fatal. Despite the frequency of application, the evidence-base describing the surface landmarks involved is missing. The aim of the current study was to critically investigate the surface markings of the central venous system in children. The superior vena cava/right atrial (SVC/RA) junction, superior vena cava (SVC) formation, and brachiocephalic vein (BCV) formation were examined independently by two investigators. Three hundred computed tomography (CT) scans collected across multiple centers were categorized by age group into: 0-3 years, 4-7 years, and 8-11 years. Scans with pathology that distorted or obscured the regional anatomy were excluded. The BCV formation was commonly found behind the ipsilateral medial clavicular head throughout childhood. This contrasts with the variable levels of SVC formation, SVC length, and SVC/RA junction. In the youngest group, SVC formation was most commonly at the second costal cartilage (CC), but moved to the first CC/first intercostal space (ICS) as the child grew. The SVC/RA junction was at the fourth CC in the youngest group and moved to the third CC/third ICS as the child grew. This study demonstrates the variable anatomy of SVC formation and the SVC/RA junction with respect to rib level. This variability underscores the unreliability of surface anatomical landmarks of the SVC/RA junction as a guide to catheter tip position.
More Related Videos
 06:02
Anatomical Reconstructions of the Human Cardiac Venous System using Contrast-computed Tomography of Perfusion-fixed Specimens
Published on: April 18, 2013
 05:51
Computed Tomography (CT) Guided Implantation of a Totally Implantable Venous Access Port (TIVAP) through Subclavian Vein
Published on: January 13, 2026
Related Concept Videos
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:17
Veins of Upper Limbs
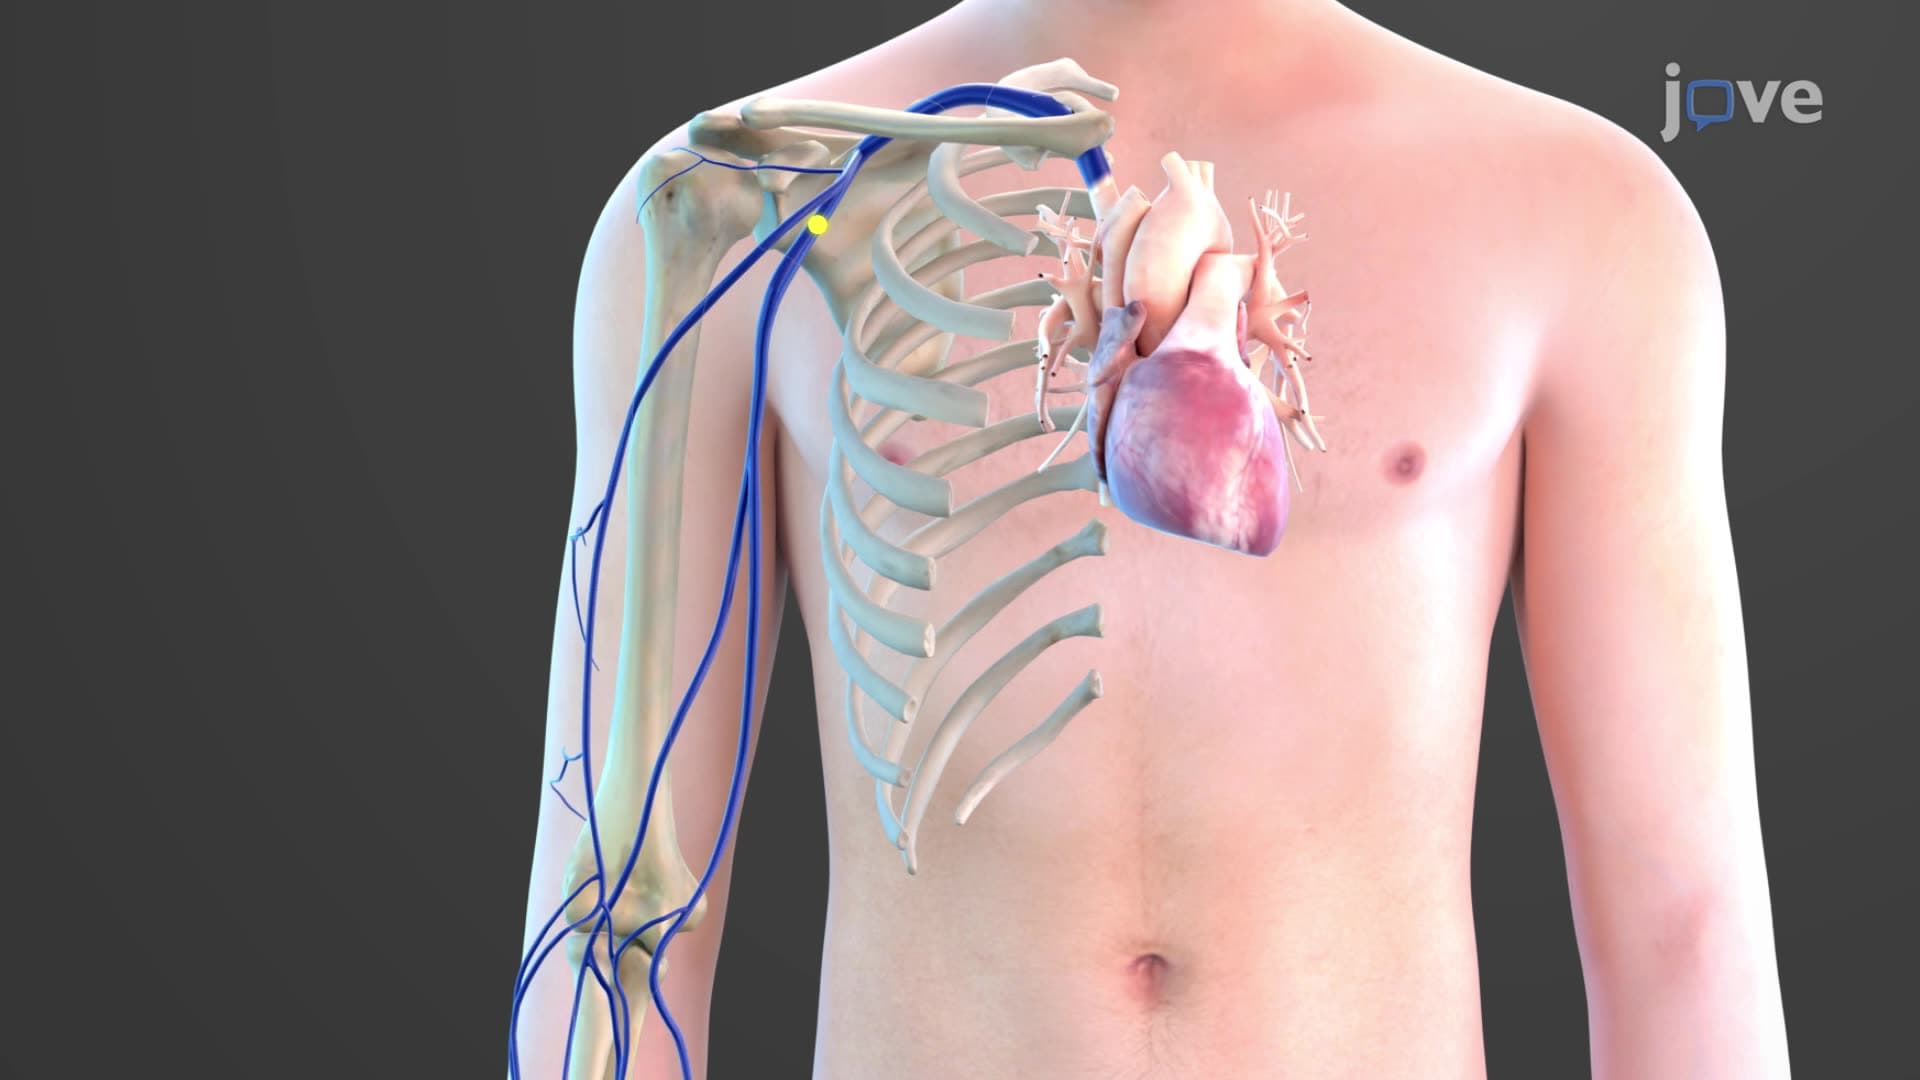
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:19
Veins of Thorax
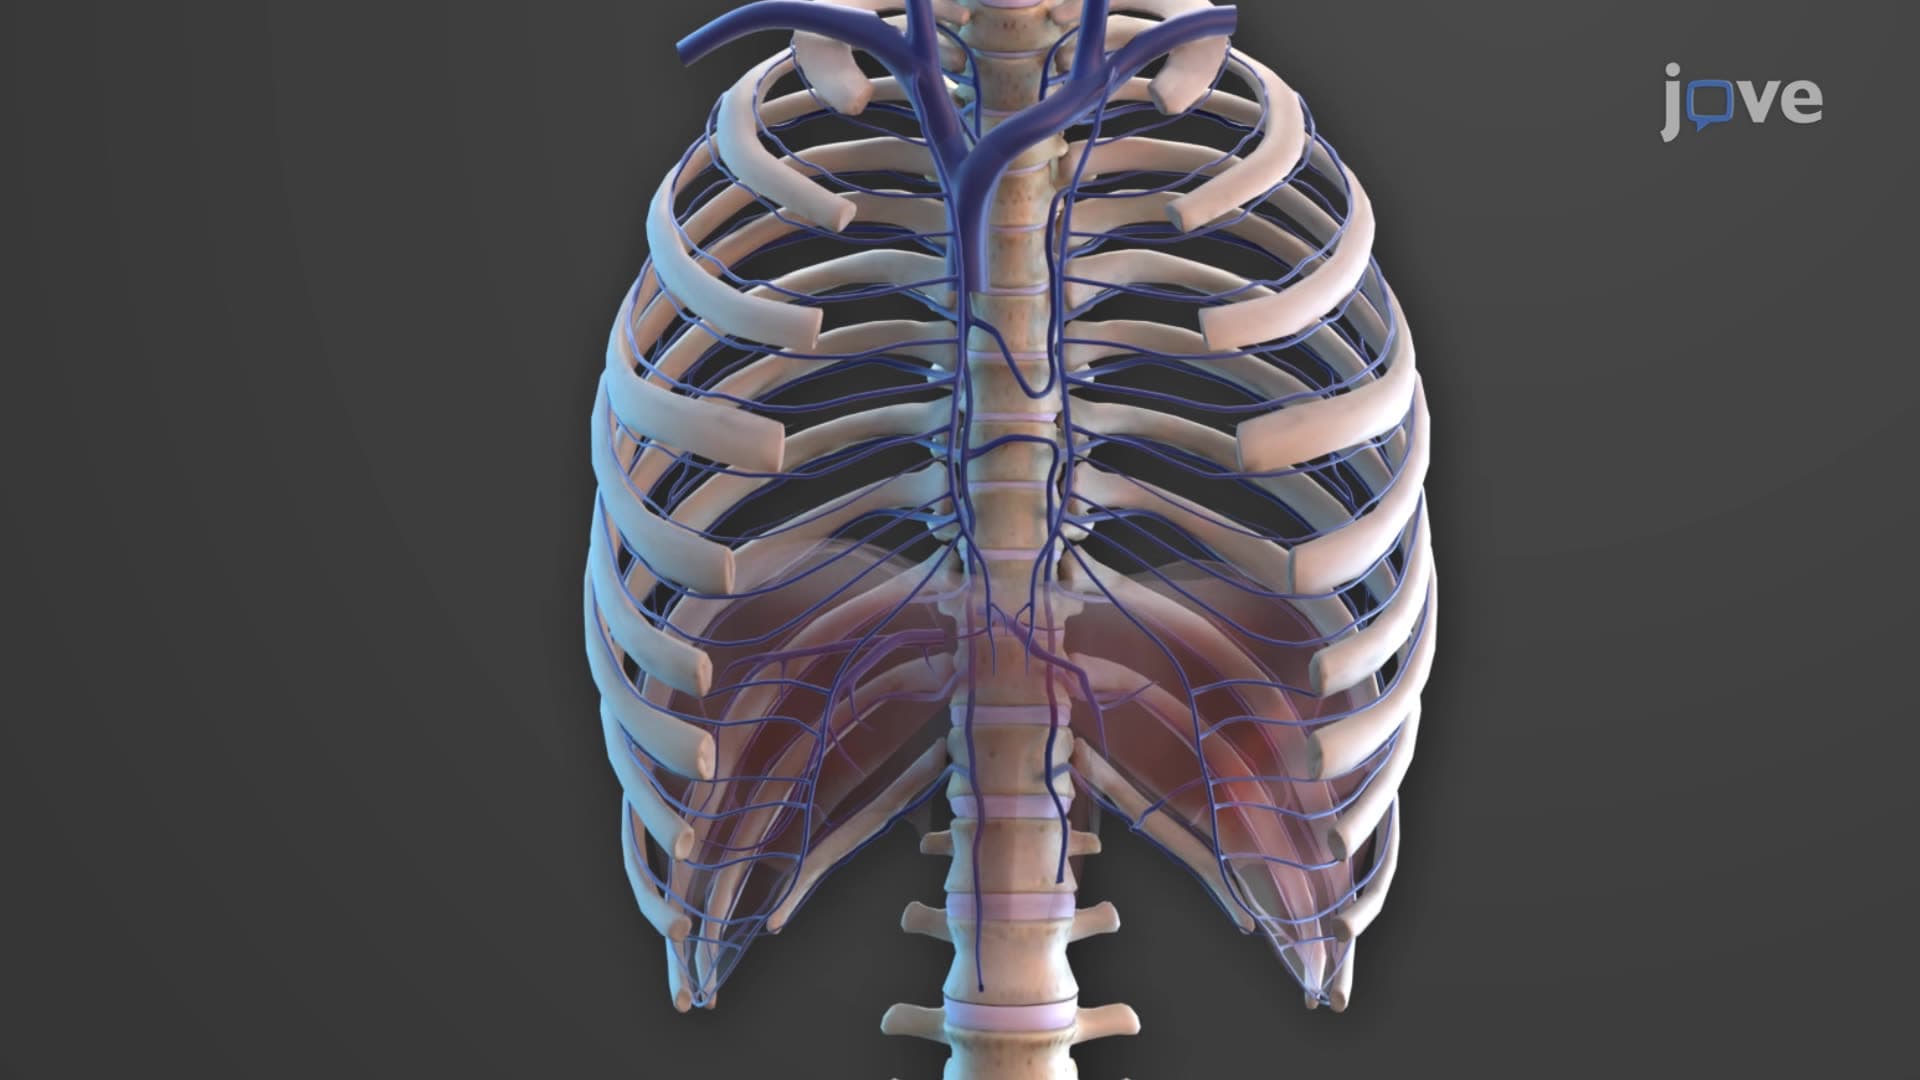
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...