Related Experiment Video
Updated: Mar 30, 2026
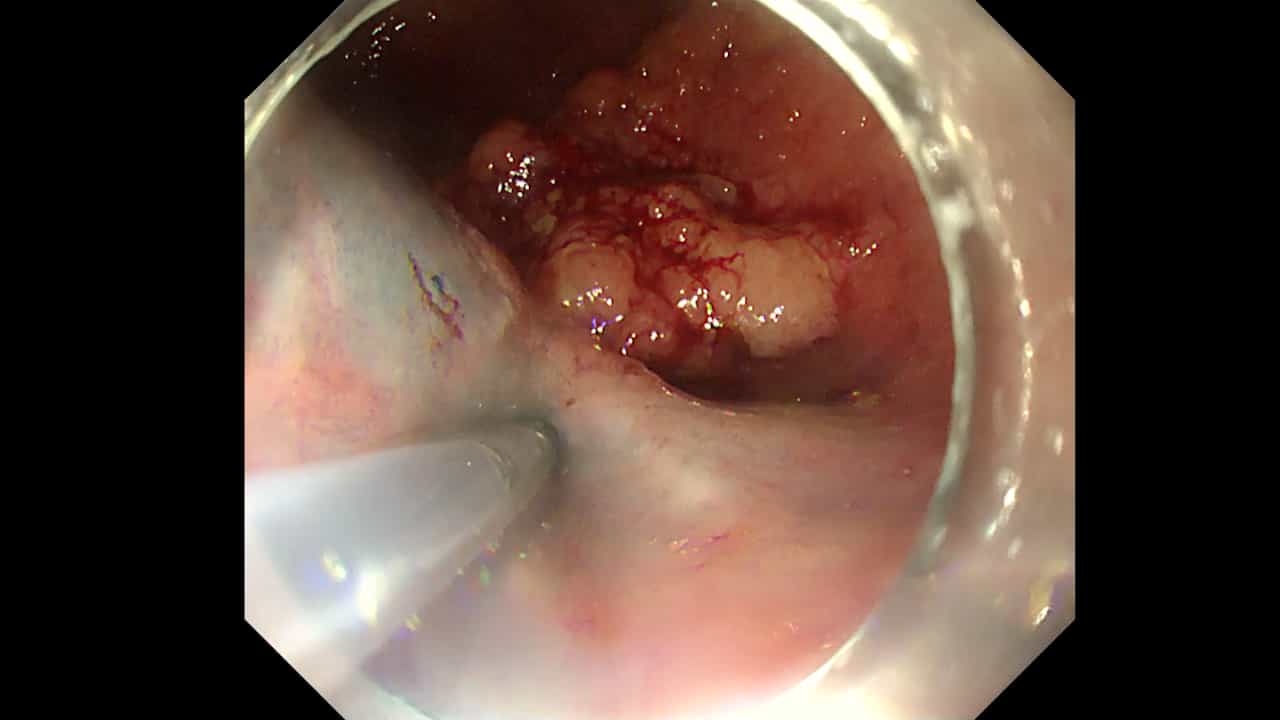

The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Cancer emerging from the recurrence of sessile serrated adenoma/polyp resected endoscopically 5 years ago
A Chino1, S Nagayama2, H Ishikawa3
1Digestive of Gastroenterology Cancer Institute Hospital, Japanese Foundation for Cancer Research, Tokyo akiko.chino@jfcr.or.jp.

Abstract:
Since the serrated neoplastic pathway has been regarded as an important pathway of colorectal carcinogenesis, few reports have been published on clinical cases of cancer derived from sessile serrated adenoma/polyp, especially on recurrence after resected sessile serrated adenoma/polyp. An elderly woman underwent endoscopic mucosal resection of a flat elevated lesion, 30 mm in diameter, in the ascending colon; the histopathological diagnosis at that time was a hyperplastic polyp, now known as sessile serrated adenoma/polyp. Five years later, cancer due to the malignant transformation of the sessile serrated adenoma/polyp was detected at the same site. The endoscopic diagnosis was a deep invasive carcinoma with a remnant sessile serrated adenoma/polyp component. The carcinoma was surgically removed, and the pathological diagnosis was an adenocarcinoma with sessile serrated adenoma/polyp, which invaded the muscularis propria. The surgically removed lesion did not have a B-RAF mutation in either the sessile serrated adenoma/polyp or the carcinoma; moreover, the initial endoscopically resected lesion also did not have a B-RAF mutation. Immunohistochemistry confirmed negative MLH1 protein expression in only the cancer cells. Lynch syndrome was not detected on genomic examination. The lesion was considered to be a cancer derived from sessile serrated adenoma/polyp recurrence after endoscopic resection, because both the surgically and endoscopically resected lesions were detected at the same location and had similar pathological characteristics, with a serrated structure and low-grade atypia. Furthermore, both lesions had a rare diagnosis of a sessile serrated adenoma/polyp without B-RAF mutation. This report highlights the need for the follow-up colonoscopy after endoscopic resection and rethinking our resection procedures to improve treatment.
More Related Videos
 03:01
Author Spotlight: A Reproductive Hysteroscopy Approach for Complete Endometrial Polyp Removal and Enhanced Endometrial Receptivity
Published on: August 2, 2024
 07:22
Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
