Related Experiment Video
Updated: Mar 30, 2026


Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Preventing ICU Subsyndromal Delirium Conversion to Delirium With Low-Dose IV Haloperidol: A Double-Blind,
Nada S Al-Qadheeb1, Yoanna Skrobik, Greg Schumaker
11School of Pharmacy, Northeastern University, Boston, MA.2Department of Medicine, McGill University Health Center, Montreal, Quebec, Canada.3Division of Pulmonary, Critical Care and Sleep Medicine, Tufts Medical Center, Boston, MA.4Department of Psychiatry, Tufts Medical Center, Boston, MA.5Department of Pharmacy, Tufts Medical Center, Boston, MA.6Research Design Center and Biostatistics Research Center, Tufts Clinical and Translational Science Institute, Tufts Medical Center, Boston, MA.

Objective:
To compare the efficacy and safety of scheduled low-dose haloperidol versus placebo for the prevention of delirium (Intensive Care Delirium Screening Checklist ≥ 4) administered to critically ill adults with subsyndromal delirium (Intensive Care Delirium Screening Checklist = 1-3).
Design:
Randomized, double-blind, placebo-controlled trial.
Setting:
Three 10-bed ICUs (two medical and one surgical) at an academic medical center in the United States.
Patients:
Sixty-eight mechanically ventilated patients with subsyndromal delirium without complicating neurologic conditions, cardiac surgery, or requiring deep sedation.
Interventions:
Patients were randomly assigned to receive IV haloperidol 1 mg or placebo every 6 hours until delirium occurred (Intensive Care Delirium Screening Checklist ≥ 4 with psychiatric confirmation), 10 days of therapy had elapsed, or ICU discharge.
Measurements And Main Results:
Baseline characteristics were similar between the haloperidol (n = 34) and placebo (n = 34) groups. A similar number of patients given haloperidol (12/34 [35%]) and placebo (8/34 [23%]) developed delirium (p = 0.29). Haloperidol use reduced the hours per study day spent agitated (Sedation Agitation Scale ≥ 5) (p = 0.008), but it did not influence the proportion of 12-hour ICU shifts patients spent alive without coma (Sedation Agitation Scale ≤ 2) or delirium (p = 0.36), the time to first delirium occurrence (p = 0.22), nor delirium duration (p = 0.26). Days of mechanical ventilation (p = 0.80), ICU mortality (p = 0.55), and ICU patient disposition (p = 0.22) were similar in the two groups. The proportion of patients who developed corrected QT-interval prolongation (p = 0.16), extrapyramidal symptoms (p = 0.31), excessive sedation (p = 0.31), or new-onset hypotension (p = 1.0) that resulted in study drug discontinuation was comparable between the two groups.
Conclusions:
Low-dose scheduled haloperidol, initiated early in the ICU stay, does not prevent delirium and has little therapeutic advantage in mechanically ventilated, critically ill adults with subsyndromal delirium.


Related Concept Videos
 01:26
Psychosis: Goals of Pharmacotherapy
 01:28
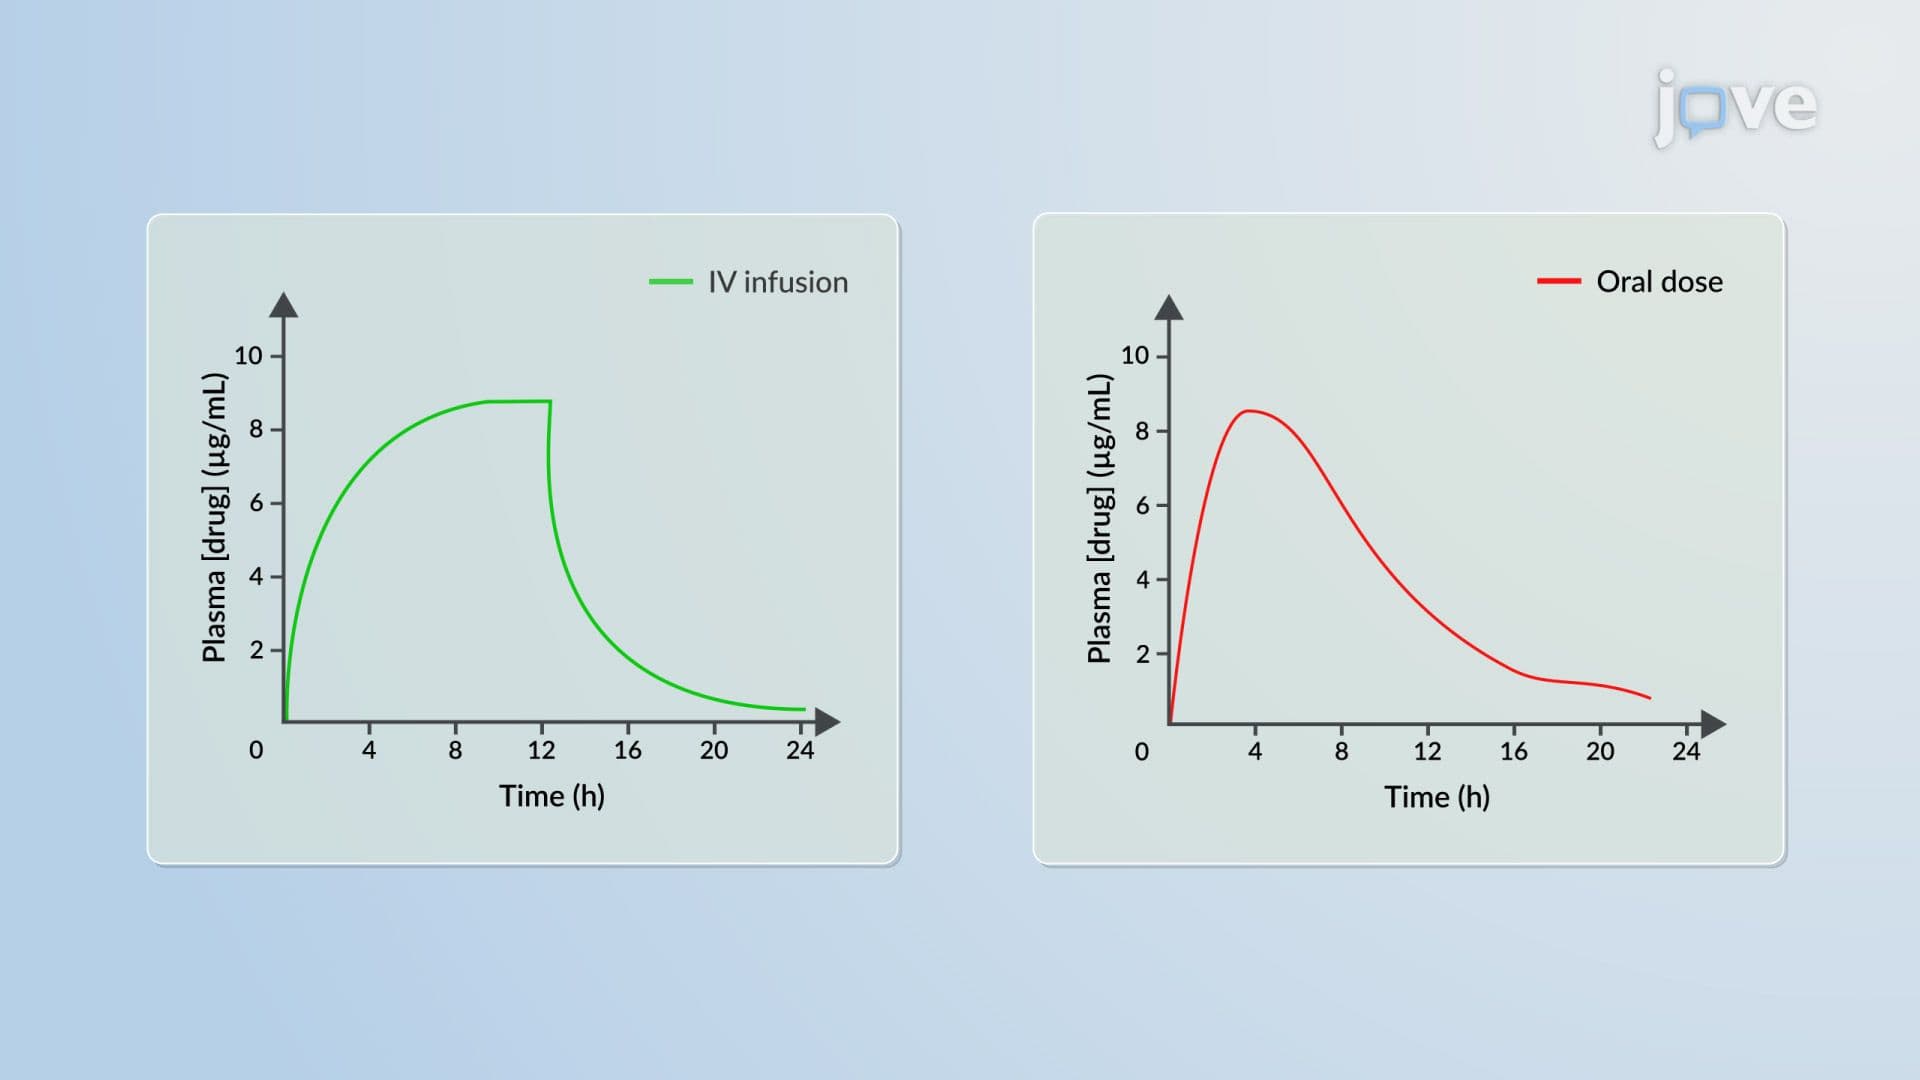
IV Infusion to Oral Dosing: Conversion Methods
 01:28
Psychosis and Antipsychotic Drugs: Overview
 01:28
Drug Therapy
Antianxiety Medications
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:28
Acute Coronary Syndrome IV: Interprofessional Care