Related Experiment Video
Updated: Mar 30, 2026

Robotic Central Pancreatectomy with Roux-en-Y Pancreaticojejunostomy
Published on: November 20, 2021
Total Laparoscopic Central Pancreatectomy with Pancreaticogastrostomy for High-Risk Cystic Neoplasm
L Schwarz1, J Fleming1, M Katz1
1Department of Surgical Oncology, The University of Texas MD Anderson Cancer Center, Houston, TX, USA.

Background:
Organ-sparing pancreatic resection is important in prophylactic surgery for cystic neoplasms. There is controversy regarding the optimal surgical approach for pancreatic lesions in the neck or proximal body of the pancreas. Central compared with distal pancreatectomy is technically more challenging, but preserves more functional pancreatic tissue. Because of the prophylactic nature of the surgery and long survival of patients with benign and borderline malignant lesions, surgeons need to stratify greater importance to surgical morbidity and sparing pancreatic parenchyma.
Patient:
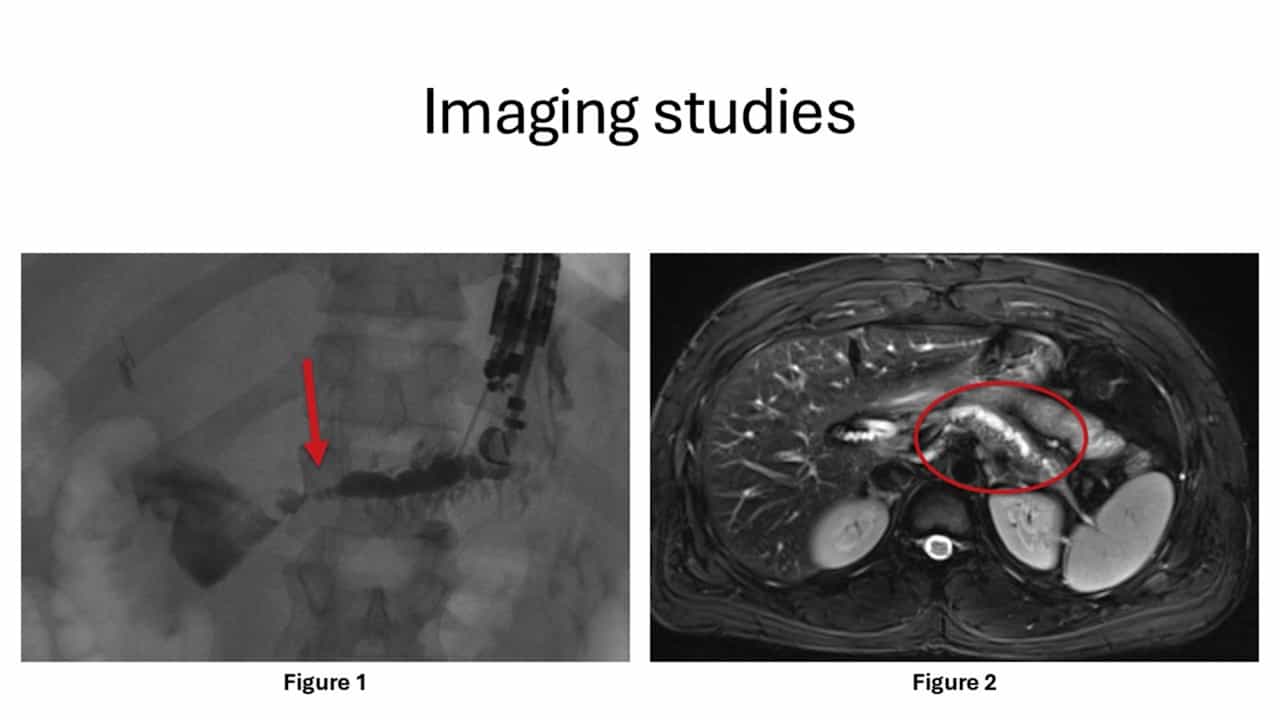
The patient is a 59-year-old active woman with a symptomatic cystic neoplasm of the pancreas exhibiting high-risk imaging features. The cyst of 2.2 × 1.8 cm in the body of the pancreas was impinging on the portal venous confluence.
Technique:
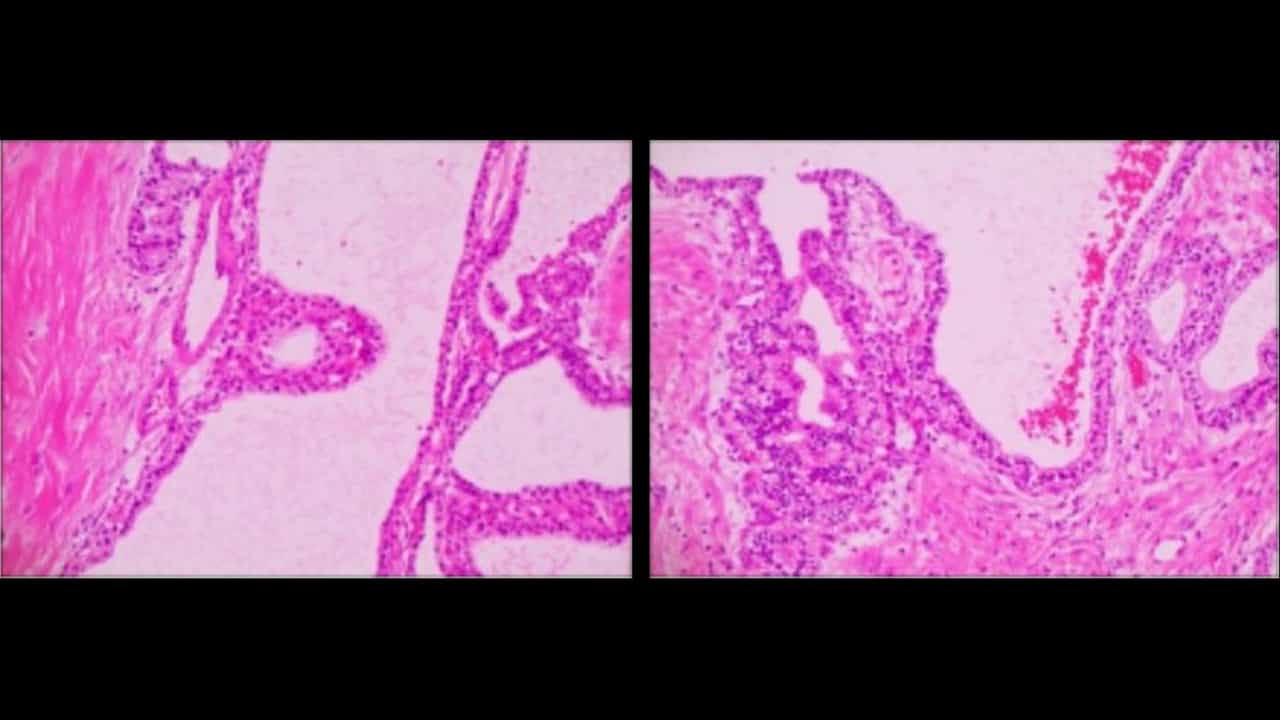
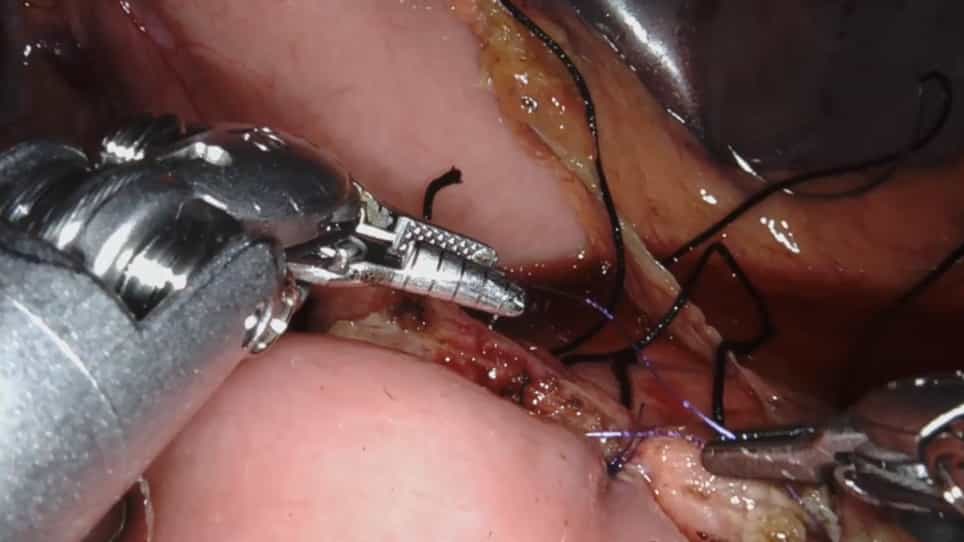
The patient was positioned in the French Position, the lesser sac was opened, and the pancreatic body exposed. A retropancreatic tunnel was created with staple division of the neck. The body was mobilized off the portal vein and splenic vessels transected. A retrogastric pancreaticogastrostomy was sewn through an anterior gastrotomy. The stent was delivered past the pylorus to decrease pancreatic enzymatic activation. Pathology demonstrated a mixed predominantly branch duct IPMN with multifocal high grade dysplasia and PanIN3.
Conclusions:
Laparoscopic ultrasound helps in defining cyst borders, and minimal blood loss optimizes visualization during the dissection. A minimally invasive pancreaticogastrostomy created through an anterior gastrotomy is technically feasible and safe. This approach can minimize the morbidity of prophylactic pancreatic surgery for patients with cystic neoplasms. Nevertheless, it should not compromise safety, oncologic completeness, or an organ-sparing approach.