Related Experiment Video
Updated: Mar 30, 2026
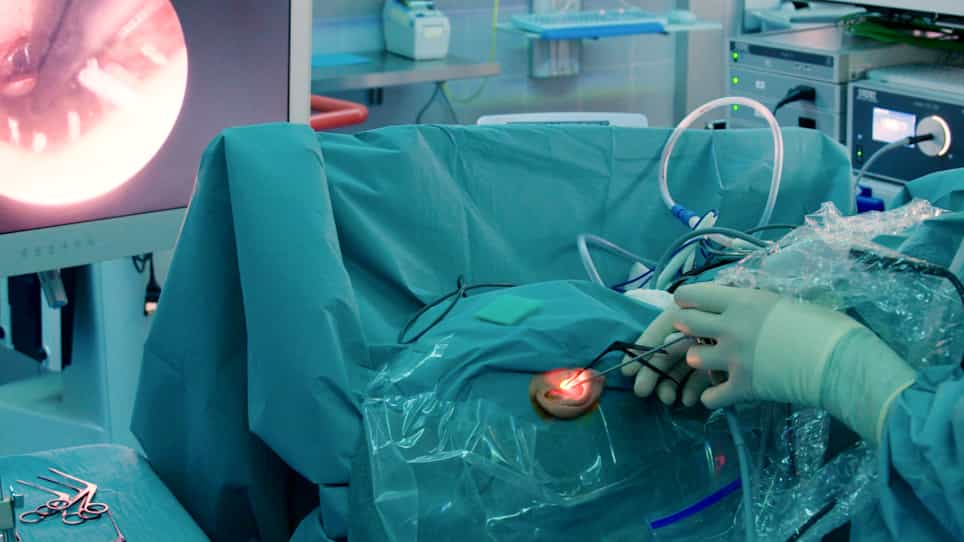

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Which technique is better for cholesteatoma surgery?

Objective:
The objective of this study was to evaluate the long-term surgical outcomes and recurrence rates of three surgical techniques that are commonly used for cholesteatoma.
Patients And Methods:
The hospital records of 132 patients with primary cholesteatoma who underwent surgery between January 1996 and December 2006 were evaluated retrospectively. Twelve cases had bilateral disease, and a total of 144 ears were treated. The patients were divided into three groups according to surgical technique: modified radical mastoidectomy (MRM) (n = 48 ears), radical mastoidectomy (RM) (n = 42 ears), and intact canal wall mastoidectomy (ICWM) (n = 54 ears). MRM and RM procedures are canal wall down (CWD) techniques, whereas the ICWM procedure is a canal wall up (CWU) technique. Postoperatively, all patients were followed up yearly for at least 6 years. The otomicroscopic features, cholesteatoma extension, surgical findings, and recurrence rates were compared in the groups.
Results:
Preoperative otomicroscopic examination showed attic retraction or perforation in 32% of the cases and central perforation in 11%. There was a higher cholesteatoma recurrence rate in the ICWM group than in the MRM and RM groups (p < 0.05), but there was also better hearing gain in the ICWM group (p < 0.05).
Conclusion:
There are several surgical techniques for eradicating cholesteatoma. Our study found that CWD procedures (RM, MRM) were more effective for the eradication of cholesteatoma, but hearing gain was better when a CWU technique was used. The choice of surgical technique should be individually tailored based on the pre-operative imaging and hearing examination findings.