Related Experiment Video
Updated: Mar 30, 2026
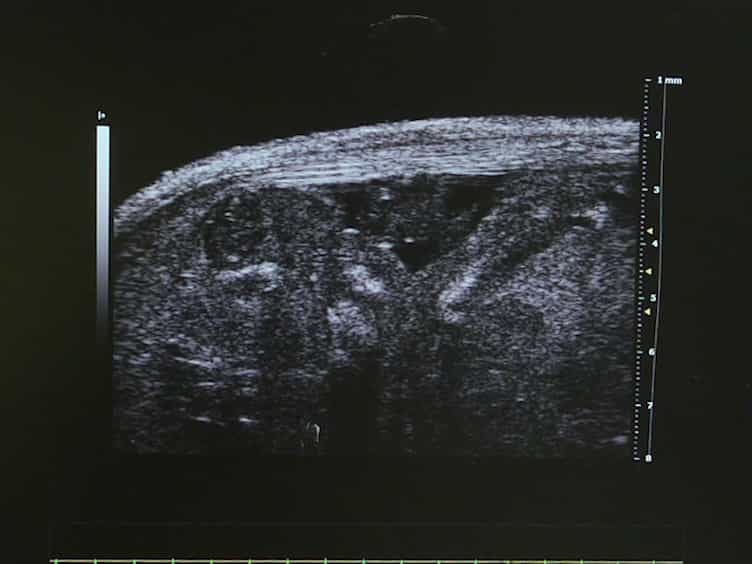
Fetal Mouse Cardiovascular Imaging Using a High-frequency Ultrasound 30/45MHZ System
Published on: May 5, 2018
Intermittent Auscultation in Labor: Could It Be Missing Many Pathological (Late) Fetal Heart Rate Decelerations?
1Department of Obstetrics and Gynaecology, Royal United Hospital NHS Foundation Trust, Bath, UK.

Intermittent auscultation (IA) of fetal heart rate (FHR) is recommended/preferred in low risk labors. Its usage even in developed countries is poised to increase because of perceived benefit of reduction in operative intervention and some disillusionment with the cardiotocography (CTG). Many national guidelines have stipulated regimes (frequency/timing) of IA based on level IV evidence. These tend to get faithfully and exactingly followed. It was observed that deliveries of many unexpectedly asphyxiated infants occurred despite rigorously performed and documented IA compliant with the guidelines. This triggered a reappraisal of the robustness of IA leading to this focused review supplemented by two anonymized cases. It concludes that the current methodology of IA may be flawed in that it poses a risk of missing many or most late (pathological) FHR decelerations, one of the foremost goals of IA. This is because many late decelerations reach their nadir before the end of the contraction. Thus the currently recommended auscultation of FHR for 60 seconds after the contraction by all national guidelines seemed to encompass their "recovery" phase and appeared to be misinterpreted as normal FHR or even as a reassuring accelerative pattern in the clinical practice. A recent recommendation of recording of the FHR as a single figure (rather than a range) does not remedy this anomaly and seems even less informative. It would be better to auscultate FHR before and after the contractions (or contraction to contraction) and take the FHR just before the contraction as the baseline FHR and interpret the FHR after contraction in the context of this baseline. This relatively simple improvement would detect most late FHR decelerations thus ameliorating the risk and significantly enhancing the patient safety.
Intermittent auscultation (IA) of fetal heart rate (FHR) is recommended/preferred in low risk labors. Its usage even in developed countries is poised to increase because of perceived benefit of reduction in operative intervention and some disillusionment with the cardiotocography (CTG). Many national guidelines have stipulated regimes (frequency/timing) of IA based on level IV evidence. These tend to get faithfully and exactingly followed. It was observed that deliveries of many unexpectedly asphyxiated infants occurred despite rigorously performed and documented IA compliant with the guidelines. This triggered a reappraisal of the robustness of IA leading to this focused review supplemented by two anonymized cases. It concludes that the current methodology of IA may be flawed in that it poses a risk of missing many or most late (pathological) FHR decelerations, one of the foremost goals of IA. This is because many late decelerations reach their nadir before the end of the contraction. Thus the currently recommended auscultation of FHR for 60 seconds after the contraction by all national guidelines seemed to encompass their "recovery" phase and appeared to be misinterpreted as normal FHR or even as a reassuring accelerative pattern in the clinical practice. A recent recommendation of recording of the FHR as a single figure (rather than a range) does not remedy this anomaly and seems even less informative. It would be better to auscultate FHR before and after the contractions (or contraction to contraction) and take the FHR just before the contraction as the baseline FHR and interpret the FHR after contraction in the context of this baseline. This relatively simple improvement would detect most late FHR decelerations thus ameliorating the risk and significantly enhancing the patient safety.
Related Concept Videos
 01:13
Special considerations while measuring pulse
 01:25
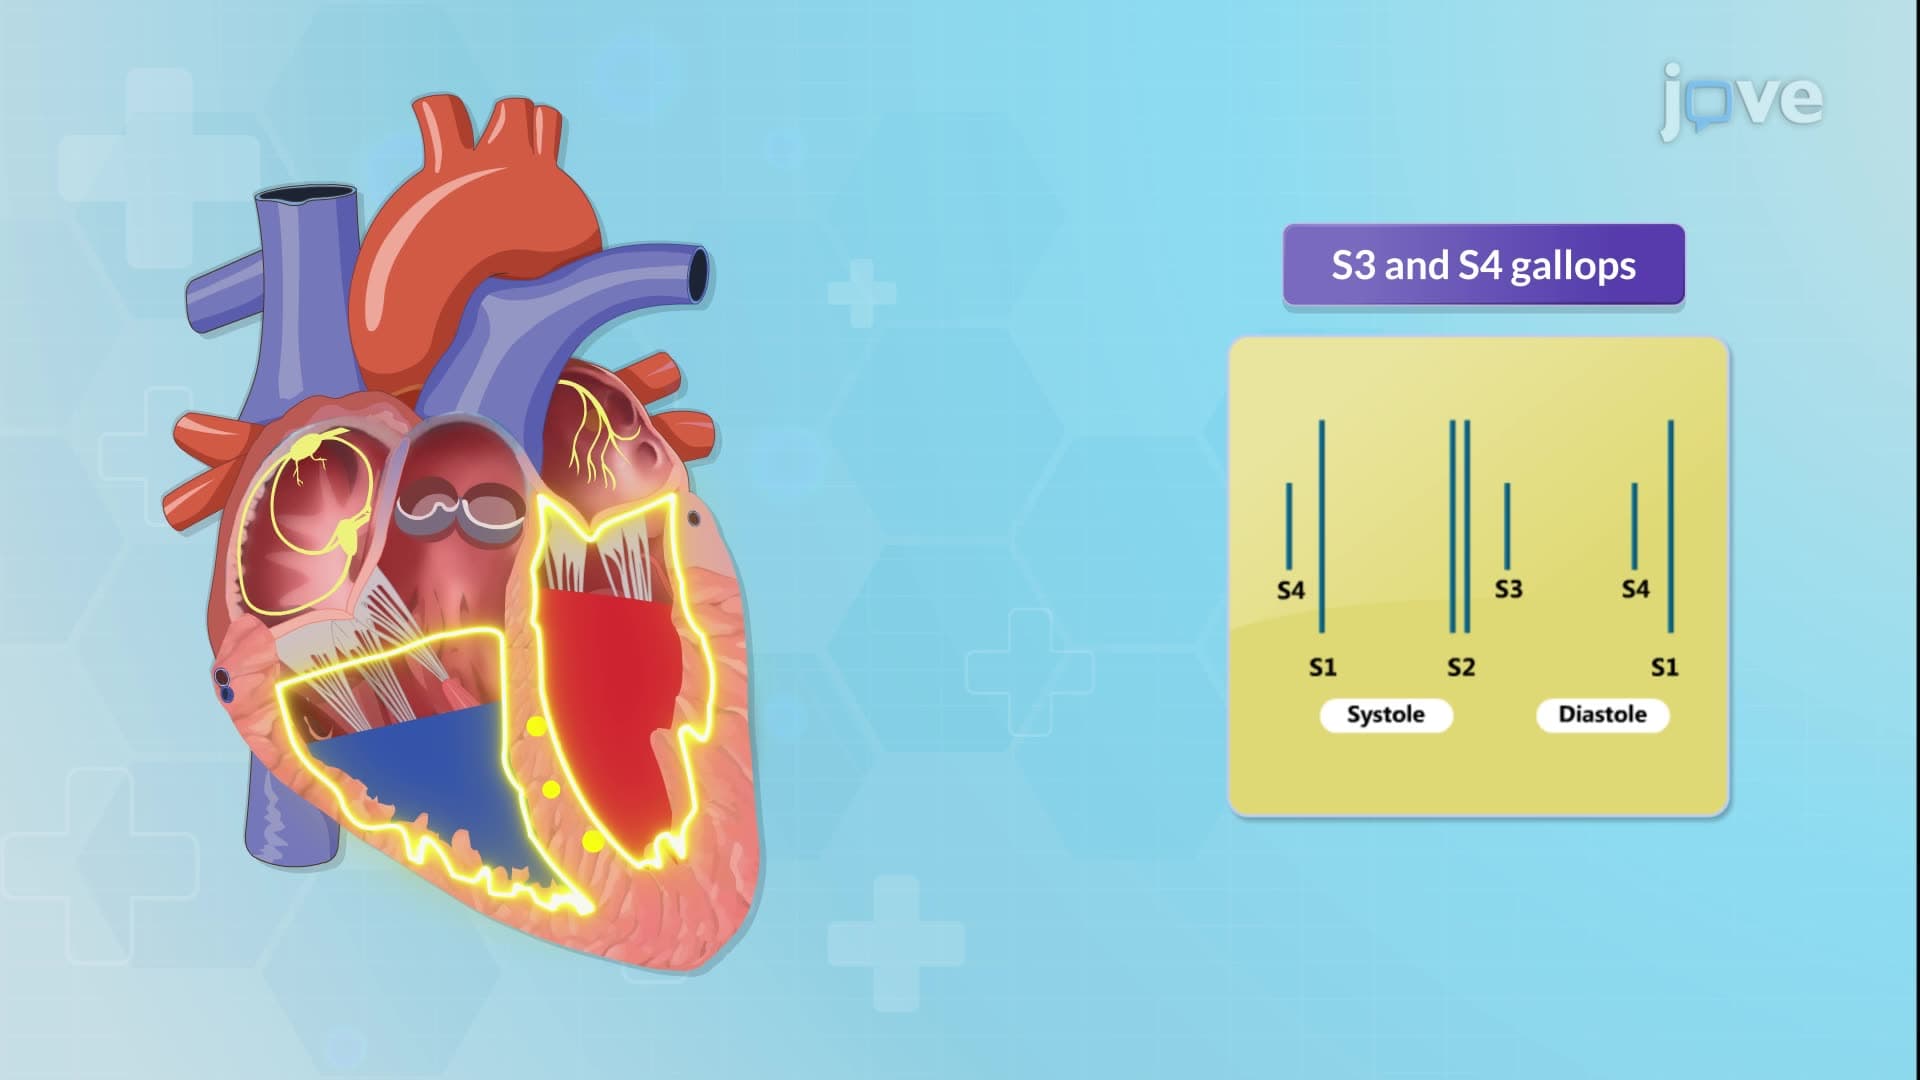
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:17
Assessment of apical pulse
Assessing the apical pulse is a critical nursing procedure, particularly indicated for: