Related Experiment Video
Updated: Mar 30, 2026
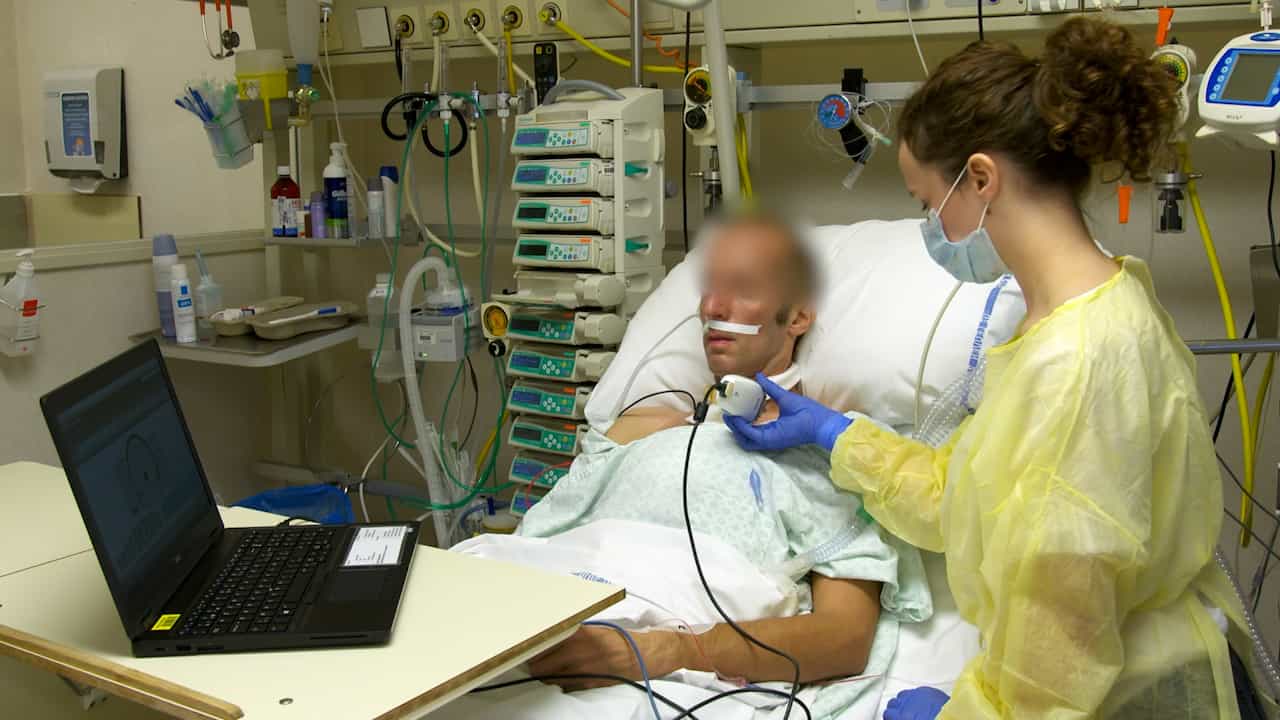

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Smart Care™ versus respiratory physiotherapy-driven manual weaning for critically ill adult patients: a randomized
Corinne Taniguchi1, Elivane S Victor2, Talita Pieri3
1Adult ICU, Hospital Israelita Albert Einstein, Avenida Albert Einstein, 627, 5 andar, São Paulo, SP, CEP:05652-900, Brazil. corinnetani@yahoo.com.br.

Introduction:
A recent meta-analysis showed that weaning with SmartCare™ (Dräger, Lübeck, Germany) significantly decreased weaning time in critically ill patients. However, its utility compared with respiratory physiotherapist-protocolized weaning is still a matter of debate. We hypothesized that weaning with SmartCare™ would be as effective as respiratory physiotherapy-driven weaning in critically ill patients.
Methods:
Adult critically ill patients mechanically ventilated for more than 24 hours in the adult intensive care unit of the Albert Einstein Hospital, São Paulo, Brazil, were randomly assigned to be weaned either by progressive discontinuation of pressure support ventilation (PSV) with SmartCare™. Demographic data, respiratory function parameters, level of PSV, tidal volume (VT), positive end-expiratory pressure (PEEP), inspired oxygen fraction (FIO2), peripheral oxygen saturation (SpO2), end-tidal carbon dioxide concentration (EtCO2) and airway occlusion pressure at 0.1 second (P0.1) were recorded at the beginning of the weaning process and before extubation. Mechanical ventilation time, weaning duration and rate of extubation failure were compared.
Results:
Seventy patients were enrolled 35 in each group. There was no difference between the two groups concerning age, sex or diagnosis at study entry. There was no difference in maximal inspiratory pressure, maximal expiratory pressure, forced vital capacity or rapid shallow breathing index at the beginning of the weaning trial. PEEP, VT, FIO2, SpO2, respiratory rate, EtCO2 and P0.1 were similar between the two groups, but PSV was not (median: 8 vs. 10 cmH2O; p =0.007). When the patients were ready for extubation, PSV (8 vs. 5 cmH2O; p =0.015) and PEEP (8 vs. 5 cmH2O; p <0.001) were significantly higher in the respiratory physiotherapy-driven weaning group. Total duration of mechanical ventilation (3.5 [2.0-7.3] days vs. 4.1 [2.7-7.1] days; p =0.467) and extubation failure (2 vs. 2; p =1.00) were similar between the two groups. Weaning duration was shorter in the respiratory physiotherapy-driven weaning group (60 [50-80] minutes vs. 110 [80-130] minutes; p <0.001).
Conclusion:
A respiratory physiotherapy-driven weaning protocol can decrease weaning time compared with an automatic system, as it takes into account individual weaning difficulties.
Trial Registration:
Clinicaltrials.gov Identifier: NCT02122016 . Date of Registration: 27 August 2013.


Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...