Related Experiment Video
Updated: Mar 30, 2026
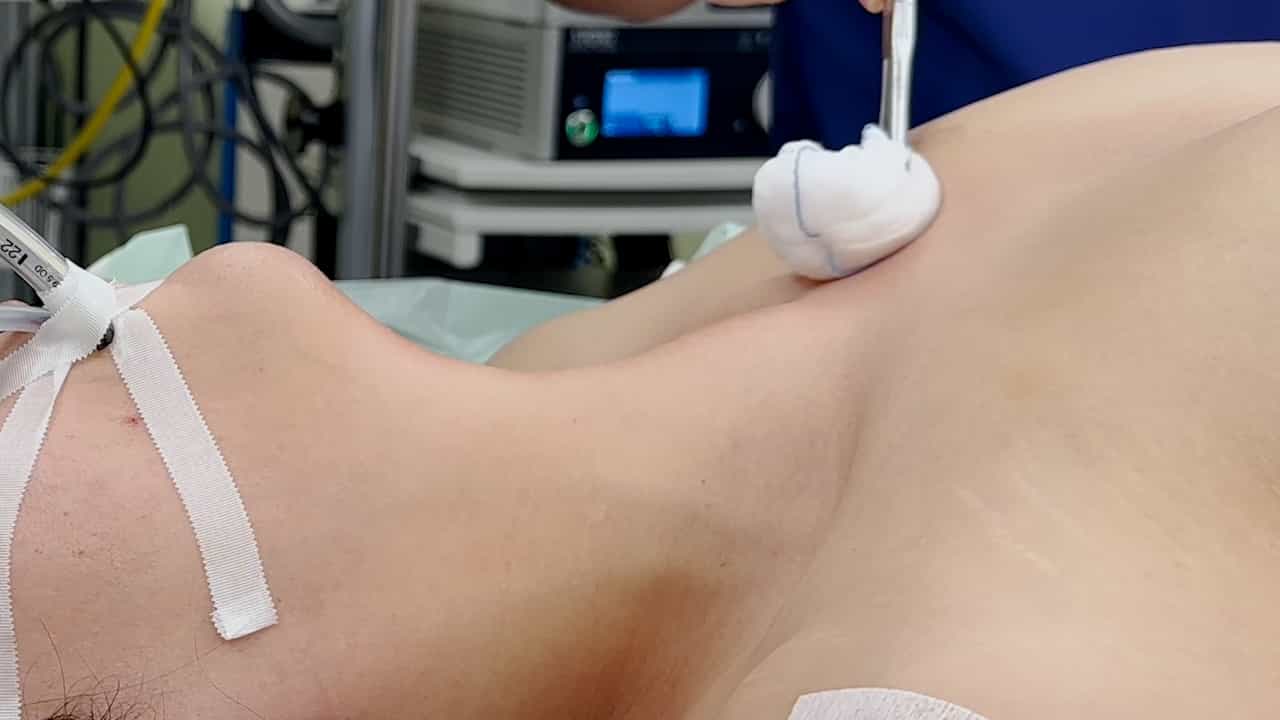
Minimal Invasive Resection of Large Retrosternal Thyroid Goiter
Published on: September 20, 2024
Rapid restoration of bone mass after surgical management of hyperthyroidism: A prospective case control study in
Poongkodi Karunakaran1, Chandrasekaran Maharajan2, Kamaludeen N Mohamed2
1Department of Endocrine surgery, Madras Medical College, Chennai, India; Department of General surgery, Government Mohankumaramangalam Medical College and Hospital, Salem, India.

Context:
The rate and the extent of bone remineralization at cancellous versus cortical sites after treatment of hyperthyroidism is unclear. Few studies have examined the effect of operative management of hyperthyroidism on recovery of bone mass.
Objective:
To evaluate prospectively the bone mineral density (BMD), bone mineral content (BMC), and bone areal size at the spine, hip, and forearm before and after total thyroidectomy.
Design And Setting:
A prospective case control observational study from August 2011 to July 2014 in a single center.
Participants:
This study evaluated 40 overt hyperthyroid patients and 31 age-matched euthyroid controls who were operative candidates.
Main Outcome Measures:
Bone indices were measured at baseline and 6-month postoperatively using dual energy x-ray absorptiometry. Serum levels of alkaline phosphatase and 25-hydroxy vitamin D3 (25OHD) were assessed.
Results:
Baseline BMD of hyperthyroid subjects at the spine, hip, and forearm were less than euthyroid controls (P = .001) with concomitant increases in serum alkaline phosphatase (mean ± SD, 143 ± 72 vs 72 ± 23 IU/L control; P < .001). The 25OHD level was 24.3 ± 10.6 and 26.1 ± 14.6 ng/mL in patients and controls, respectively. Among hyperthyroid patients, posttreatment BMD expressed as g/cm(2) were 0.97 ± 0.12 (vs pretreatment 0.91 ± 0.14; P = .001) at the spine, 0.87 ± 0.12 (vs pretreatment 0.80 ± 0.13; P = .001) at the hip, and 0.67 ± 0.09 (vs pretreatment 0.64 ± 0.11; P = .191) at the forearm. The percent change in BMD was greatest at spine (8.3%) followed by the hip (7.6%) and forearm (3.0%).
Conclusion:
Operative management with total thyroidectomy improved the bone loss associated with hyperthyroidism as early as 6 months postoperatively at the hip and spine despite concomitant vitamin D deficiency. Delayed recovery of bone indices at the forearm, a cortical bone, requires further long-term evaluation.
Related Concept Videos
 01:40
Bone Remodeling
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:21
Skeleton and Calcium Homeostasis
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:31
Osteoclasts in Bone Remodeling