Related Experiment Video
Updated: Mar 30, 2026


Author Spotlight: Recent Advancements in Reoperative Foregut Surgery
Published on: September 22, 2023
Collis-Nissen gastroplasty for short oesophagus
Sandro Mattioli1, Marialuisa Lugaresi2, Alberto Ruffato2
1Division of Thoracic Surgery, Centre for the Study and Research on Diseases of the Esophagus, Alma Mater Studiorum - University of Bologna, GVM Care and Research, Cotignola, Italy Department of Medical and Surgical Sciences (DIMEC), Alma Mater Studiorum - University of Bologna, Bologna, Italy PhD Course in Cardio-Nephro-Thoracic Sciences, Alma Mater Studiorum - University of Bologna, Bologna, Italy sandro.mattioli@unibo.it.

Abstract:
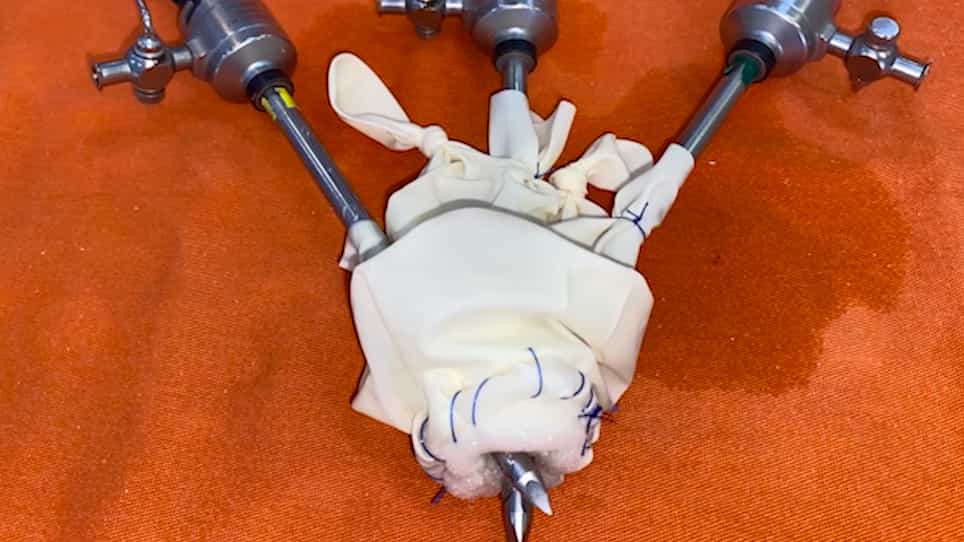
The Collis-Nissen procedure is performed for the surgical treatment of 'true short oesophagus'. When this condition is strongly suspected radiologically, the patient is placed in the 45° left lateral position on the operating table with the left chest and arm lifted to perform a thoracostomy in the V-VI space, posterior to the axillary line. The hiatus is opened and the distal oesophagus is widely mobilized. With intraoperative endoscopy, the position of the oesophago-gastric junction in relationship to the hiatus is determined and the measurement of the length of the intra-abdominal oesophagus is performed to decide either to carry out a standard anti-reflux procedure or to lengthen the oesophagus. If the oesophagus is irreversibly short ('true short oesophagus'), the short gastric vessels are divided and the gastric fundus is mobilized. An endostapler is introduced into the left chest. The left thoracoscopic approach is suitable to control effectively the otherwise blind passage of the endostapler into the mediastinum and upper abdomen (if a second optic is not used). The tip of the stapler is clearly visible while 'walking' on the left diaphragm. The Collis gastroplasty is performed over a 46 Maloney bougie. A floppy Nissen fundoplication and the hiatoplasty complete the procedure.

Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...