Related Experiment Video
Updated: Mar 29, 2026


Intracranial Pressure Monitoring In Nontraumatic Intraventricular Hemorrhage Rodent Model
Published on: February 8, 2022
New Insights into Blood Pressure Control for Intracerebral Haemorrhage

Although blood pressure (BP) levels may rise in the weeks preceding intracerebral haemorrhage (ICH), in contrast to findings in the ischaemic stroke population, the initial post-ICH BP is often much higher than the last pre-morbid level. Elevated BP is therefore common in acute ICH, often with markedly elevated levels, and is associated with poor outcomes, though the exact pathophysiological mechanisms remain unclear. The Antihypertensive Treatment of Acute Cerebral Haemorrhage (ATACH) trial and the INTEnsive blood pressure Reduction in Acute Cerebral haemorrhage Trial (INTERACT) demonstrated that early and intensive lowering of elevated BP in the acute ICH period is feasible and safe. Importantly, recent CT perfusion studies have shown that early, intense BP reduction does not reduce cerebral blood flow or promote cerebral ischaemia. The recent, large INTERACT2 trial confirmed the safety of early BP lowering in ICH and suggested that intensive target-driven BP reduction may improve outcomes, with a non-significant trend towards reduced death and major disability and a significant favourable shift of scores on the modified Rankin scale compared with guideline-based treatment. BP lowering in acute ICH may reduce haematoma growth, particularly when target levels are achieved early and are sustained, though the evidence is partly conflicting. Other aspects of BP may also be important following acute ICH, with maximum systolic BP and systolic BP variability being independent predictors of poor outcomes in a recent study. This chapter gives an overview of the current evidence regarding BP in ICH and covers the following topics: the incidence of elevated BP in acute ICH and the patterns of BP observed before and after the event; the effect of elevated BP on outcomes in ICH and the potential underlying pathophysiological mechanisms; the safety and feasibility of BP lowering; the effects of BP lowering on clinical and radiological outcomes; other important aspects of BP in ICH; and the choice of antihypertensive agent.
Although blood pressure (BP) levels may rise in the weeks preceding intracerebral haemorrhage (ICH), in contrast to findings in the ischaemic stroke population, the initial post-ICH BP is often much higher than the last pre-morbid level. Elevated BP is therefore common in acute ICH, often with markedly elevated levels, and is associated with poor outcomes, though the exact pathophysiological mechanisms remain unclear. The Antihypertensive Treatment of Acute Cerebral Haemorrhage (ATACH) trial and the INTEnsive blood pressure Reduction in Acute Cerebral haemorrhage Trial (INTERACT) demonstrated that early and intensive lowering of elevated BP in the acute ICH period is feasible and safe. Importantly, recent CT perfusion studies have shown that early, intense BP reduction does not reduce cerebral blood flow or promote cerebral ischaemia. The recent, large INTERACT2 trial confirmed the safety of early BP lowering in ICH and suggested that intensive target-driven BP reduction may improve outcomes, with a non-significant trend towards reduced death and major disability and a significant favourable shift of scores on the modified Rankin scale compared with guideline-based treatment. BP lowering in acute ICH may reduce haematoma growth, particularly when target levels are achieved early and are sustained, though the evidence is partly conflicting. Other aspects of BP may also be important following acute ICH, with maximum systolic BP and systolic BP variability being independent predictors of poor outcomes in a recent study. This chapter gives an overview of the current evidence regarding BP in ICH and covers the following topics: the incidence of elevated BP in acute ICH and the patterns of BP observed before and after the event; the effect of elevated BP on outcomes in ICH and the potential underlying pathophysiological mechanisms; the safety and feasibility of BP lowering; the effects of BP lowering on clinical and radiological outcomes; other important aspects of BP in ICH; and the choice of antihypertensive agent.

Related Concept Videos
 01:30
Blood Pressure
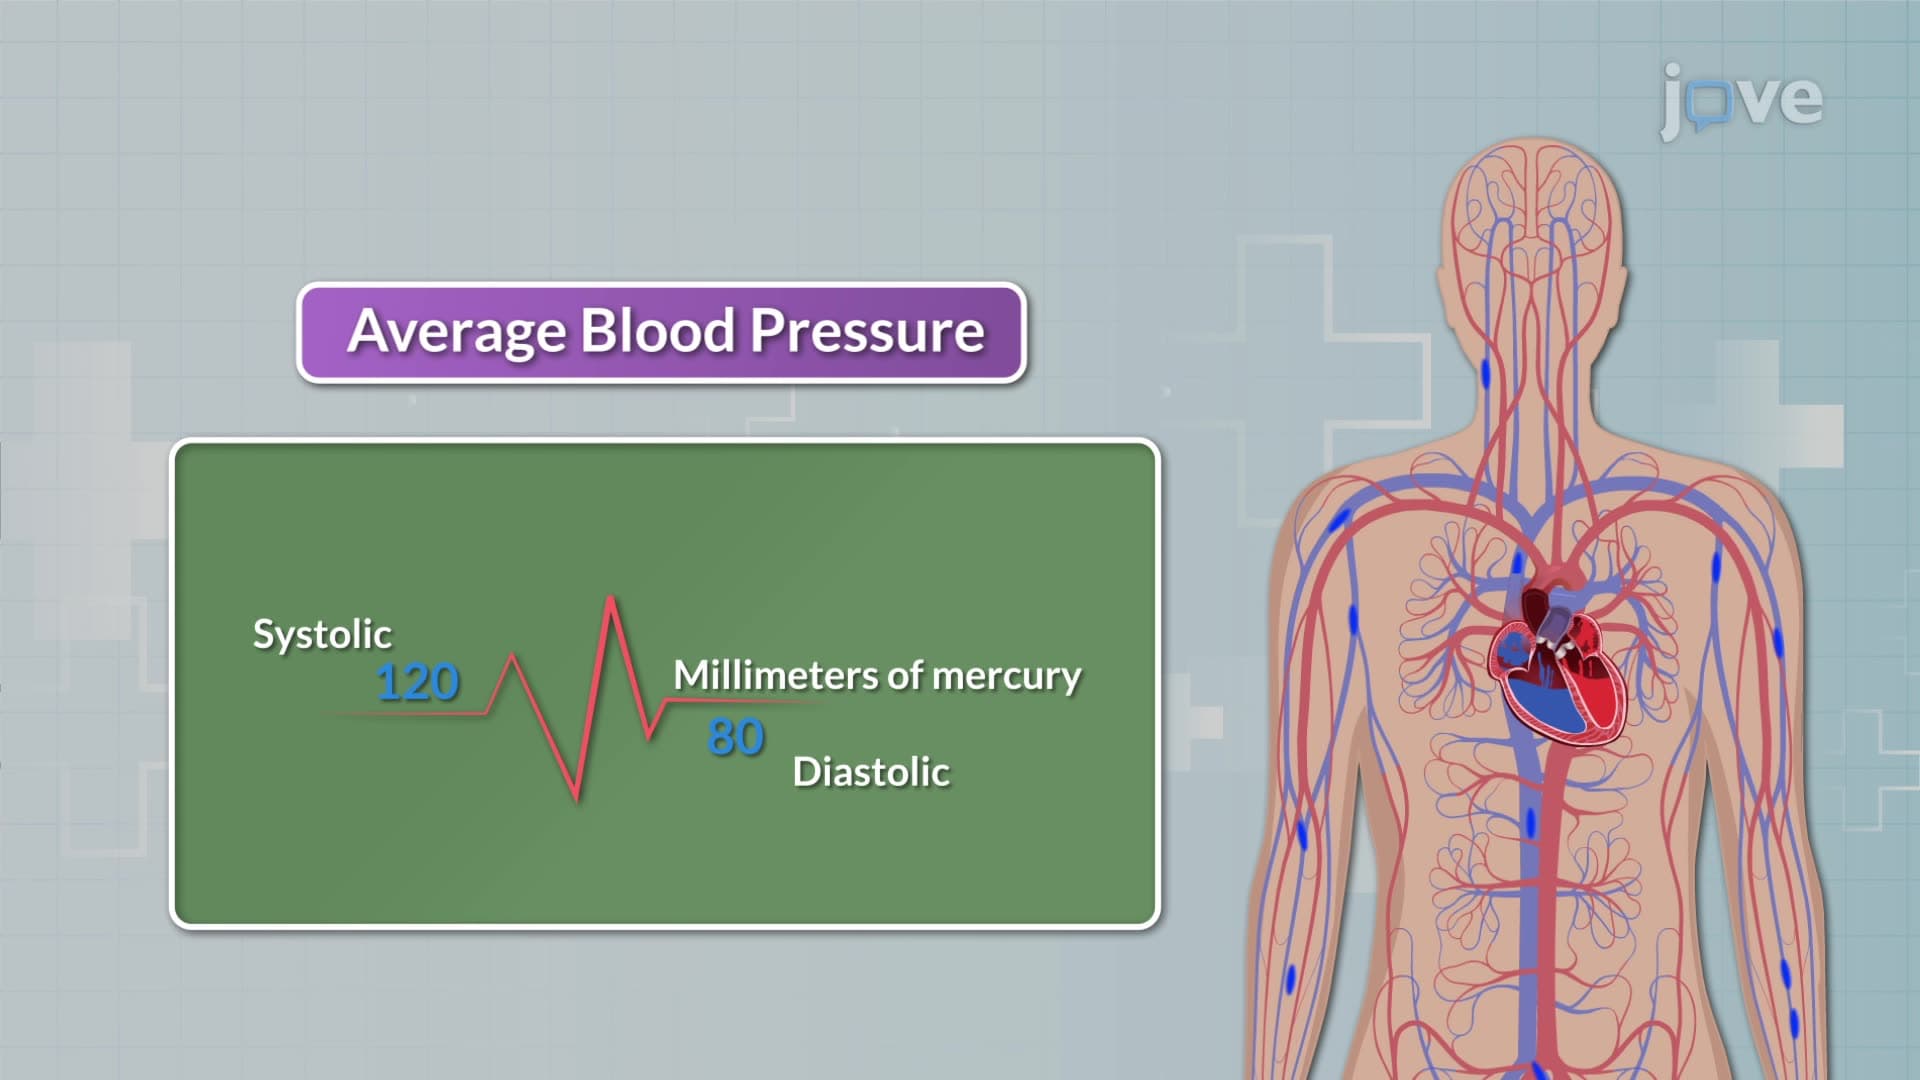
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:24
Blood Pressure
 01:18
Hypertension and Regulation of Blood Pressure
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:18
Neural Regulation of Blood Pressure
Baroreceptor Reflex
Baroreceptors, located in the carotid sinuses and aortic arch, detect changes in blood pressure. When blood pressure rises, these stretch-sensitive receptors...