Related Experiment Video
Updated: Mar 29, 2026
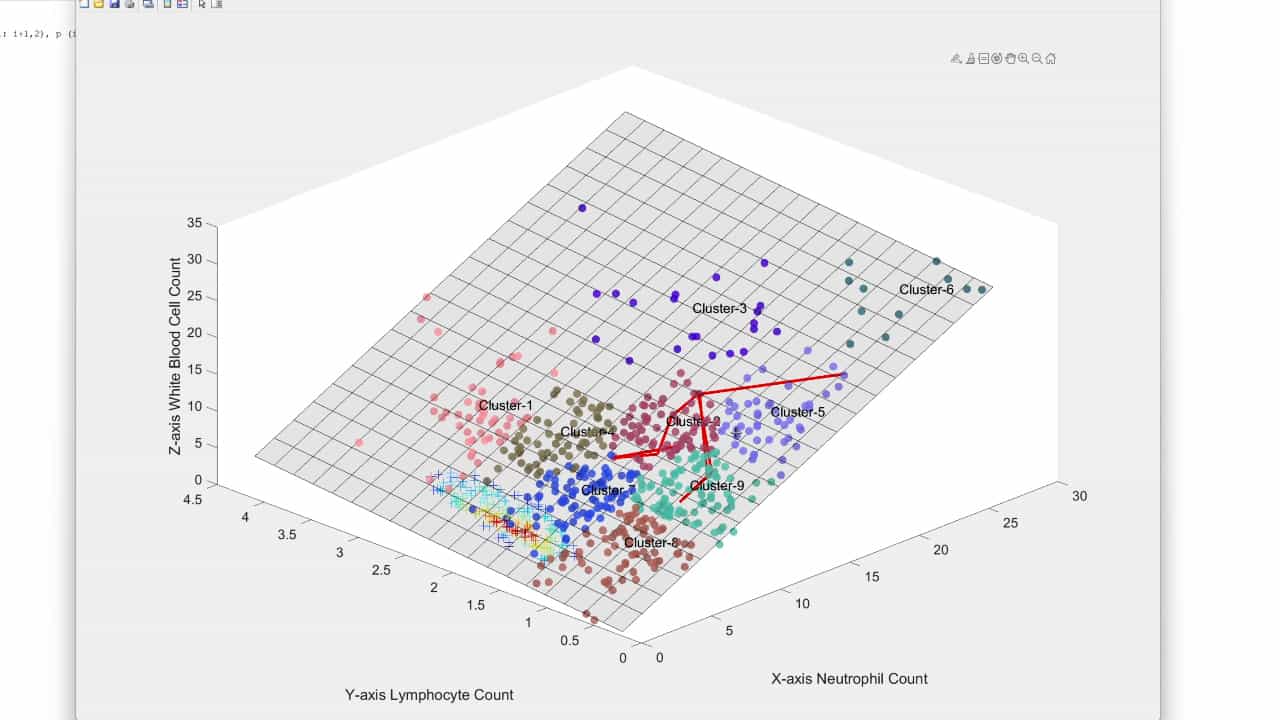

A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Temporal trends in the systemic inflammatory response syndrome, sepsis, and medical coding of sepsis
Benjamin S Thomas1,2, S Reza Jafarzadeh3, David K Warren4
1Division of Infectious Diseases, Department of Medicine, Washington University School of Medicine, 660 South Euclid Avenue, Campus Box 8051, St. Louis, MO, 63110, USA. bthomas@dom.wustl.edu.

Background:
Recent reports using administrative claims data suggest the incidence of community- and hospital-onset sepsis is increasing. Whether this reflects changing epidemiology, more effective diagnostic methods, or changes in physician documentation and medical coding practices is unclear.
Methods:
We performed a temporal-trend study from 2008 to 2012 using administrative claims data and patient-level clinical data of adult patients admitted to Barnes-Jewish Hospital in St. Louis, Missouri. Temporal-trend and annual percent change were estimated using regression models with autoregressive integrated moving average errors.
Results:
We analyzed 62,261 inpatient admissions during the 5-year study period. 'Any SIRS' (i.e., SIRS on a single calendar day during the hospitalization) and 'multi-day SIRS' (i.e., SIRS on 3 or more calendar days), which both use patient-level data, and medical coding for sepsis (i.e., ICD-9-CM discharge diagnosis codes 995.91, 995.92, or 785.52) were present in 35.3 %, 17.3 %, and 3.3 % of admissions, respectively. The incidence of admissions coded for sepsis increased 9.7 % (95 % CI: 6.1, 13.4) per year, while the patient data-defined events of 'any SIRS' decreased by 1.8 % (95 % CI: -3.2, -0.5) and 'multi-day SIRS' did not change significantly over the study period. Clinically-defined sepsis (defined as SIRS plus bacteremia) and severe sepsis (defined as SIRS plus hypotension and bacteremia) decreased at statistically significant rates of 5.7 % (95 % CI: -9.0, -2.4) and 8.6 % (95 % CI: -4.4, -12.6) annually. All-cause mortality, SIRS mortality, and SIRS and clinically-defined sepsis case fatality did not change significantly during the study period. Sepsis mortality, based on ICD-9-CM codes, however, increased by 8.8 % (95 % CI: 1.9, 16.2) annually.
Conclusions:
The incidence of sepsis, defined by ICD-9-CM codes, and sepsis mortality increased steadily without a concomitant increase in SIRS or clinically-defined sepsis. Our results highlight the need to develop strategies to integrate clinical patient-level data with administrative data to draw more accurate conclusions about the epidemiology of sepsis.


Related Concept Videos
 01:14
SBAR II: Application of SBAR
SBAR Report from a Nurse to a Health Care Provider
S: "Hello, Dr. Smith. This is Jane, RN, from the Med Surg unit. I am calling to tell you about Ms. White in Room 210, who is experiencing increased pain and redness at her incision site. Her recent...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:26
Guidelines for Nursing Documentation II
Timely documentation is crucial to ensure continuity of care for patients. Any delays in recording or reporting medical information can result in medical errors and even adverse patient outcomes. From medication administration to diagnostic test results, every detail must be accurately and promptly documented to provide the best possible care for patients.
 01:29
Issues And Trends In Healthcare Delivery System
Cost Containment
Payment for healthcare services has historically promoted adoption of costly and often unnecessary or inefficient...
 01:29
Staphylococcal Skin Infections
 01:24
Data Reporting and Recording