Related Experiment Video
Updated: Mar 29, 2026

Inverse Probability of Treatment Weighting Propensity Score using the Military Health System Data Repository and National Death Index
Published on: January 8, 2020
Estimating the value of medical treatments to patients using probabilistic multi criteria decision analysis
Henk Broekhuizen1, Catharina G M Groothuis-Oudshoorn2, A Brett Hauber3
1Department of Health Technology and Services Research, MIRA Institute, University of Twente, Enschede, The Netherlands. h.broekhuizen@utwente.nl.

Background:
Estimating the value of medical treatments to patients is an essential part of healthcare decision making, but is mostly done implicitly and without consulting patients. Multi criteria decision analysis (MCDA) has been proposed for the valuation task, while stated preference studies are increasingly used to measure patient preferences. In this study we propose a methodology for using stated preferences to weigh clinical evidence in an MCDA model that includes uncertainty in both patient preferences and clinical evidence explicitly.
Methods:
A probabilistic MCDA model with an additive value function was developed and illustrated using a case on hypothetical treatments for depression. The patient-weighted values were approximated with Monte Carlo simulations and compared to expert-weighted results. Decision uncertainty was calculated as the probability of rank reversal for the first rank. Furthermore, scenario analyses were done to assess the relative impact of uncertainty in preferences and clinical evidence, and of assuming uniform preference distributions.
Results:
The patient-weighted values for drug A, drug B, drug C, and placebo were 0.51 (95% CI: 0.48 to 0.54), 0.51 (95% CI: 0.48 to 0.54), 0.54 (0.49 to 0.58), and 0.15 (95% CI: 0.13 to 0.17), respectively. Drug C was the most preferred treatment and the rank reversal probability for first rank was 27%. This probability decreased to 18% when uncertainty in performances was not included and increased to 41% when uncertainty in criterion weights was not included. With uniform preference distributions, the first rank reversal probability increased to 61%. The expert-weighted values for drug A, drug B, drug C, and placebo were 0.67 (95% CI: 0.65 to 0.68), 0.57 (95% CI: 0.56 to 0.59), 0.67 (95% CI: 0.61 to 0.71), and 0.19 (95% CI: 0.17 to 0.21). The rank reversal probability for the first rank according to experts was 49%.
Conclusions:
Preferences elicited from patients can be used to weigh clinical evidence in a probabilistic MCDA model. The resulting treatment values can be contrasted to results from experts, and the impact of uncertainty can be quantified using rank probabilities. Future research should focus on integrating the model with regulatory decision frameworks and on including other types of uncertainty.
More Related Videos
 06:16
Signal Acquisition, Score Interpretation, and Economics of a Non-Invasive Point-of-Care Test for Coronary Artery Disease
Published on: August 9, 2024
 13:04
Measuring the Subjective Value of Risky and Ambiguous Options using Experimental Economics and Functional MRI Methods
Published on: September 19, 2012
Related Concept Videos
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:09
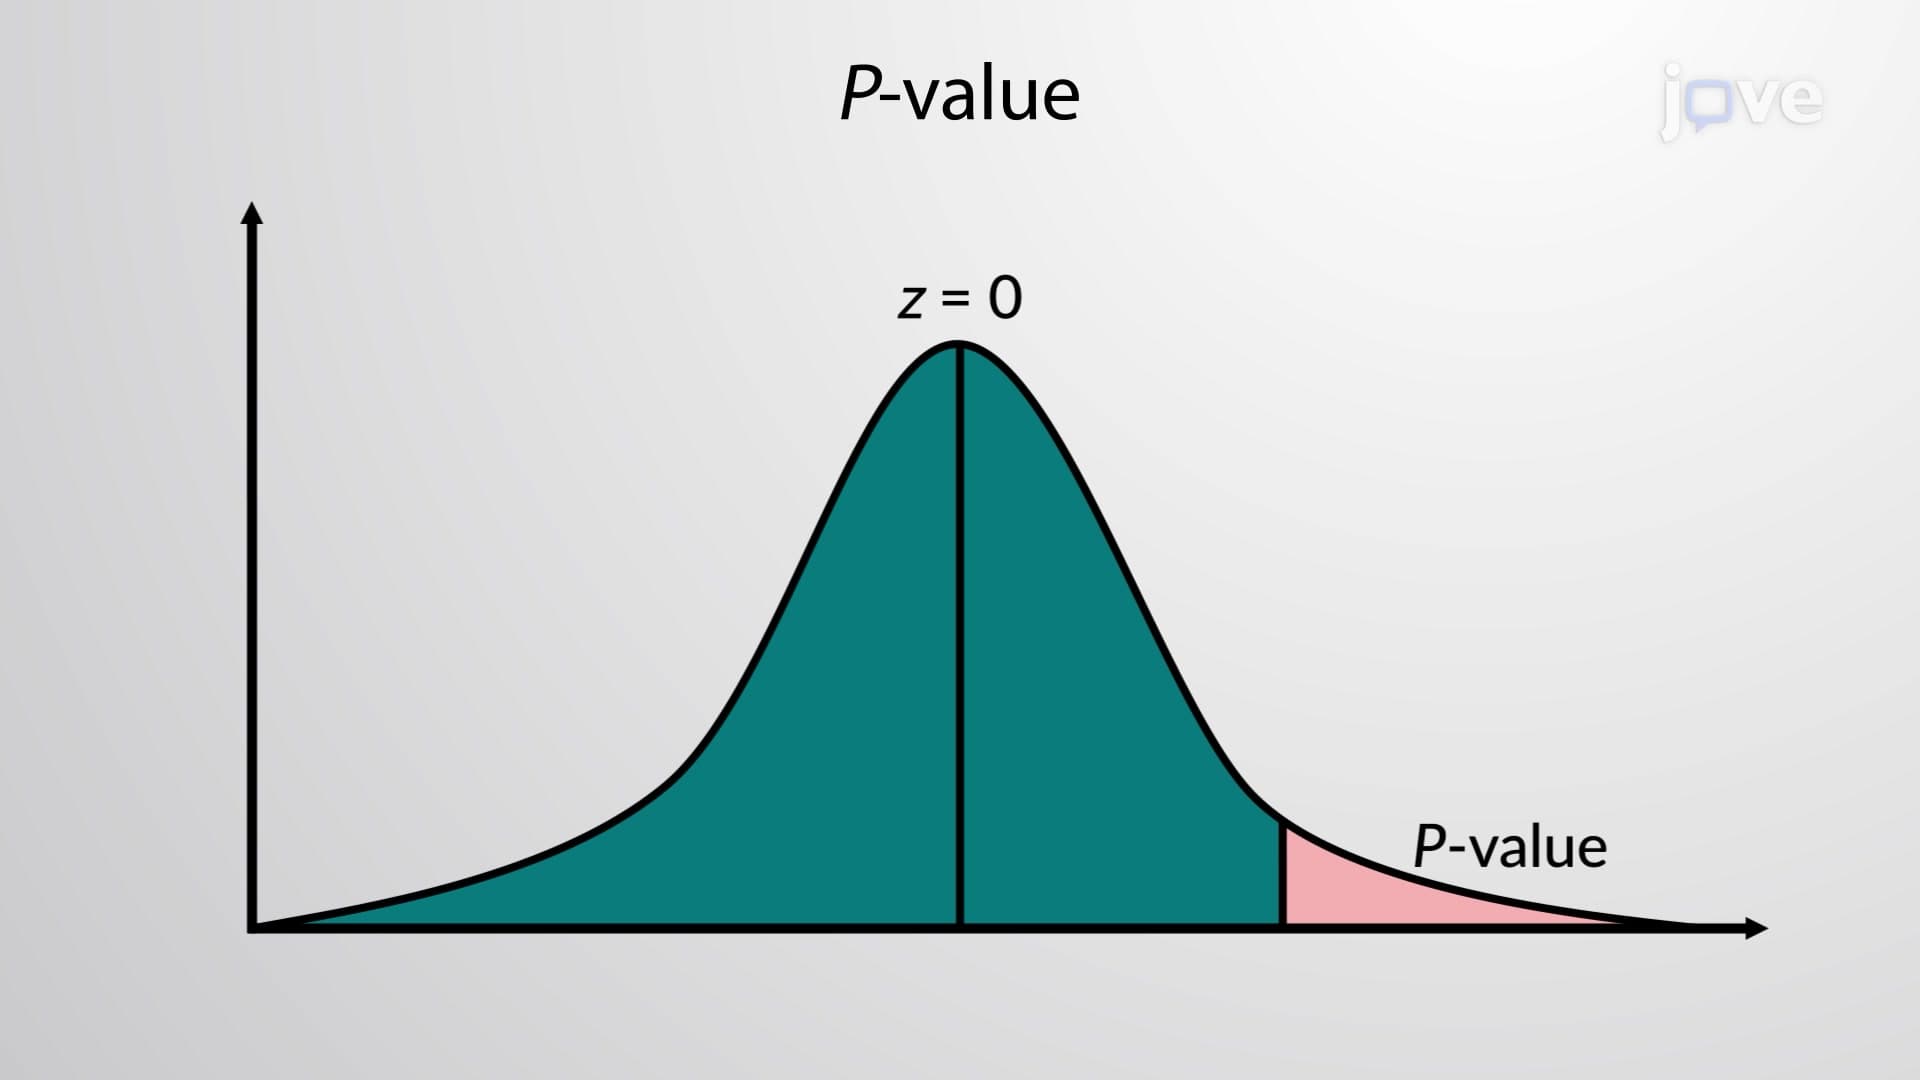
Decision Making: P-value Method
First, a specific claim about the population parameter is proposed. The claim is based on the research question and is stated in a simple form. Further, an opposing statement to the claim is also stated. These statements can act as null and alternative hypotheses: a null hypothesis would be a neutral statement while the alternative hypothesis can...
 01:15
Methods of Documentation VI: Case Management Model
For example, a patient with a chronic...
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:21
Cancer Survival Analysis
 01:27
Ethical Issues
Ethical Concerns in Healthcare: