Related Experiment Video
Updated: Mar 29, 2026
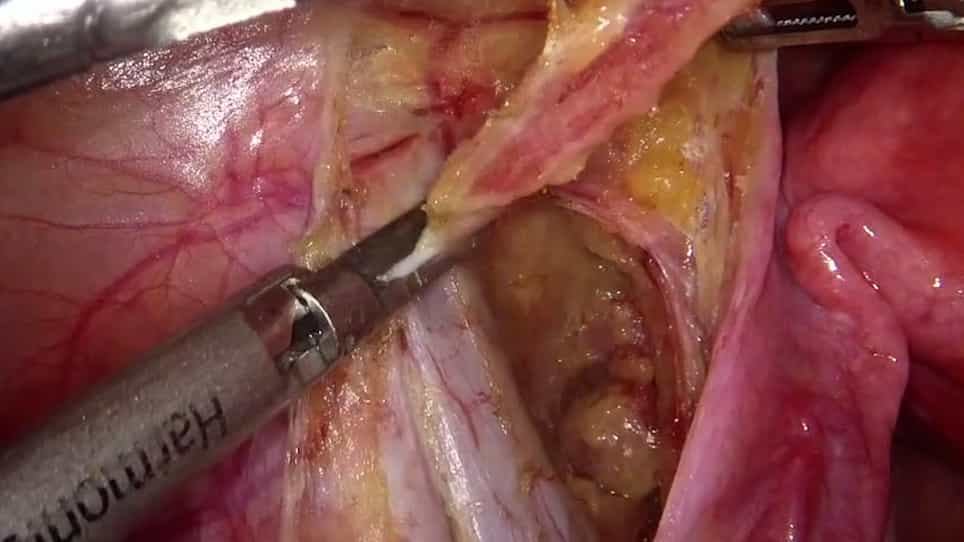
Sentinel Lymph Node Mapping and Biopsy for Endometrial Cancer at Early Stage with Laparoscopy
Published on: August 19, 2021
Application of a Pattern-based Classification System for Invasive Endocervical Adenocarcinoma in Cervical Biopsy,
Bojana Djordjevic1, Carlos Parra-Herran
1Department of Pathology and Laboratory Medicine, University of Ottawa, The Ottawa Hospital, Ottawa, ON, Canada.

Abstract:
A pattern-based classification system has been recently proposed for invasive endocervical adenocarcinoma, which is predictive of the risk of nodal metastases. Identifying cases at risk of nodal involvement is most relevant at the time of biopsy and loop electrosurgical excision procedure (LEEP) to allow for optimal surgical planning, and, most importantly, consideration of lymphadenectomy. This study aims to determine the topography of patterns of stromal invasion in invasive endocervical adenocarcinoma with emphasis on patterns in biopsy, cone, and LEEP. Invasive pattern was assessed following the pattern-based classification (Patterns A, B, and C) in 47 invasive endocervical adenocarcinomas treated with hysterectomy or trachelectomy and correlated with pattern of invasion at the tumor surface (2 mm of tumor depth) and on preoperative biopsy and cone/LEEP. Patterns A, B, and C were present in 21.3%, 36.2%, and 42.5% of cases, respectively. Most pattern A cases were Stage IA (90%), whereas most Pattern B and C cases were Stage IB (76.5% and 80%, respectively). Horizontal spread was on average larger in Pattern C (24.1 mm) than in Patterns A and B (7.7 and 12.3 mm, respectively). Pattern at the tumor surface correlated with the overall pattern in 95.7% of cases. Concordance between patterns at cone/LEEP and hysterectomy was 92.8%; the only discrepant case was upgraded from Pattern A on LEEP to C on final excision. Agreement between patterns in biopsy and the overall tumor, however, was only 37.5%. In all discrepant cases, biopsy failed to reveal destructive invasion, which was evident on excision. All discrepant biopsies with pattern A showed glandular complexity resembling exophytic papillary growth but did not meet criteria for destructive invasion. On excision, marked gland confluence with papillary architecture was evident. We conclude that the pattern of invasion on cone/LEEP is a good predictor of pattern of invasion on hysterectomy, particularly if there is destructive invasion (B or C). Thus, pattern-based classification can be successfully applied in these samples to guide definitive surgical treatment. Prediction of the overall pattern based on biopsy material alone appears to be suboptimal. However, glandular confluence and complexity on biopsy, regardless of its size, appears to be associated with destructive invasion in the overall tumor.
More Related Videos
 07:13
Comparison of Predictive Performance of Three Lymph Node Staging Systems in Colorectal Signet Ring Cell Carcinoma Based on Machine Learning Model
Published on: April 18, 2025
 06:57
Chromogenic In Situ Hybridization as a Tool for HPV-Related Head and Neck Cancer Diagnosis
Published on: June 14, 2019