Related Concept Videos

Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment01:08

Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment

Hepatic impairment, characterized by decreased liver function, does not uniformly mandate adjustments in drug dosage. Whether dosage modifications are necessary depends on various factors related to the drug's metabolism and elimination pathways. If a drug is primarily excreted via the kidneys and bypasses significant hepatic processing, if it undergoes minimal metabolic transformation in the liver, or if it is volatile and primarily expelled through the lungs, dose adjustments may not be...
344
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant01:25

Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant

In patients with renal disease, dosage adjustments are necessary to maintain therapeutic plasma drug concentrations and prevent toxicity or subtherapeutic exposure. Renal impairment alters drug pharmacokinetics, especially in conditions like uremia, where changes such as prolonged elimination half-life and altered apparent volume of distribution can significantly affect drug disposition. These changes require careful modification of the dosing regimen to achieve the desired clinical...
306
Dosage Regimens: Partial Pharmacokinetic Parameters01:01

Dosage Regimens: Partial Pharmacokinetic Parameters

It is not uncommon for complete drug pharmacokinetic profiles to remain elusive in pharmacokinetics. This necessitates certain educated assumptions by pharmacokineticists to determine appropriate dosage regimens without comprehensive pharmacokinetic data from animal or human studies. One prevalent assumption is setting the bioavailability factor, denoted as F, to 1 or 100%. This assumption caters to the scenario where a drug doesn't achieve full systemic absorption, resulting in the patient...
255
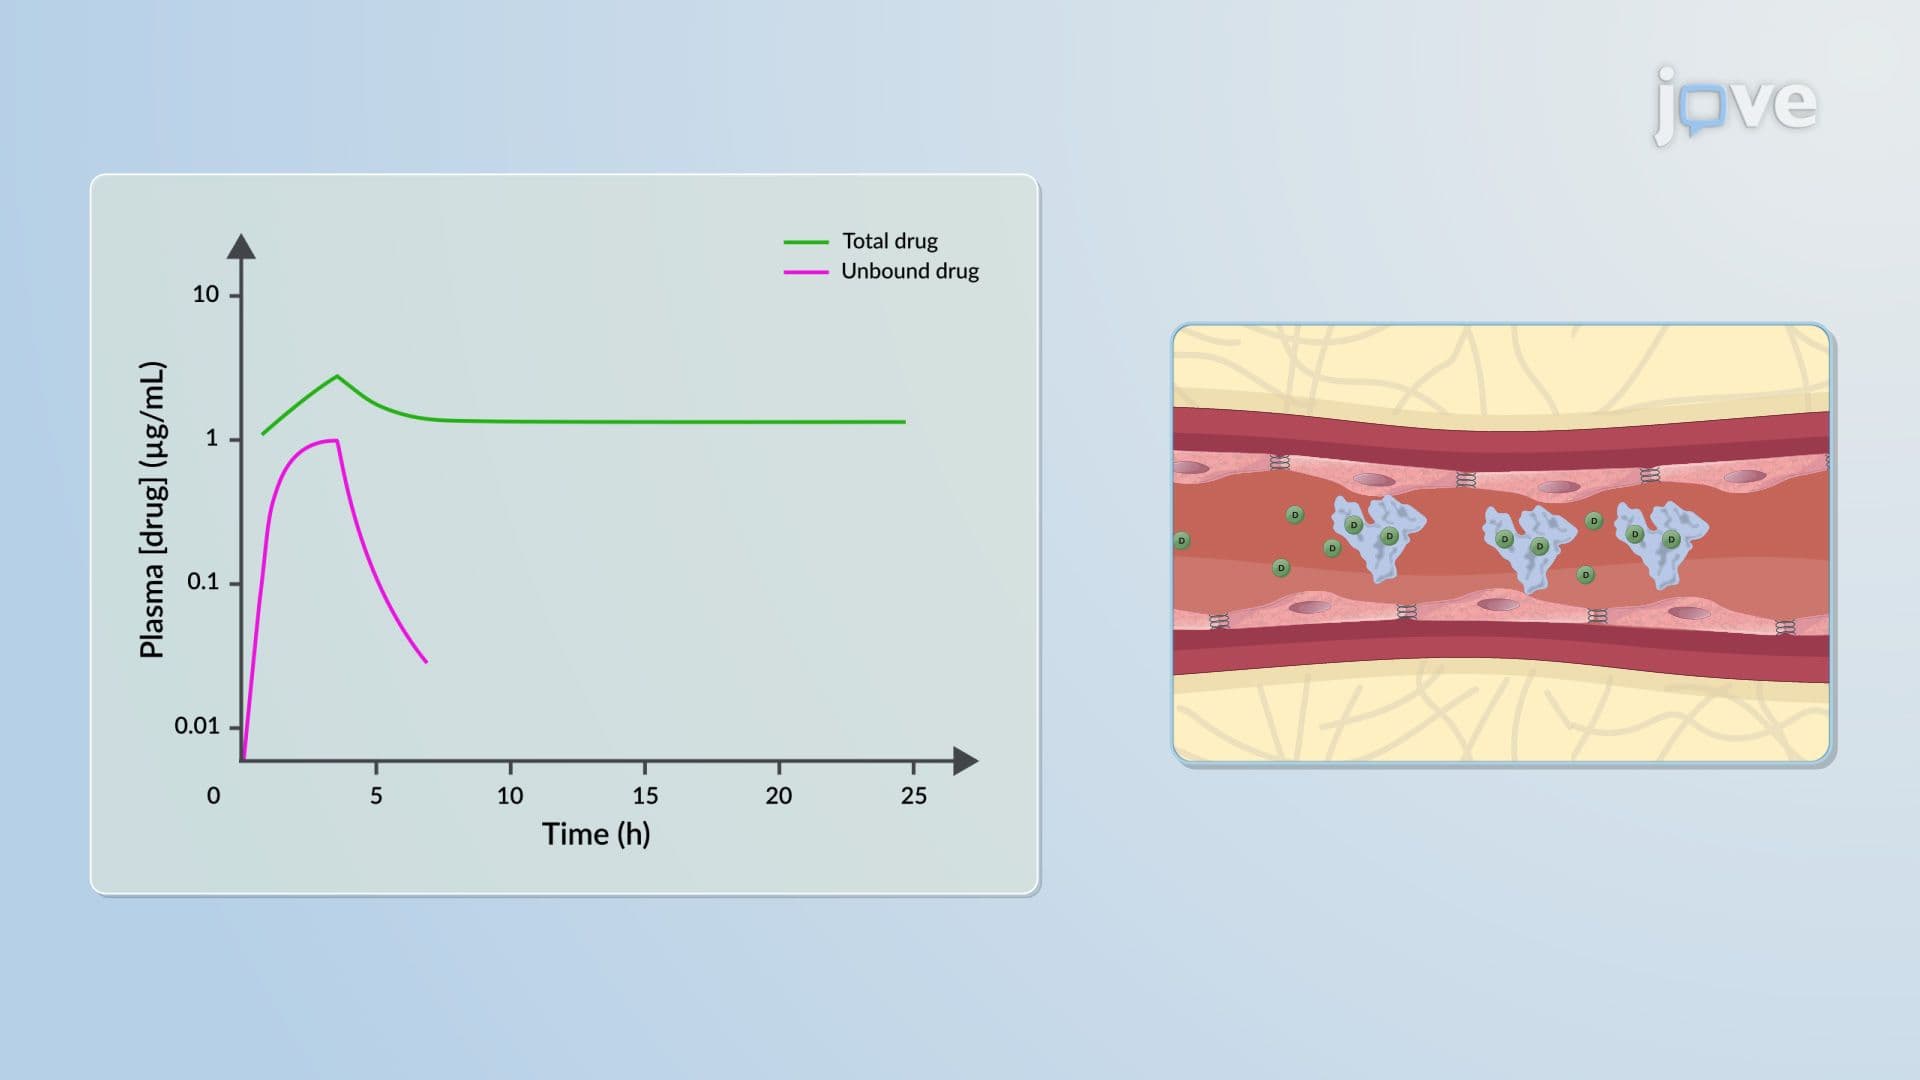
Renal Failure: Dose Adjustments01:11

Renal Failure: Dose Adjustments

In patients with renal impairment, drugs undergo significant changes in their pharmacokinetics, which require dosage adjustments to ensure safe and effective therapy.
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
575
Pharmacokinetic–Pharmacodynamic Relationship: Problems01:24

Pharmacokinetic–Pharmacodynamic Relationship: Problems

The empirical approach to drug therapy optimization relies on correlating pharmacological response with administered dosage. Such an approach can be costly, time-consuming, and often yields poor correlation due to variables like formulation factors and drug elimination characteristics. A more precise approach correlates response with plasma drug concentration or the amount of drug in the body, rather than dosage. This is achieved through pharmacokinetic-pharmacodynamic (PK/PD) modeling, which...
77
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase01:27

Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase

Phase II biotransformation reactions are essential for detoxifying and eliminating xenobiotics, including many pharmaceutical compounds. These reactions typically involve conjugation, the covalent attachment of polar endogenous groups such as glucuronic acid, sulfate, methyl, or acetyl moieties to functional groups introduced during Phase I metabolism. The resulting conjugates are more water-soluble, enabling efficient renal or biliary excretion.The major classes of Phase II enzymes include...
61