Related Experiment Video
Updated: Mar 28, 2026


Investigation into Deep Breathing through Measurement of Ventilatory Parameters and Observation of Breathing Patterns
Published on: September 16, 2019
Diaphragmatic breathing for rumination syndrome: efficacy and mechanisms of action
M Halland1, G Parthasarathy1, A E Bharucha1
1Division of Gastroenterology and Hepatology, Mayo Clinic Rochester, Rochester, MN, USA.

Background:
While high resolution esophageal manometry combined with impedancometry has demonstrated that gastric pressurizations lead to rumination, the contribution of upper esophageal sphincter (UES) and esophagogastric junction (EGJ) function to rumination is unclear. Behavioral therapy with diaphragmatic breathing (DB) can reduce rumination. We aimed to evaluate the pressures in the stomach, EGJ and UES during rumination and the effects of DB augmented with biofeedback therapy.
Methods:
Sixteen patients with rumination were studied with manometry and impedancometry before and after a meal. The postprandial assessment comprised three periods: before, during, and after DB augmented with biofeedback therapy.
Key Results:
All patients had postprandial rumination, which was associated (p < 0.001) with increased gastric pressure and reversal of the postprandial gastroesophageal pressure gradient from -4 (-43 to 18) before to 20 (7-79) mmHg during rumination. The EGJ pressure was lower (p < 0.001) during gastric pressurizations that were associated with rumination vs those that were not. The UES also relaxed, almost completely, during rumination. Patients had a median (range) of 5 (2-10) rumination episodes before, 1 (0-2) (p < 0.001) during, and 3 (1-5) after (p < 0.001 vs during) diaphragmatic breathing. During manometry and impedancometry, DB was well-tolerated and learned within 5 min. Diaphragmatic breathing increased EGJ pressure (p < 0.001) and restored a negative gastroesophageal pressure gradient (-20 mmHg [-80 to 7]).
Conclusions & Inferences:
Diaphragmatic breathing aided with high resolution esophageal manometry is well-tolerated, effective and averts the gastroesophageal pressure disturbance that leads to rumination.

Related Concept Videos
 01:17
Pulmonary Cycle: Exhalation
 01:29
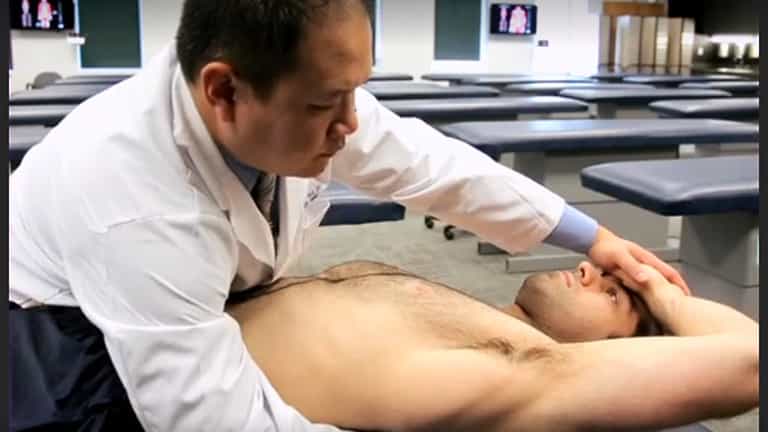
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:22
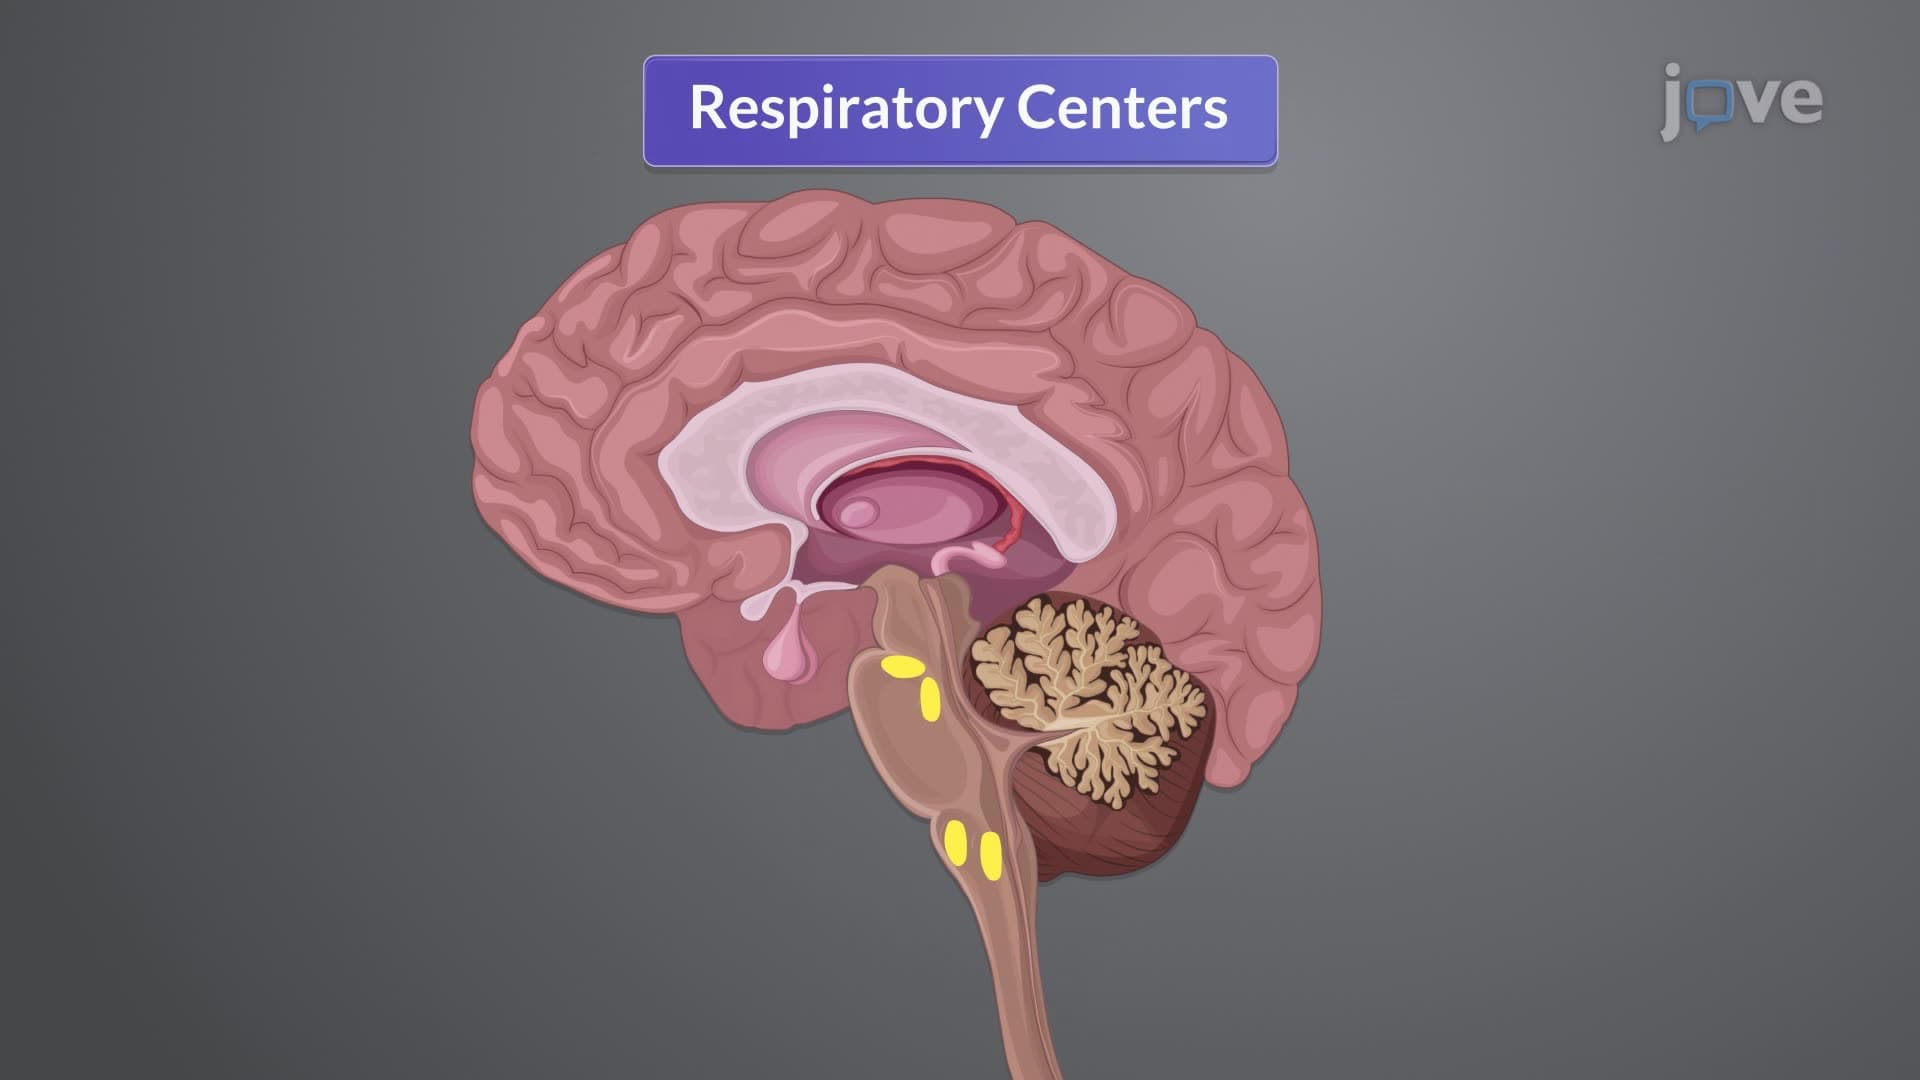
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers:
 01:21
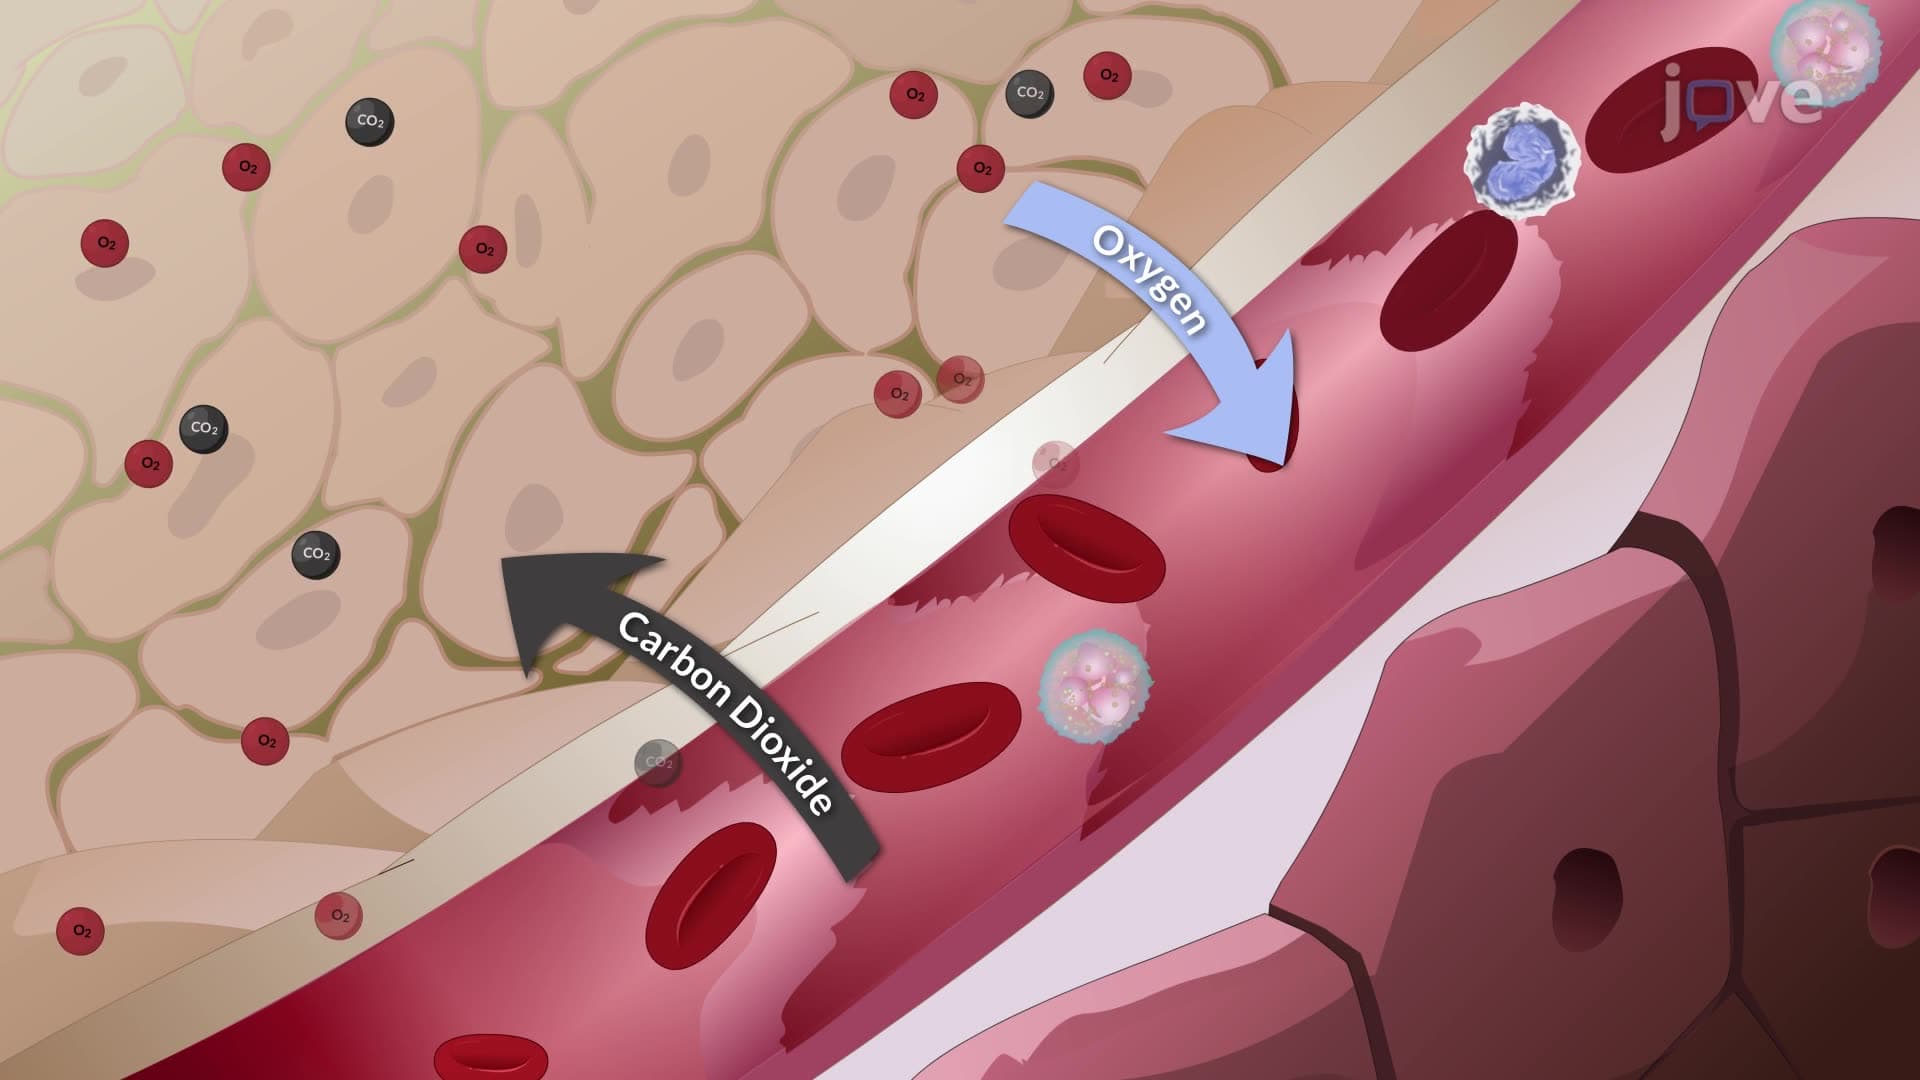
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:23
Mechanism of Breathing II: Expiration
Expiration, or exhaling, is a complex physiological process that begins as the inspiratory muscles begin to relax. This relaxation triggers a series of events that epitomize the efficiency of the respiratory system.
Mechanism of Expiration: