Related Experiment Video
Updated: Mar 28, 2026


Generation of Prostate Cancer Cell Models of Resistance to the Anti-mitotic Agent Docetaxel
Published on: September 8, 2017
Dose modifications in Asian cancer patients with hepatic dysfunction receiving weekly docetaxel: A prospective
Nicholas Li-Xun Syn1,2, Lingzhi Wang1,2,3, Andrea Li-Ann Wong1
1Department of Haematology-Oncology, National University Cancer Institute, Singapore, Singapore.

Abstract:
Hepatic dysfunction may modify the safety profile and pharmacokinetics of docetaxel in cancer patients, but no validated guideline exists to guide dose modification necessitated by this uncommon comorbidity. We carried out the first prospective study of a personalized dosage regimen for cancer patients with liver dysfunction treated with docetaxel. Weekly dosages were stratified by hepatic dysfunction classification as such: Category 1, normal; Category 2, mild--alkaline phosphatase, aspartate aminotransferase, and/or alanine aminotransferase ≤5× upper limit of normal (ULN), and total bilirubin within normal range; and Category 3, moderate--any alkaline phosphatase, and aspartate aminotransferase or alanine aminotransferase ≤5-10× ULN, and/or total bilirubin ≤1-1.5× ULN. Category 1, 2 and 3 patients received starting dosages of 40, 30, and 20 mg/m(2) docetaxel, respectively. Pharmacokinetics were evaluated on day 1 and 8 of the first treatment cycle, and entered into a multilevel model to delineate interindividual and interoccasion variability. Adverse event evaluation was carried out weekly for two treatment cycles. We found that docetaxel clearance was significantly different between patient categories (P < 0.001). Median clearance was 22.8, 16.4, and 11.3 L/h/m(2) in Categories 1, 2, and 3, respectively, representing 28% and 50% reduced clearance in mild and moderate liver dysfunction patients, respectively. However, docetaxel exposure (area under the concentration-time curve) and docetaxel-induced neutropenia (nadir and the maximum percentage decrease in neutrophil count) were not significantly different between categories. Median area under the concentration-time curve was 1.74, 1.83, and 1.77 mg·h/L in Categories 1, 2, and 3, respectively. The most common Grade 3/4 toxicity was neutropenia (30.0%). An unplanned comparison with the Child-Pugh and National Cancer Institute Organ Dysfunction Working Group grouping systems suggests that the proposed classification system appears to more effectively discriminate patients by docetaxel clearance and dose requirements. (ClinicalTrials.gov registration no. NCT00703378).
More Related Videos

Related Concept Videos
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:15
Drug Dosing: Geriatric Patients
 01:01
Dosage Regimen: Fixed Dose
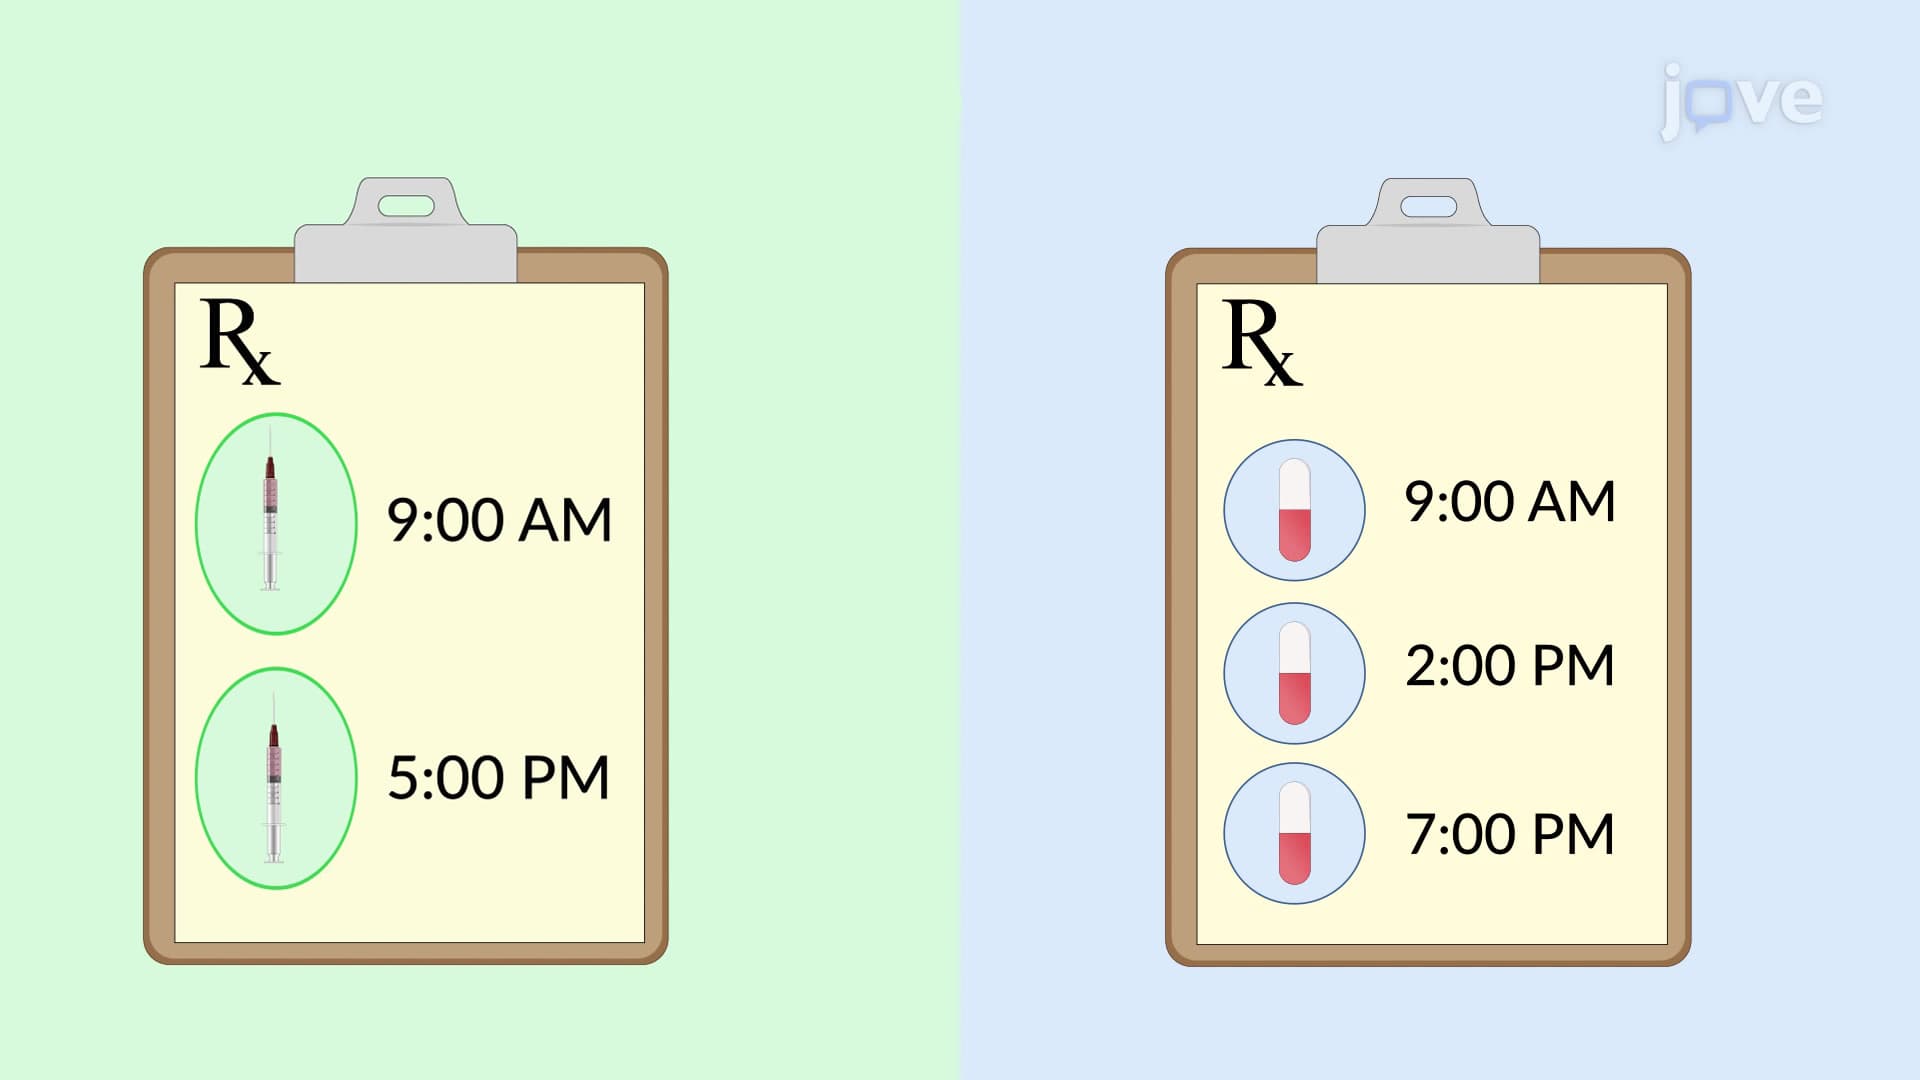
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...