Related Experiment Video
Updated: Mar 28, 2026
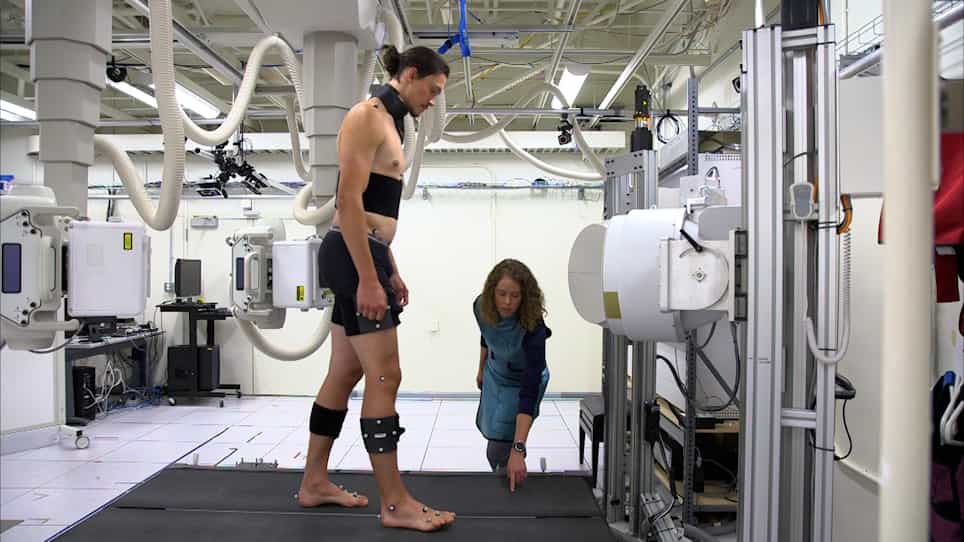
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Femoroacetabular impingement and osteoarthritis of the hip
Charlie Zhang1, Linda Li1, Bruce B Forster1
1Dr Zhang is a family medicine resident at the University of Calgary in Alberta and an alumnus of the Faculty of Medicine at the University of British Columbia in Vancouver. Dr Li is Assistant Professor in the Department of Physical Therapy at the University of British Columbia and Senior Research Scientist at the Arthritis Research Centre of Canada in Vancouver. Dr Forster is Professor and Head of the Division of Radiology at the University of British Columbia and Regional Medical Director of Medical Imaging at Vancouver General Hospital. Dr Kopec is Professor in the School of Population and Public Health at the University of British Columbia and Senior Research Scientist at the Arthritis Research Centre of Canada. Dr Ratzlaff is a postdoctoral fellow at the Arthritis Research Centre of Canada and a research fellow at Brigham and Women's Hospital at Harvard Medical School in Boston, Mass. Dr Halai is a family medicine resident at the University of British Columbia and Research Team Coordinator at the Arthritis Research Centre of Canada. Dr Cibere is Associate Professor in the Division of Rheumatology at the University of British Columbia and Senior Research Scientist in the Arthritis Research Centre of Canada. Dr Esdaile is Professor in the Division of Rheumatology at the University of British Columbia and Scientific Director of the Arthritis Research Centre of Canada.

Objective:
To outline the clinical presentation, physical examination findings, diagnostic criteria, and management options of femoroacetabular impingement (FAI).
Sources Of Information:
PubMed was searched for relevant articles regarding the pathogenesis, diagnosis, treatment, and prognosis of FAI.
Main Message:
In recent years, FAI has been increasingly recognized as a potential precursor and an important contributor to hip pain in the adult population and idiopathic hip osteoarthritis later in life. Femoroacetabular impingement is a collection of bony morphologic abnormalities of the hip joint that result in abnormal contact during motion. Cam-type FAI relates to a non-spherical osseous prominence of the proximal femoral neck or head-neck junction. Pincer-type FAI relates to excessive acetabular coverage over the femoral head, which can occur owing to several morphologic variants. Patients with FAI present with chronic, deep, or aching anterior groin pain most commonly in the sitting position, or during or after activity. Patients might also experience occasional sharp pains during activity. A thorough history should be taken that includes incidence of trauma and exercise frequency. A physical examination should be performed that includes a full hip, low back, and abdominal examination to assess for alternate causes of anterior groin pain. Diagnosis of FAI should be confirmed with radiography. Femoroacetabular impingement can be managed conservatively with rest, modification of activities, medications, and physiotherapy, or it can be treated surgically.
Conclusion:
Femoroacetabular impingement is an important cause of anterior groin pain. Early recognition and intervention by the primary care provider might be critical to alleviating morbidity and preventing FAI progression.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 08:42
A Reproducible Cartilage Impact Model to Generate Post-Traumatic Osteoarthritis in the Rabbit
Published on: November 21, 2023
Related Concept Videos
 01:16
Bones of the Lower Limb: Femur and Patella
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:20
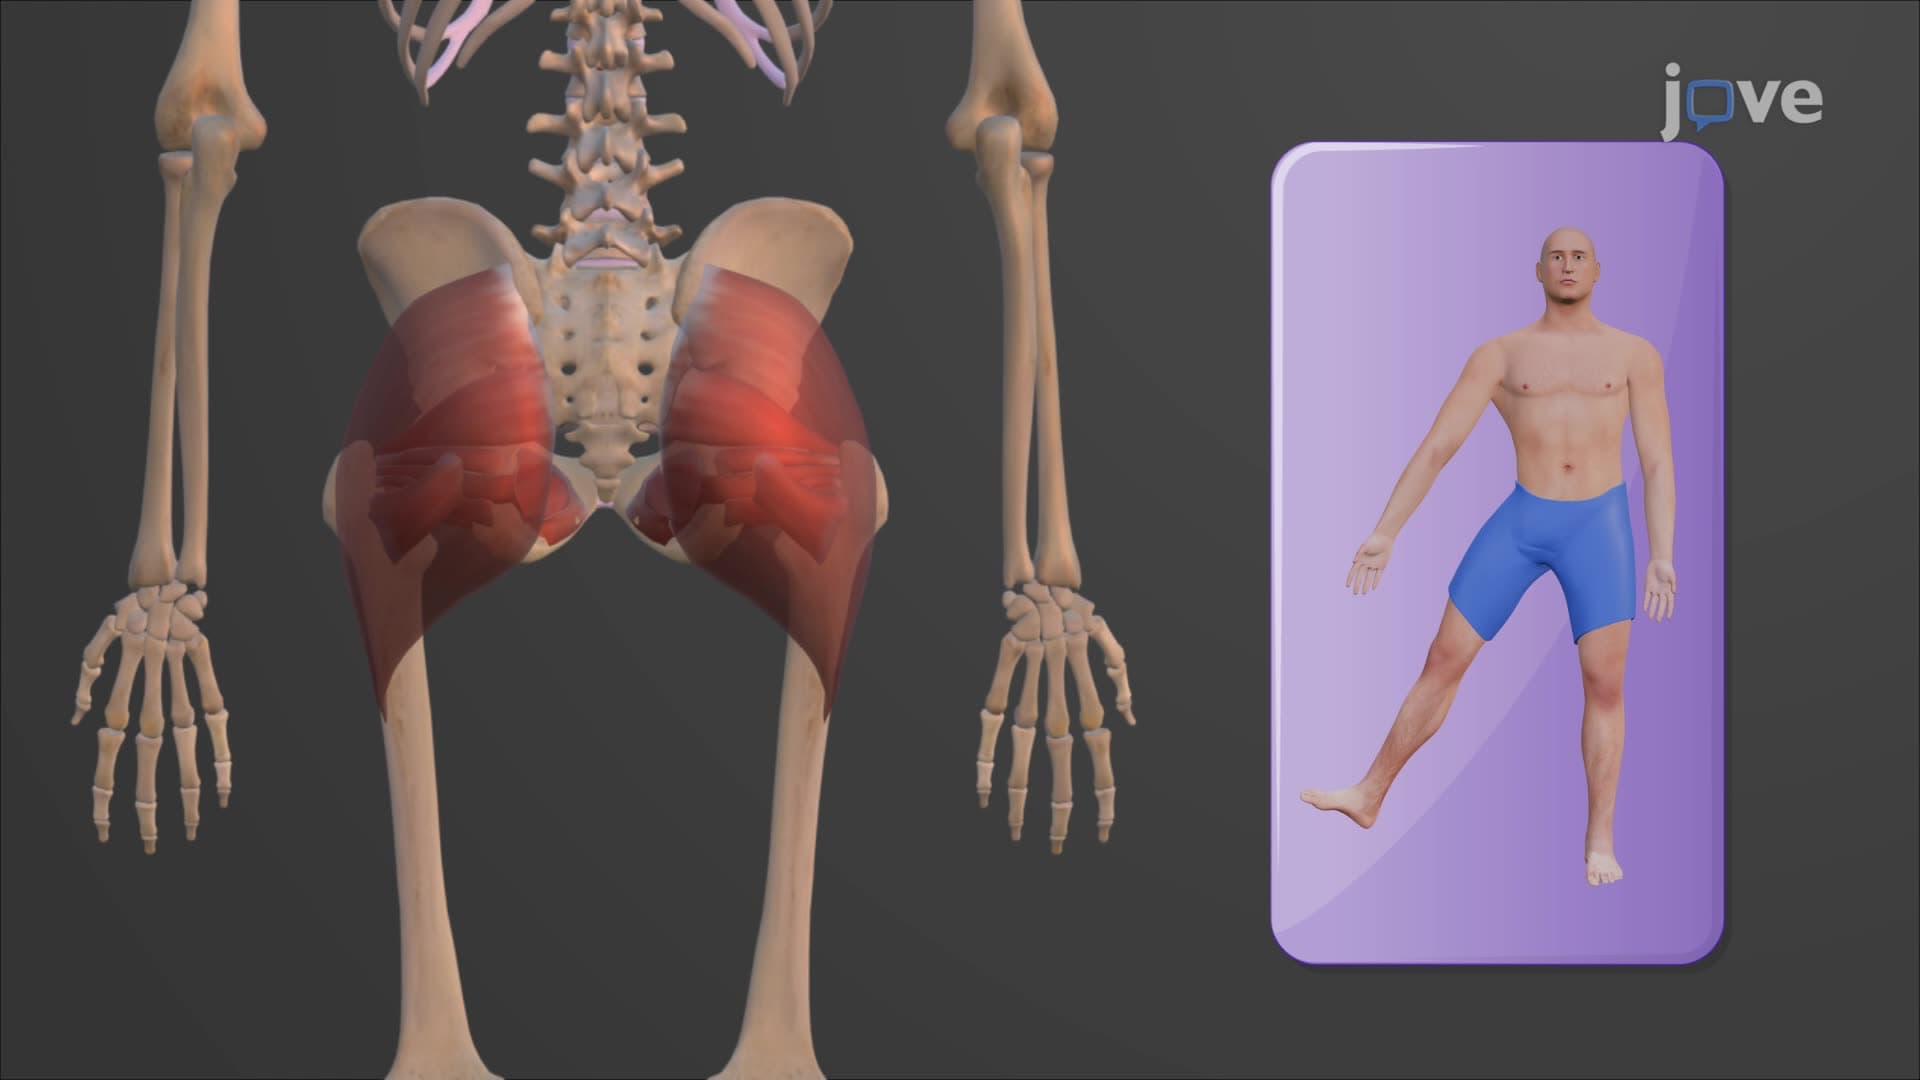
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar...