Related Experiment Video
Updated: Mar 28, 2026
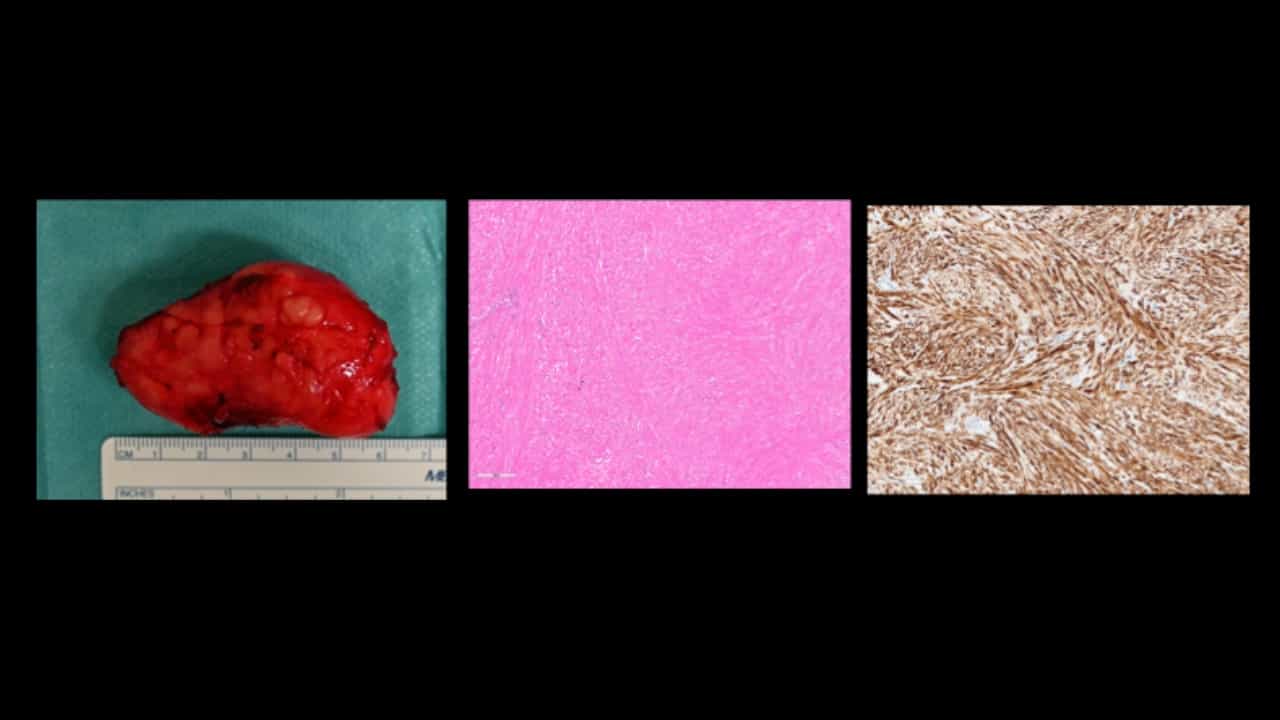

Robotic Enucleation of Esophageal Leiomyoma
Published on: February 20, 2026
Case 225: Leiomyoma
Jason DiPoce1, Xiaolin Liu-Jarin1, Jeffrey Newhouse1
1From the Departments of Radiology (J.D., J.N.) and Pathology (X.L.J.), Columbia University Medical Center, 180 Fort Washington Ave, 3rd Floor, Harkness Pavillion, Room 313, New York, NY 10032.

Abstract:
A 33-year-old pregnant woman (gravida 11, para 8) presented with increasing severe abdominal pain during the first trimester of pregnancy and increasing abdominal distention out of proportion to her prior pregnancies. Ultrasonography (US) without Doppler performed at another hospital had revealed a pelvic mass; therefore, this patient had been referred to our institution for further evaluation. Unenhanced magnetic resonance (MR) imaging was then performed at 8 weeks of gestation. The main portion of the gravid uterus and the ovaries was not seen on these images, but the parts that were seen appeared normal. Diagnostic laparoscopic biopsy was performed during the first trimester, but complete removal of the mass was deferred because of fears the pregnancy would be lost. The patient was closely observed throughout the pregnancy with serial US until the 37th week of gestation, at which time the patient underwent Caesarian section. At the time of Caesarian section, the mass was noted to extend from the spleen downward deep into the pelvis. A biopsy was performed at the time of Caesarian section. Definitive removal of the mass was deferred at the time of Caesarian section to minimize postpartum blood loss and to further delineate the mass with imaging for future surgery. Intravenous contrast material-enhanced (120 mL of Omnipaque 350; Nycomed Amersham, Princeton, NJ) computed tomography (CT) was performed 3 days after Caesarian section. The cystic component measured approximately 15 HU. Repeat MR imaging 1.5 months after Caesarian section was then performed. No loss of signal intensity in the mass was seen on fat-saturated images. There was no evidence of local or distant metastatic disease. The mass abutted and displaced the uterus and the ovaries but did not distort either of these organs. Vascular anatomy was not useful in determining the origin of the mass. The comprehensive metabolic panel and complete blood count were normal throughout and after the pregnancy.
More Related Videos
 05:46
Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
 08:07
Establishment of an Experimental Mouse Model of Endometrioma to Study its Related Infertility
Published on: April 5, 2024
Related Concept Videos
 01:16
Uterine Tubes
 01:18
Uterus and Cervix
The uterus is securely anchored within the pelvic cavity by paired broad ligaments on either side. It is further stabilized by three pairs...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:19
Histology of the Uterus
The endometrium is the...
 01:26
Ovaries
On the ovarian surface, a layer of...
 01:24
Disorders of the Female Reproductive System