Related Experiment Video
Updated: Jul 25, 2026


Assessment of Child Anthropometry in a Large Epidemiologic Study
Published on: February 2, 2017
[Estimation of the optimal tube length : Systematic review article on published formulae for infants and children]
M Boensch1, V Schick2, O Spelten2
1Klinik für Anästhesiologie und Operative Intensivmedizin, Universitätsklinikum Köln (AöR), Kerpener Str. 62, 50937, Köln, Deutschland. Marc.Boensch@uk-koeln.de.

Insights
Accurate endotracheal tube placement in children is critical. Published formulas for estimating tube depth have limitations, with a maximum 81% concordance, necessitating clinical verification.
Area of Science:
- Pediatric Anesthesiology
- Critical Care Medicine
- Respiratory Management
Background:
- Correct endotracheal tube (ETT) placement in children is vital to prevent complications like volutrauma and hypoxia.
- Existing formulas for nasotracheal and orotracheal tube placement often rely on body weight and age.
Purpose of the Study:
- To identify and compare published formulas for estimating correct ETT placement in pediatric patients.
- To analyze the advantages and disadvantages of various ETT depth estimation formulas.
Main Methods:
- A comprehensive literature search of Medline and PubMed was conducted using specific keywords related to pediatric anesthesia and ETT placement.
- 13 distinct formulas for ETT insertion depth were identified and analyzed for both orotracheal and nasotracheal intubation.
- Formulas were categorized for newborns/infants and older children (1-16 years), with independent assessment by anesthesiology and pediatric specialists.
Main Results:
- 16 relevant publications yielded 13 different formulas for ETT depth estimation.
- For children aged 1-16 years, 7 formulas were found (6 age-based, 1 weight-based).
- For newborns and infants, 6 formulas were identified (4 weight-based, 1 length-based, 1 gestational age-based).
Conclusions:
- Published formulas for pediatric ETT depth are simple but have significant limitations.
- Age-based formulas showed a maximum 81% concordance with chest X-rays for both intubation types and age groups.
- A gestational age-based formula showed some utility for newborns/infants, but no single formula is universally recommended without clinical confirmation (auscultation or X-ray).
Background:
The correct placement of an endotracheal tube in children is essential as incorrect placement following unilateral ventilation and tube displacement may lead to far-reaching consequences, such as volutrauma and hypoxia, respectively. Different formulae referring to the correct placement of nasotracheal and orotracheal tubes have been published with reference to body weight and age.
Objective:
The aim of the present review article was to identify and compare the published formulae for estimating correct endotracheal tube placement in children with their advantages and disadvantages.
Material And Methods:
A search in Medline and PubMed was performed to identify published formulae. Formulae for insertion depth in orotracheal and also nasotracheal intubation are discussed. The published formulae for newborns and infants are presented separately. The keywords "paediatric"/"pediatric", "anaesthesia"/"anesthesia", "anaesthesiology"/"anesthesiology", "endotracheal tube", "placement", "position", "length", "depth" and "insertion" were used to identify the formulae.
Results:
A total of 806 publications were found, 16 publications were identified as being relevant and 13 different formulae were identified. In the age group from 1 to 16 years old a total of 7 formulae (6 age-based formulae and one based on weight) and for newborns and infants a total of 6 formulae (4 formulae based on body weight, 1 formula based on body length and 1 formula based on gestational age) were found. All publications were subsequently assessed and classified independently by a specialist physician in anesthesiology and a specialist physician in pediatrics.
Conclusion:
The published formulae were comparatively simply to apply but had notable limitations. Correlating the position of the endotracheal tubes with chest x-rays, the concordance analysis showed that for the age-based formulae using orotracheal as well as nasotracheal intubation and in both age groups, an accordance could only be achieved in a maximum of 81%. In the presence of a lack of alternative possibilities, only one formula based on the gestational age seemed to have an impact on estimation of correct endotracheal tube depth placement in newborns and infants. Therefore, a generally valid formula cannot be recommended without verification by auscultation or chest x-ray.


Related Concept Videos
 01:23
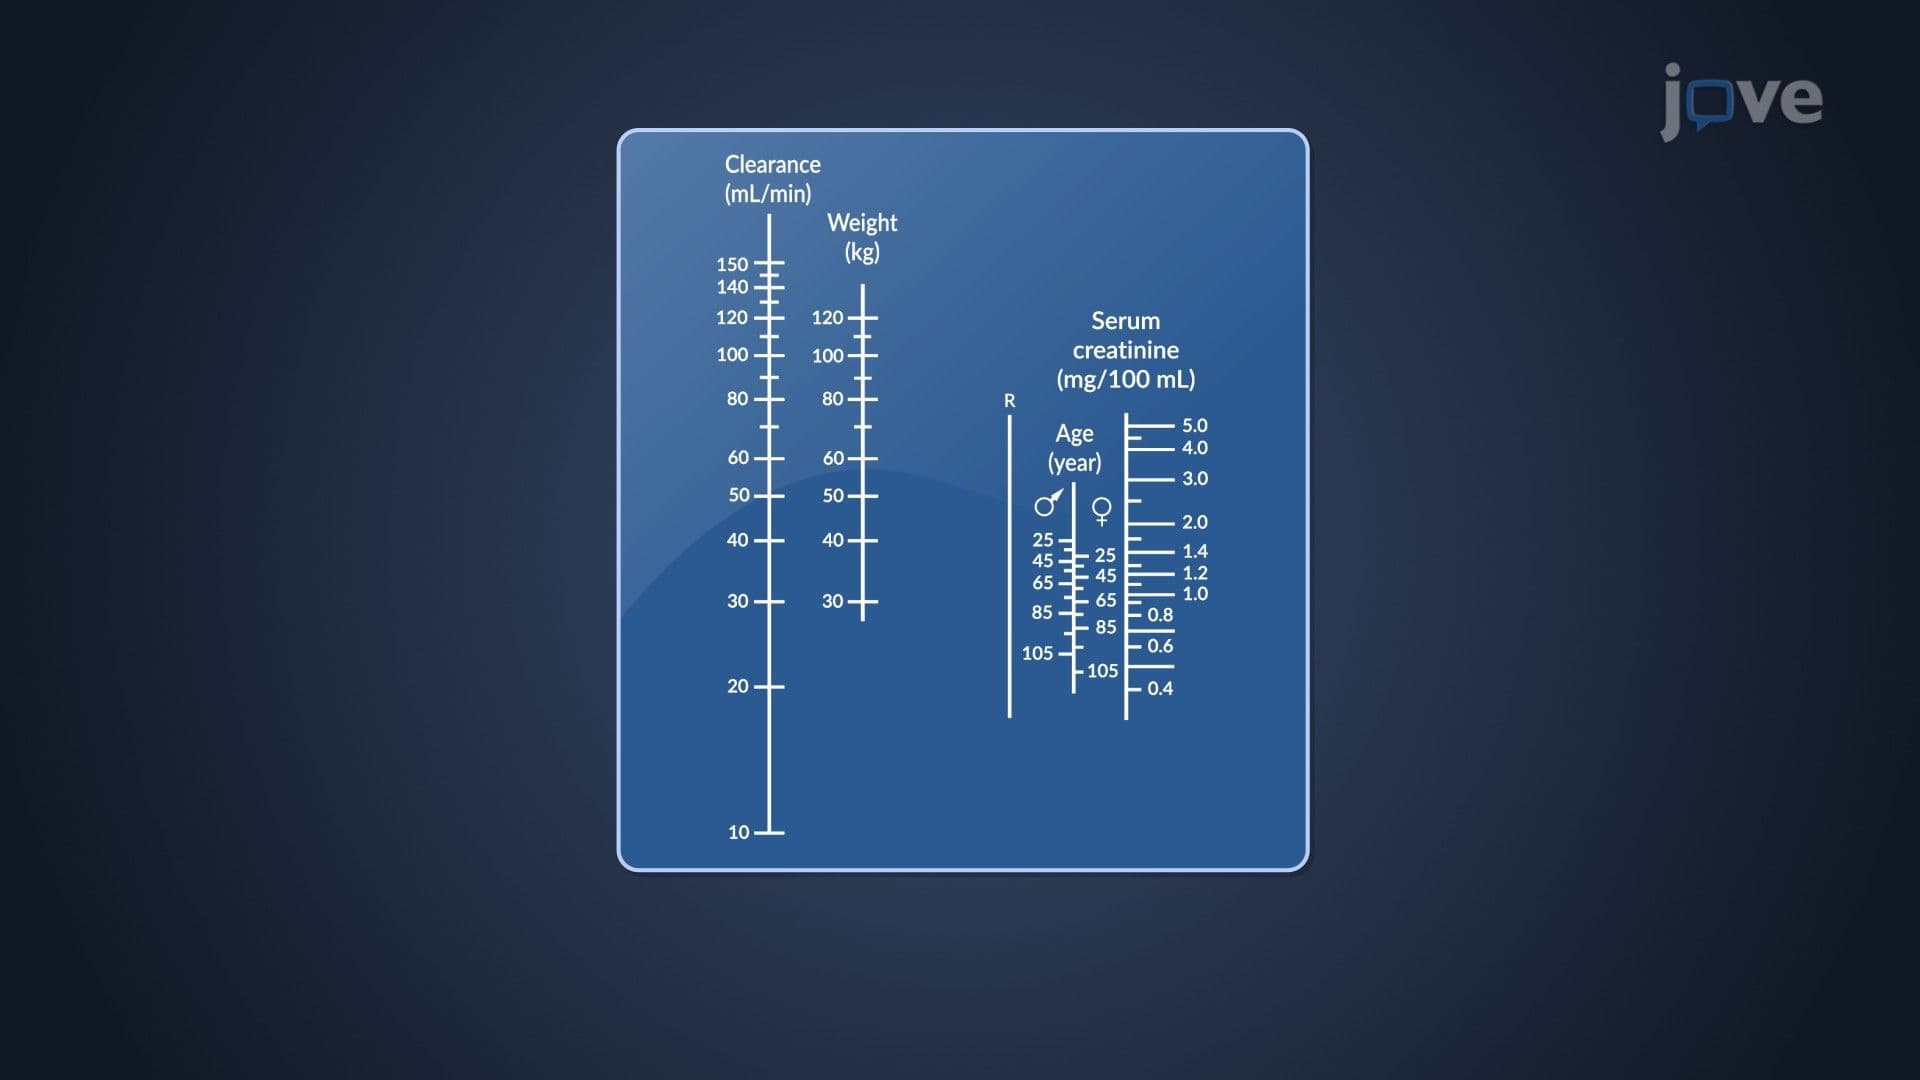
Dosage Regimen Designs: Nomograms and Tabulations
 01:29
Drug Dosing: Infants and Children
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration