Related Experiment Video
Updated: Mar 27, 2026
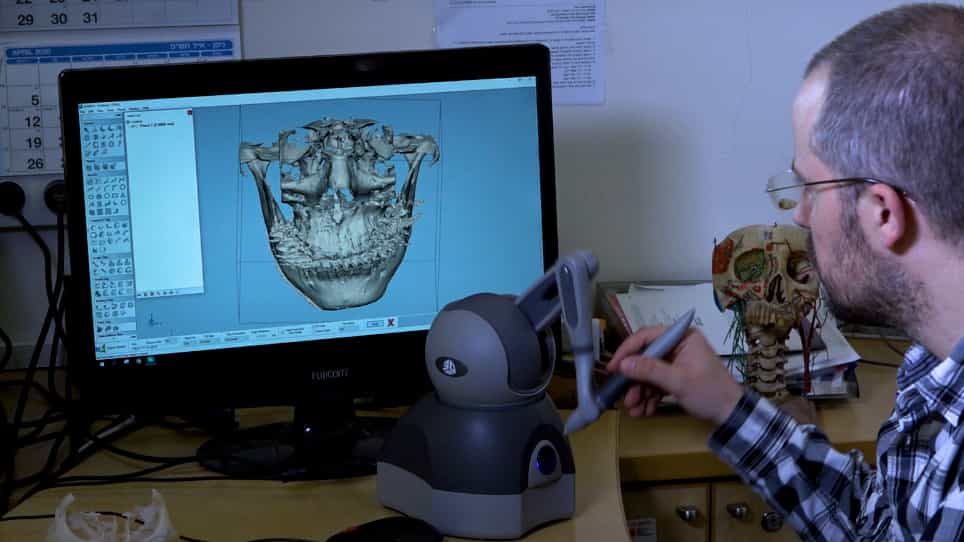

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Treated Versus Untreated Positional Head Deformity
Jan-Falco Wilbrand1, Nikolai Lautenbacher, Jörn Pons-Kühnemann
1*Department of Cranio-Maxillofacial Surgery †Department of Biostatistics ‡Department of Neurosurgery, University Hospital Giessen, Giessen, Germany.

Insights
Helmet therapy significantly improved positional head deformity in children over five years, showing greater improvement than untreated cases. This study contrasts with recent findings suggesting no benefit from helmet use.
Area of Science:
- Craniofacial Surgery
- Pediatric Orthopedics
- Developmental Pediatrics
Background:
- Positional head deformity is common in infants, often considered benign and self-correcting.
- Helmet therapy is frequently recommended for moderate to severe cases of deformational plagiocephaly and brachycephaly.
- Recent studies have questioned the efficacy of helmet therapy for positional head deformities.
Purpose of the Study:
- To evaluate the long-term clinical course of positional cranial deformation.
- To compare anthropometric parameters between children treated with orthotic helmets and untreated children.
- To assess the effectiveness of individual molding helmets in correcting nonsynostotic head deformities.
Main Methods:
- A 5-year observational study comparing treated and untreated children with positional cranial deformation.
- Anthropometric measurements including cranial vault asymmetry (CVA), cranial vault asymmetry index (CVAI), and oblique cranial length ratio (OCLR) were recorded.
- Patients were matched at baseline, with initial differences in CVA and CVAI noted between groups.
Main Results:
- Children treated with molding helmets showed significant improvement in CVA (ΔCVA 1.35 cm) and CVAI over 5 years.
- Untreated children exhibited minimal improvement in CVA (ΔCVA 0.01 cm) and CVAI during the same period.
- Despite baseline differences, helmet therapy demonstrated a clear positive impact on cranial symmetry.
Conclusions:
- Individual molding helmet therapy leads to significant improvement in nonsynostotic head deformities.
- Untreated positional cranial deformities show limited improvement in absolute measurements over a 5-year period.
- Findings suggest that helmet therapy is an effective treatment for positional head deformity, contrary to some recent research.
Background:
Positional head deformity in early childhood is asserted to be a benign and in some cases spontaneously correcting entity encountered in craniofacial surgery. Although many authors have stated that helmet therapy is indicated in moderate and severe cases of deformational plagiocephaly and brachycephaly; others have reported resolution of these conditions within the first 2 to 3 years of life. A recent randomized controlled trial found that helmet therapy does not have beneficial effects for patients with positional head deformity.
Methods:
The authors evaluated the clinical course of positional cranial deformation during a period of 5 years and compared the anthropometric parameters of orthotically treated versus untreated children within this timeframe.
Results:
Although the patients were matched with respect to their cranial deformation at baseline, there were significant differences in the cranial vault asymmetry (CVA), cranial vault asymmetry index (CVAI), and oblique cranial length ratio (OCLR) between Groups 1 and 2 at the initial point (P < 0.05). The mean CVA was 0.95 cm in Group 1 (no helmet) and 1.74 cm in Group 2 (helmet). The mean CVAI at baseline was 7.25 for Group 1 and 13.77 for Group 2. Approximately 5 years after the first examination, the authors found clear improvement in the mean CVA in Group 2 (ΔCVA 1.35 cm) compared with Group 1 (ΔCVA 0.01 cm) and the mean CVAI.
Conclusions:
In contrast to recently published studies, the authors found clear improvement in nonsynostotic head deformity treated with an individual molding helmet and no clear evidence of improvement of absolute measurements in untreated cranial deformity within a 5-year follow-up period.
More Related Videos
 08:03
Midface Hypoplasia and Cranial Base Morphology in Syndromic Craniosynostosis: A Comparative Analysis Study Using a Predictive Regression Model
Published on: November 4, 2025
 07:11
Assessment of the Efficacy of An Osteopathic Treatment in Infants with Biomechanical Impairments to Suckling
Published on: February 5, 2019
Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:08
Overview of the Skull
The cranial vault surrounds and protects the brain and houses the middle and inner ear structures. This cavity is bounded superiorly by the rounded top of the skull, which...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...