Free phenytoin assessment in patients: measured versus calculated blood serum levels
Related Experiment Video
Updated: Mar 27, 2026

Seizure Activity Induced by Electroshock in Drosophila Larvae
Published on: June 6, 2025
Andrea Tobler1, Raphael Hösli1, Stefan Mühlebach2
1Division of Clinical Pharmacy and Epidemiology and Hospital Pharmacy, University of Basel, Spitalstrasse 26, 4031, Basel, Switzerland.

Background:
Total serum drug levels are routinely determined for the therapeutic drug monitoring of selected, difficult-to-dose drugs. For some of these drugs, however, knowledge of the free fraction is necessary to adapt correct dosing. Phenytoin, with its non-linear pharmacokinetics, >90 % albumin binding and slow elimination rate, is such a drug requiring individualization in patients, especially if rapid intravenous loading and subsequent dose adaptation is needed. In a prior long-term investigation, we showed the excellent performance of pharmacy-assisted Bayesian forecasting support for optimal dosing in hospitalized patients treated with phenytoin. In a subgroup analysis, we evaluated the suitability of the Sheiner-Tozer algorithm to calculate the free phenytoin fraction in hypoalbuminemic patients.
Objective:
To test the usefulness of the Sheiner-Tozer algorithm for the correct estimation of the free phenytoin concentrations in hospitalized patients.
Setting:
A Swiss tertiary care hospital.
Method:
Free phenytoin plasma concentration was calculated from total phenytoin concentration in hypoalbuminemic patients and compared with the measured free phenytoin. The patients were separated into a low (35 ≤ albumin ≥ 25 g/L) and a very low group (albumin <25 g/L) for comparing and statistically analyzing the calculated and the measured free phenytoin concentration.
Main Outcome Measures:
Calculated and the measured free phenytoin concentration.
Results:
The calculated (1.2 mg/L (SD = 0.7) and the measured (1.1 mg/L (SD = 0.5) free phenytoin concentration correlated. The mean difference in the low and the very low albumin group was: 0.10 mg/L (SD = 1.4) (n = 11) and 0.13 mg/L (SD = 0.24) (n = 12), respectively. Although the variability of the data could be a bias, no statistically significant difference between the groups was found: t test (p = 0.78), the Passing-Bablok regression, the Spearman's rank correlation coefficient of r = 0.907 and p = 0.00. The Bland-Altman plot including the regression analysis revealed no systematic differences between the calculated and the measured value [M = 0.11 (SD = 0.28)].
Conclusion:
In absence of a free phenytoin plasma concentration measurement also in hypoalbuminemic patients, the Sheiner-Tozer algorithm represents a useful tool to assist therapeutic monitoring to calculate or control free phenytoin by using total phenytoin and the albumin concentration.

Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:28
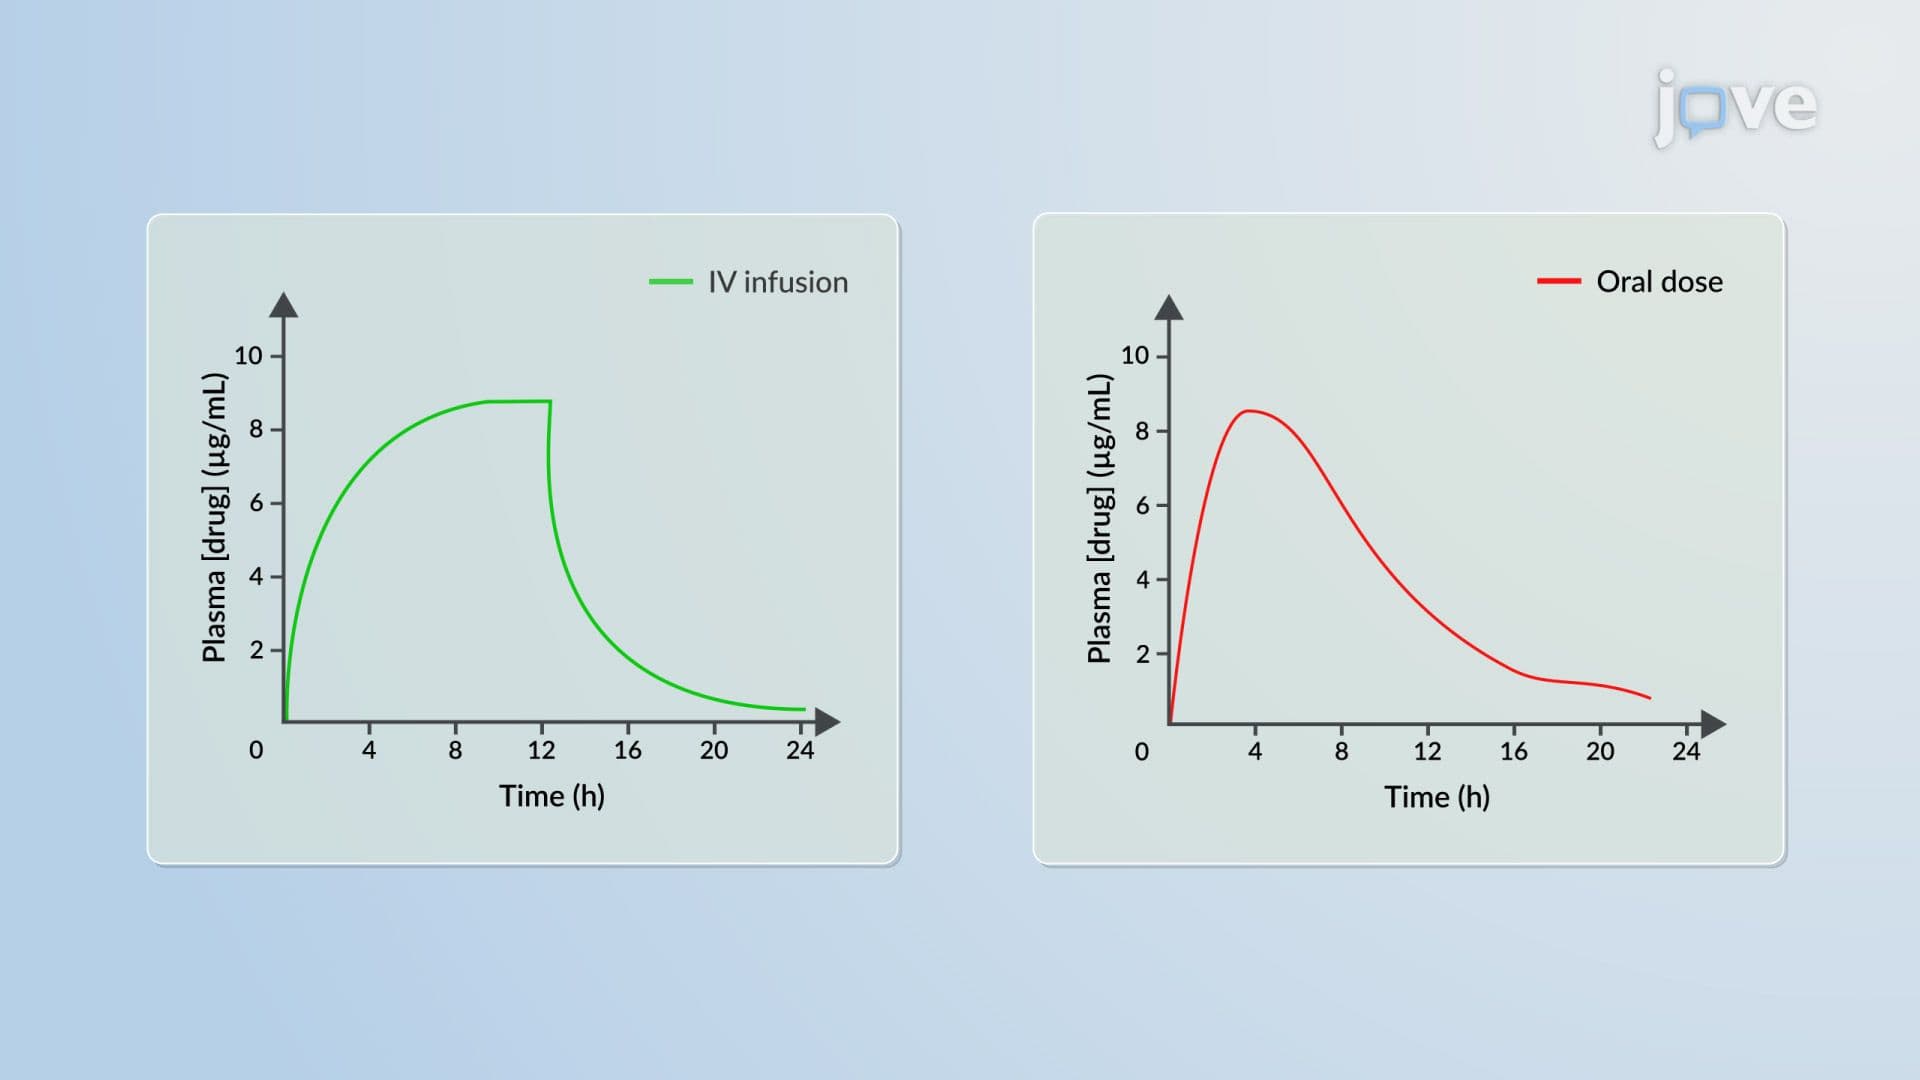
IV Infusion to Oral Dosing: Conversion Methods
 01:20
Measurement of Bioavailability: Pharmacodynamic Methods
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters