Related Experiment Video
Updated: Mar 27, 2026
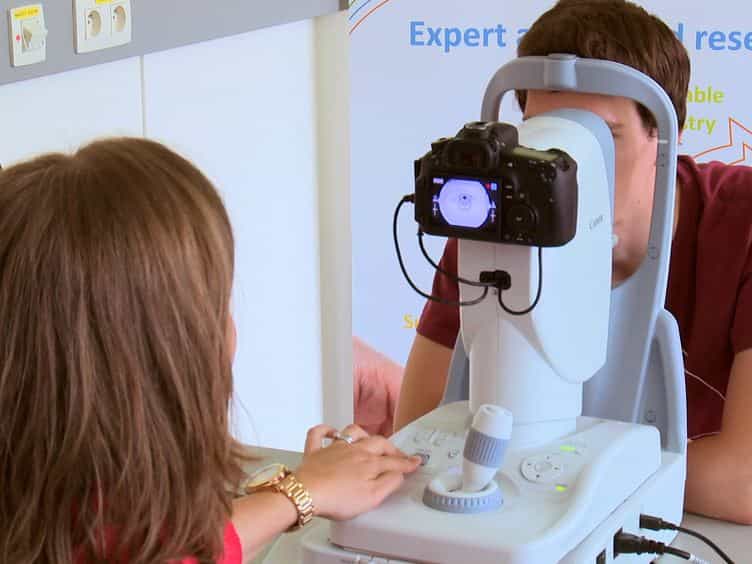

Fundus Photography as a Convenient Tool to Study Microvascular Responses to Cardiovascular Disease Risk Factors in Epidemiological Studies
Published on: October 22, 2014
Hypertensive/Microvascular Disease and COPD: a Case Control Study
Sky K H Chew1, Deb Colville, Piers Canty
1The University of Melbourne Department of Medicine (Northern Health), Epping, Australia.

Background/Aims:
This study tested the hypothesis that individuals with chronic obstructive pulmonary disease (COPD) have more small vessel disease and more severe disease than an age- and gender- matched hospital patient comparison group.
Methods:
This was a single centre, case-control study of 151 individuals with COPD (FEV1/VC) < 0.7 recruited consecutively immediately after respiratory function tests at a Melbourne teaching hospital over a 4 month period in 2010. Controls were individuals with normal respiratory function tests recruited contemporaneously from the same centre. Retinal images were obtained with a nonmydriatic camera (KOWA or Canon CR5-45NM), deidentiifed and graded by two trained graders for microvascular retinopathy (Wong and Mitchell classification), and vessel calibre using a computer-assisted method and Knudtson's modification of the Parr-Hubbard formula. Differences in microvascular retinopathy and vessel calibre between COPD patients and the comparison group were examined using Fisher's exact test or the t test (StataCorp, Texas).
Results:
Patients with COPD had more microvascular retinopathy (121, 80% and 76, 50%; OR 3.98, 95%CI 2.39 to 6.64) and more severe disease (42, 28% and 18, 12%; OR 2.85, 95% CI 1.55 to 5.23) than other hospital patients. COPD remained an independent determinant of microvascular retinopathy (OR 4.56, 95%CI 2.49 to 8.36) after adjusting for gender, hypertension, smoking, and diabetes duration. Retinal arterioles and venules were wider in patients with COPD than other hospital patients (mean difference +6.5 µm, 95% confidence interval 1.4 to 11.6; and +17.4 µm, 95%CI 9.4 to 25.5, respectively). Larger venules were more common in younger individuals (+0.6 µm, 0.1 to 1.17) with more cigarette exposure (+0.3 µm, 0.2 to 0.5) or a lower serum albumin (+23.0 µm, 6.0 to 40.0). Venular calibre was not different in current and former smokers (p=0.77). There were trends for venules to be larger with more severe COPD (lower FEV1/VC, p=0.09) and with CT-demonstrated emphysema (p=0.06).
Conclusions:
Hypertensive/microvascular disease is more common and more severe in patients with COPD. This is likely to contribute to the associated increase in cardiac risk.

Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: