Related Experiment Video
Updated: Mar 27, 2026
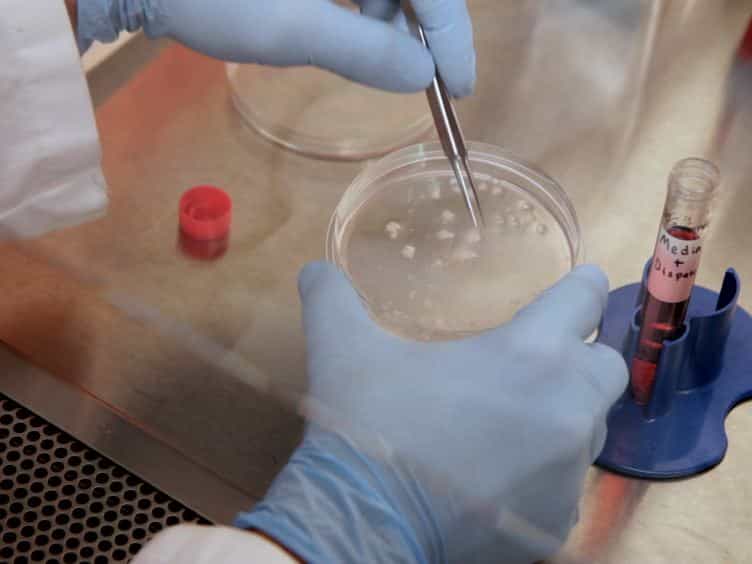
Method for Obtaining Primary Ovarian Cancer Cells From Solid Specimens
Published on: February 4, 2014
Primary Ovarian Pregnancy: 43 Years Experience in a Single Institute and still a Medical Challenge

Background:
Despite awareness regarding tubal pregnancy, ovarian pregnancy still remains a diagnostic challenge. The correct diagnosis is most frequently made intraoperatively and requires histopathologic confirmation. Therefore, additional diagnostic measurements are needed for earlier and more accurate detection of ovarian pregnancies which will allow more rapid and efficient treatment.
Objectives:
To assess the time trends, clinical manifestations, surgical management and post-procedure outcome of 46 primary ovarian pregnancies in a single institution during three time periods.
Methods:
In this retrospective study we compared 20 patients with primary ovarian pregnancy during the years 1971- 1989 (first period), 19 patients in 1990-2001 (second period) and 7 patients in 2002-2013 (third period). In all cases the pathology examination confirmed primary ovarian pregnancy.
Results:
The number of tubal ectopic pregnancies almost doubled, from 637 in the first period to 1279 in the third period (P < 0.001). However, there was a significant fall in the number of ovarian ectopic pregnancies, from 20 cases in the first period to 7 cases in the third (P = 0.009). A significant difference was noted when we compared the postoperative hospitalization time (4.06 ± 1.4 vs. 2.0 ± 0.6 days respectively, P = 0.001) in the second versus the third time period.
Conclusions:
Ovarian pregnancy continues to be a diagnostic challenge, associated with a high rate of circulatory collapse, hemoperitoneum and requirements for blood transfusions, all leading to longer hospitalization.


Related Concept Videos
 01:27
Ovarian Cycle
 01:22
Oogenesis
Each primary oocyte is surrounded by a layer of pre-granulosa cells, forming what is...
 02:07
Oogenesis
 01:20
Folliculogenesis
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:24
Disorders of the Female Reproductive System