Related Experiment Video
Updated: Mar 27, 2026
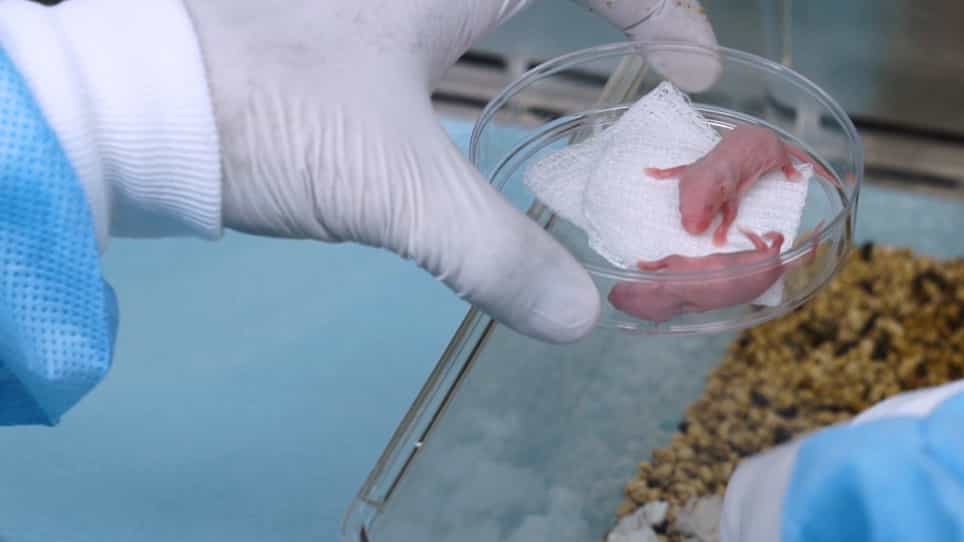

Chronic, Acute, and Reactivated HIV Infection in Humanized Immunodeficient Mouse Models
Published on: December 3, 2019
Survival in HIV-positive transplant recipients compared with transplant candidates and with HIV-negative controls
Michelle E Roland1, Burc Barin, Shirish Huprikar
1aDepartment of Medicine, University of California, San Francisco, San Francisco, CaliforniabEMMES Corporation, Rockville, MarylandcIcahn School of Medicine at Mount Sinai, New York, New YorkdBeth Israel Deaconess Medical Center, Boston, MassachusettseUniversity of Pennsylvania, Philadelphia, PennsylvaniafRush University Medical Center, Chicago, IllinoisgDavid Geffen School of Medicine, UCLA and Cedars Sinai Medical Center, Los AngeleshDepartment of Surgery, University of California, San Francisco, San Francisco, California, USA.*Douglas W. Hanto's current affiliation is Vanderbilt University, Nashville, TN, USA.†George Beatty current affiliation is California Department of Corrections and Rehabilitation, California, USA.

Objectives:
To evaluate the impact of liver and kidney transplantation on survival in HIV-positive transplant candidates and compare outcomes between HIV-positive and negative recipients.
Design:
Observational cohort of HIV-positive transplant candidates and recipients and secondary analysis comparing study recipients to HIV-negative national registry controls.
Methods:
We fit proportional hazards models to assess transplantation impact on mortality among recipients and candidates. We compared time to graft failure and death with HIV-negative controls in unmatched, demographic-matched, and risk-adjusted models.
Results:
There were 17 (11.3%) and 46 (36.8%) deaths among kidney and liver recipients during a median follow-up of 4.0 and 3.5 years, respectively. Transplantation was associated with survival benefit for HIV-infected liver recipients with model for end-stage liver disease (MELD) greater than or equal 15 [hazard ratio (HR) 0.1; 95% confidence interval (CI) 0.05, 0.01; P < 0.0001], but not for MELD less than 15 (HR 0.7; 95% CI 0.3, 1.8; P = 0.43) or for kidney recipients (HR 0.6; 95% CI 0.3, 1.4; P = 0.23). In HIV-positive kidney recipients, unmatched and risk-matched analyses indicated a marginally significant HR for graft loss [1.3 (P = 0.07) and HR 1.4 (P = 0.052)]; no significant increase in risk of death was observed. All models demonstrated a higher relative hazard of graft loss or death in HIV-positive liver recipients; the absolute difference in the proportion of deaths was 6.7% in the risk-matched analysis.
Conclusion:
Kidney transplantation should be standard of care for well managed HIV-positive patients. Liver transplant in candidates with high MELD confers survival benefit; transplant is a viable option in selected candidates. The increased mortality risk compared with HIV-negative recipients was modest.
Trial Registration:
ClinicalTrials.Gov; NCT00074386; http://clinicaltrials.gov/.


Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy...
 01:10
Retrovirus Life Cycles
 01:40
Cell-mediated Immune Responses