Related Experiment Video
Updated: Mar 27, 2026
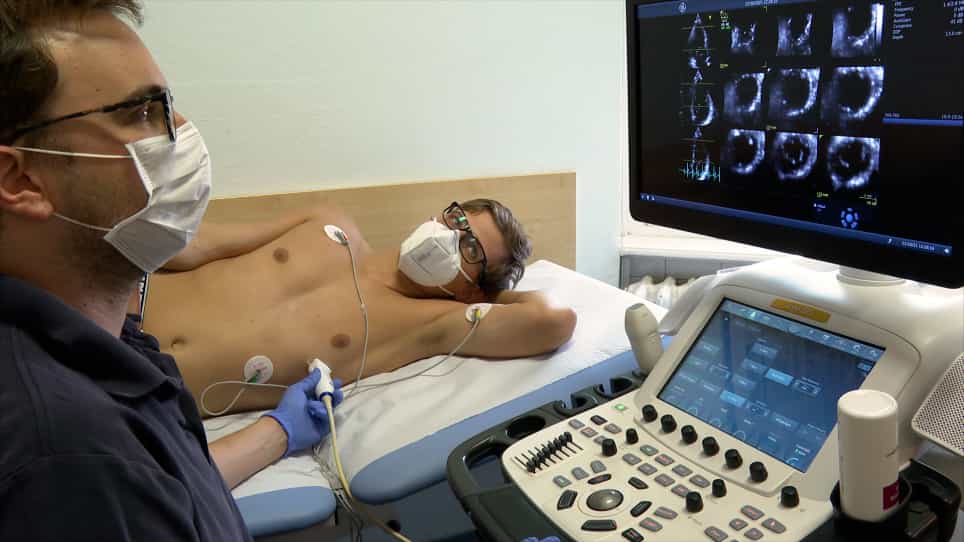

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Causes and Consequences of Longitudinal LV Dysfunction Assessed by 2D Strain Echocardiography in Cardiac Amyloidosis
Julien Ternacle1, Diane Bodez1, Aziz Guellich1
1UPEC, Créteil, France; Mondor Amyloidosis Network, Créteil, France; Department of Cardiology, AP-HP, Henri-Mondor Teaching Hospital, Créteil, France; INSERM U955, GRC Amyloid Research Institute, Créteil, France; DHU ATVB, Créteil, France; INSERM Clinical Investigation Center 006, Créteil, France.

Objectives:
The aim of this study was to compare left ventricular longitudinal strain (LS) evaluated by 2-dimensional echocardiography with cardiac magnetic resonance (CMR) in cardiac amyloidosis (CA), establish correlations between histological and imaging findings, and assess the prognostic usefulness of LS measurement and CMR.
Background:
CA is a condition with a poor prognosis due chiefly to 3 forms of amyloidosis: light-chain amyloidosis (AL), hereditary transthyretin (M-TTR), and wild-type transthyretin (WT-TTR). Two-dimensional echocardiography measurement of LS has been reported to detect early left ventricular systolic dysfunction. The pathophysiological underpinnings, regional distribution, and prognostic significance of LS in CA are unclear.
Methods:
All patients underwent echocardiography, and 53 underwent CMR. The native hearts of the 3 patients who received heart transplants were subjected to histological examination. For each of the 17 left ventricular segments in the American Heart Association model, we evaluated LS, late gadolinium enhancement (LGE) by CMR, and cardiac amyloid deposition. Univariate and multivariate analyses were performed at 6 months to identify variables associated with major adverse cardiac events (MACE).
Results:
We studied 79 patients with CA; 26 had AL, 36 M-TTR, and 17 WT-TTR. Mean LS was -10 ± 4%. Both LS and amyloid deposits showed a basal-to-apical gradient. The mean LS and number of segments with LGE were similar across the 3 CA types. LS correlated with LGE and amyloid burden (r = 0.72). LGE was seen in the 6 basal segments in all WT-TTR patients. During the median follow-up of 11 months (range 4 to 17 months), 36 (46%) patients experienced MACE. Independent predictors of MACE were apical LS (cutoff, -14.5%), N-terminal pro-B-type natriuretic peptide (cutoff, 4,000 ng/l), and New York Heart Association functional class III to IV heart failure.
Conclusions:
Basal-to-apical LS abnormalities are similar across CA types and reflect the amyloid burden. Apical LS independently predicts MACE.
Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Heart Failure II: Pathophysiology
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:22
Mitral Stenosis I: Introduction