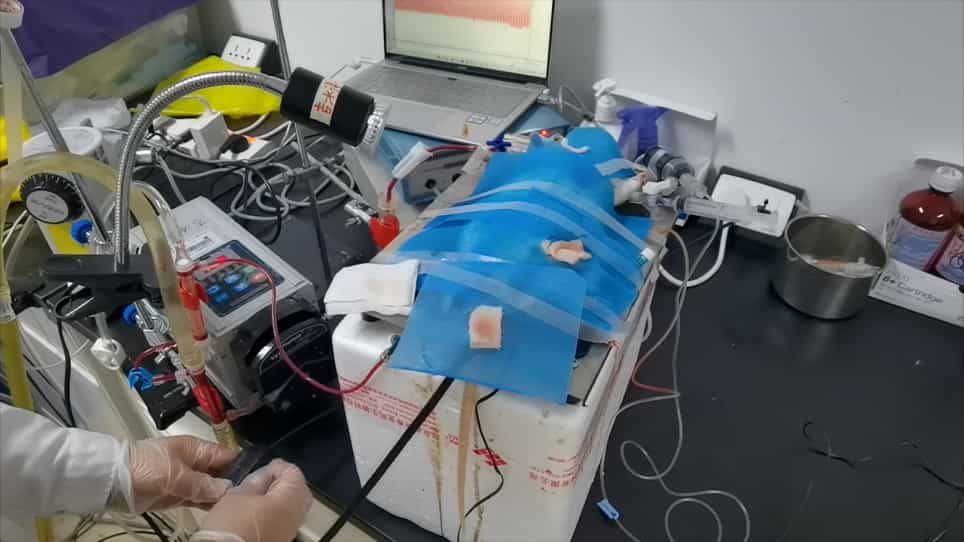
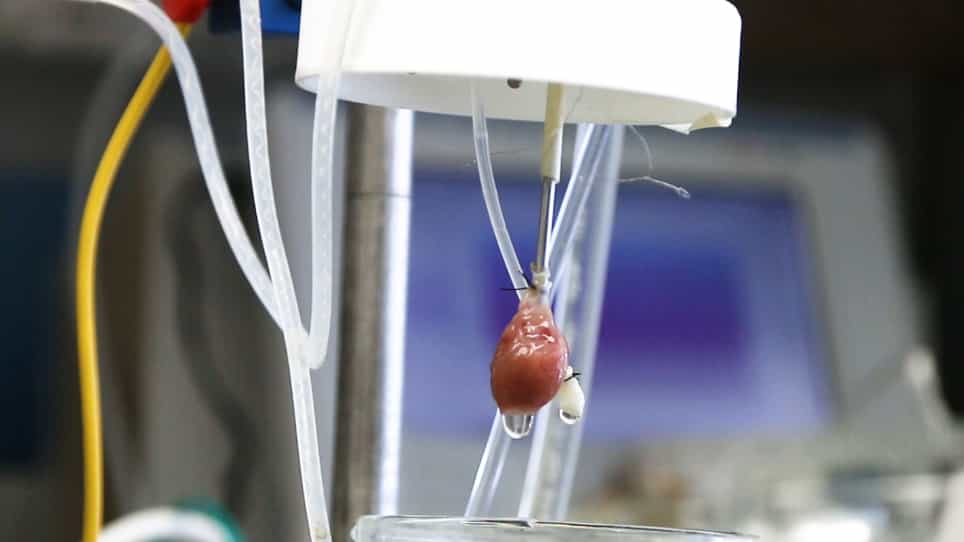
Related Experiment Video
Updated: Mar 27, 2026


In vitro Assessment of Myocardial Protection following Hypothermia-Preconditioning in a Human Cardiac Myocytes Model
Published on: October 27, 2020
Avoidance of Profound Hypothermia During Initial Reperfusion Improves the Functional Recovery of Hearts Donated After

Insights
Initial reperfusion (IR) at warmer temperatures (25°C and 35°C) significantly improves the functional recovery of hearts donated after circulatory death (DCD) during ex vivo heart perfusion (EVHP). Profound hypothermia during IR impairs myocardial function and increases injury.
Area of Science:
- Cardiology
- Transplantation Medicine
- Regenerative Medicine
Background:
- Donation after circulatory death (DCD) heart resuscitation is crucial for expanding organ availability.
- Optimizing initial reperfusion (IR) strategies is key to improving functional recovery in DCD hearts.
- The impact of IR temperature on DCD heart recovery during ex vivo heart perfusion (EVHP) requires elucidation.
Purpose of the Study:
- To determine the effect of initial reperfusion (IR) temperature on myocardial function recovery in DCD hearts during EVHP.
- To compare the functional outcomes of DCD hearts reperfused at 5°C, 25°C, and 35°C.
Main Methods:
- Eighteen pigs underwent cardiac arrest, followed by a 15-min standoff period.
- Hearts were reperfused for 3 minutes at 5°C, 25°C, or 35°C using a specific cardioplegia solution.
- Following reperfusion, hearts underwent 6 hours of normothermic EVHP with functional assessments.
Main Results:
- Coronary blood flow during IR was significantly higher at 25°C and 35°C compared to 5°C.
- Hearts reperfused at warmer temperatures exhibited reduced myocardial injury (lower troponin I levels) and better endothelial cell integrity.
- Profound hypothermia (5°C IR) impaired myocardial function recovery during EVHP, indicated by a lower cardiac index.
Conclusions:
- Avoiding profound hypothermia during initial reperfusion is critical for minimizing injury in DCD hearts.
- Warmer IR temperatures (25°C and 35°C) enhance myocardial functional recovery during EVHP.
- Optimizing IR temperature is a key strategy to improve the viability of DCD hearts for transplantation.
Abstract:
The resuscitation of hearts donated after circulatory death (DCD) is gaining widespread interest; however, the method of initial reperfusion (IR) that optimizes functional recovery has not been elucidated. We sought to determine the impact of IR temperature on the recovery of myocardial function during ex vivo heart perfusion (EVHP). Eighteen pigs were anesthetized, mechanical ventilation was discontinued, and cardiac arrest ensued. A 15-min standoff period was observed and then hearts were reperfused for 3 min at three different temperatures (5°C; N = 6, 25°C; N = 5, and 35°C; N = 7) with a normokalemic adenosine-lidocaine crystalloid cardioplegia. Hearts then underwent normothermic EVHP for 6 h during which time myocardial function was assessed in a working mode. We found that IR coronary blood flow differed among treatment groups (5°C = 483 ± 53, 25°C = 722 ± 60, 35°C = 906 ± 36 mL/min, p < 0.01). During subsequent EVHP, less myocardial injury (troponin I: 5°C = 91 ± 6, 25°C = 64 ± 16, 35°C = 57 ± 7 pg/mL/g, p = 0.04) and greater preservation of endothelial cell integrity (electron microscopy injury score: 5°C = 3.2 ± 0.5, 25°C = 1.8 ± 0.2, 35°C = 1.7 ± 0.3, p = 0.01) were evident in hearts initially reperfused at warmer temperatures. IR under profoundly hypothermic conditions impaired the recovery of myocardial function (cardiac index: 5°C = 3.9 ± 0.8, 25°C = 6.2 ± 0.4, 35°C = 6.5 ± 0.6 mL/minute/g, p = 0.03) during EVHP. We conclude that the avoidance of profound hypothermia during IR minimizes injury and improves the functional recovery of DCD hearts.