Related Experiment Video
Updated: Mar 27, 2026
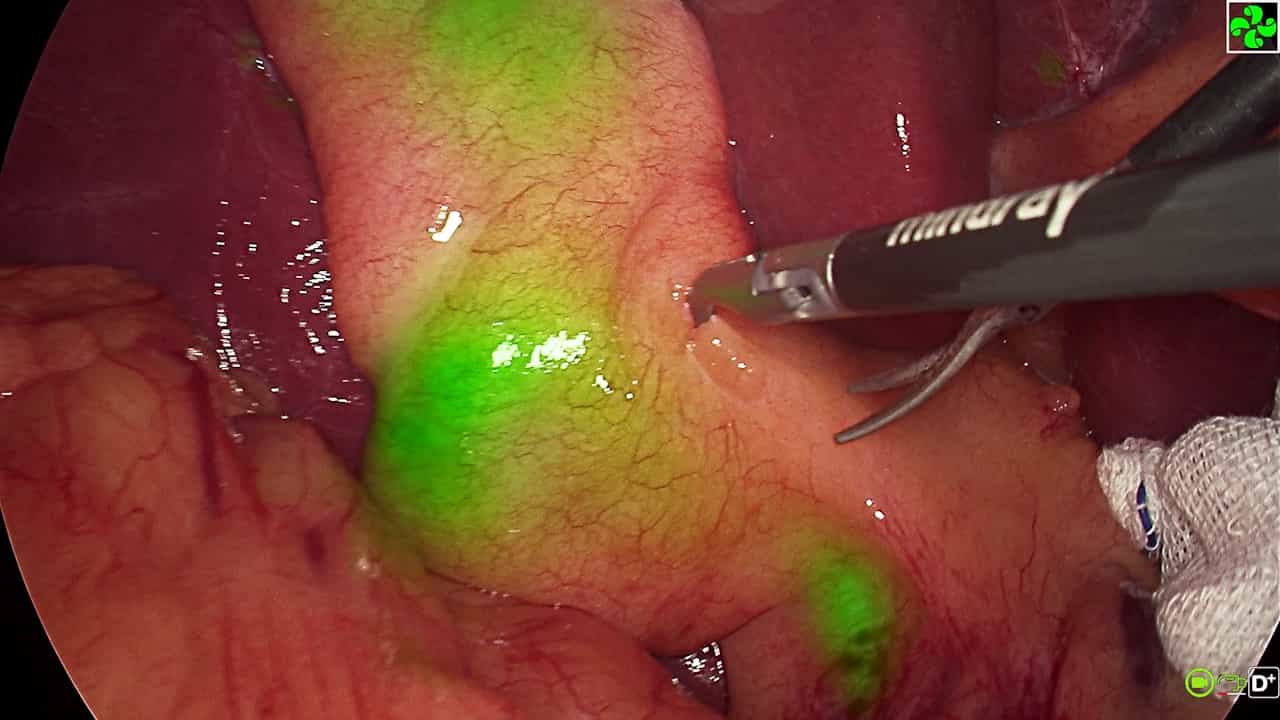

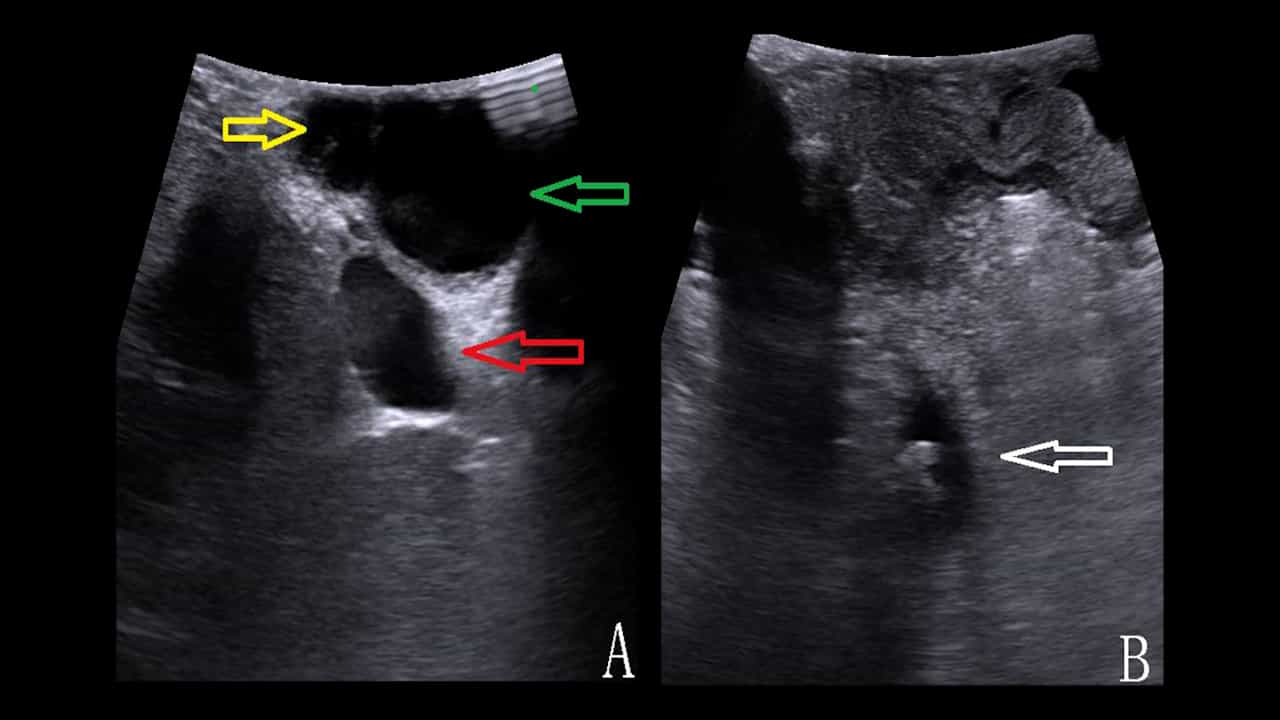
Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Exclusion criteria for assuring safety of single-incision laparoscopic cholecystectomy
Yoshikuni Kawaguchi1, Takeaki Ishizawa, Rihito Nagata
1Hepato-Biliary-Pancreatic Surgery Division, Department of Surgery, Graduate School of Medicine, The University of Tokyo.

Abstract:
Despite increasing popularity of single-incision laparoscopic cholecystectomy (SILC), indication criteria assuring safety of SILC has yet to be established. In the present study, the subjects consisted of 146 consecutive patients undergoing conventional laparoscopic cholecystectomy (CLC) or SILC. SILC was indicated after excluding patients who met following criteria: age > 75 years, obesity, operative scar, cardiopulmonary diseases, acute cholecystitis, choledocholithiasis and abnormal bile duct anatomy. Thirty-four patients were excluded from the SILC candidates (moderate/high-risk CLC group). Among the 112 potential candidates, SILC was indicated for 23 patients (21%, SILC group) and the remaining 89 patients (79%) underwent CLC (low-risk CLC group). In the SILC group, operation time was longer than in the low-risk CLC group (171 [113-286] vs. 126 [72-240] min, p < 0.01), but the periods requiring painkiller was shorter. That led to reduced length of hospital stay compared to low-risk CLC group (2 [2-4] vs. 4 [2-12] days, p < 0.01). Between the low-risk CLC and moderate/high-risk CLC group, operation time was significantly longer and amount of blood loss was larger in the latter group. No complications were encountered in the SILC group. SILC can be indicated safely as far as appropriate criteria is adopted for excluding patients in whom complicated laparoscopic procedures are needed.