Regional Heterogeneity of Chronic Obstructive Pulmonary Disease Phenotypes: Pulmonary (3)He Magnetic Resonance Imaging and Computed Tomography
Related Experiment Video
Updated: Mar 26, 2026
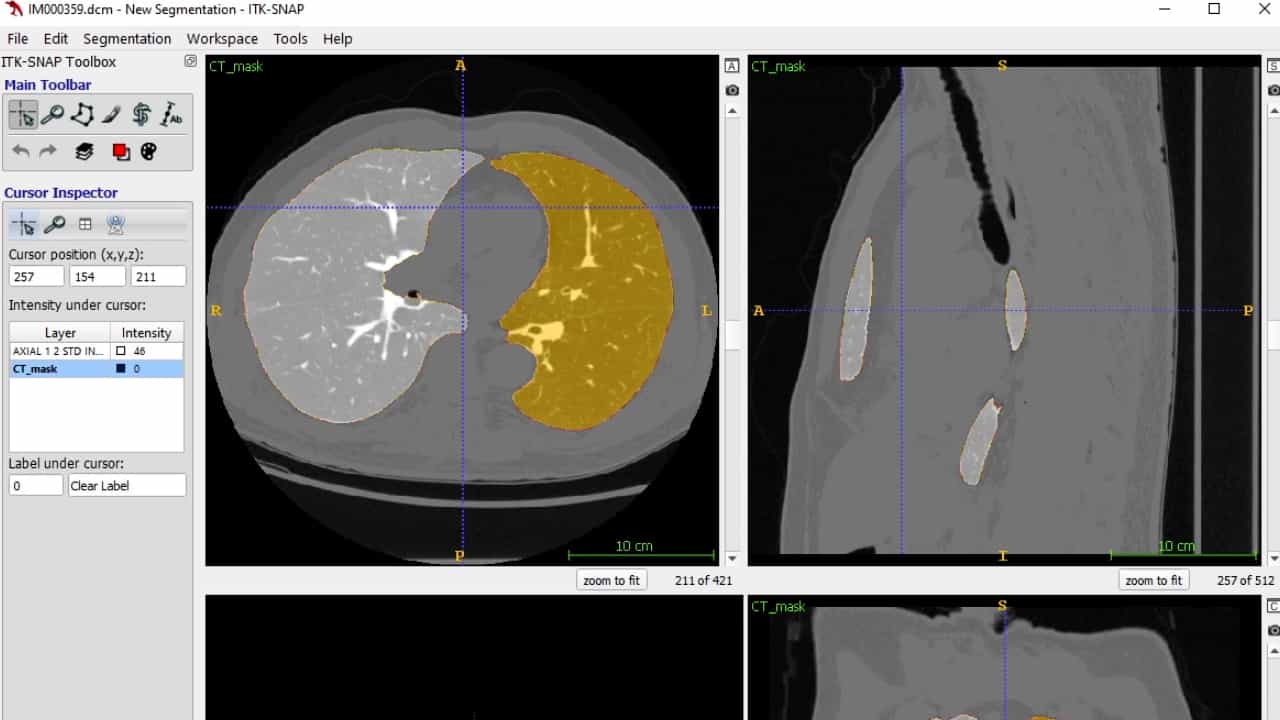
Multi-modal Pulmonary Imaging: Using Complementary Information from CT and Hyperpolarized 129Xe MRI to Evaluate Lung Structure-Function
Published on: April 12, 2024
Damien Pike1,2, Miranda Kirby3, Rachel L Eddy1,2
1a Robarts Research Institute, The University of Western Ontario , London , Canada.

Abstract:
Pulmonary ventilation may be visualized and measured using hyperpolarized (3)He magnetic resonance imaging (MRI) while emphysema and its distribution can be quantified using thoracic computed tomography (CT). Our objective was to phenotype ex-smokers with COPD based on the apical-to-basal distribution of ventilation abnormalities and emphysema to better understand how these phenotypes change regionally as COPD progresses. We evaluated 100 COPD ex-smokers who provided written informed consent and underwent spirometry, CT and (3)He MRI. (3)He MRI ventilation imaging was used to quantify the ventilation defect percent (VDP) for whole-lung and individual lung lobes. Regional VDP was used to generate the apical-lung (AL)-to-basal-lung (BL) difference (ΔVDP); a positive ΔVDP indicated AL-predominant and negative ΔVDP indicated BL-predominant ventilation defects. Emphysema was quantified using the relative-area-of-the-lung ≤-950HU (RA950) of the CT density histogram for whole-lung and individual lung lobes. The AL-to-BL RA950 difference (ΔRA950) was generated with a positive ΔRA950 indicating AL-predominant emphysema and a negative ΔRA950 indicating BL-predominant emphysema. Seventy-two ex-smokers reported BL-predominant MRI ventilation defects and 71 reported AL-predominant CT emphysema. BL-predominant ventilation defects (AL/BL: GOLD I = 18%/82%, GOLD II = 24%/76%) and AL-predominant emphysema (AL/BL: GOLD I = 84%/16%, GOLD II = 72%/28%) were the major phenotypes in mild-moderate COPD. In severe COPD there was a more uniform distribution for ventilation defects (AL/BL: GOLD III = 40%/60%, GOLD IV = 43%/57%) and emphysema (AL/BL: GOLD III = 64%/36%, GOLD IV = 43%/57%). Basal-lung ventilation defects predominated in mild-moderate GOLD grades, and a more homogeneous distribution of ventilation defects was observed in more advanced grade COPD; these differences suggest that over time, regional ventilation abnormalities become more homogenously distributed during disease progression.

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction