Related Experiment Video
Updated: Mar 26, 2026
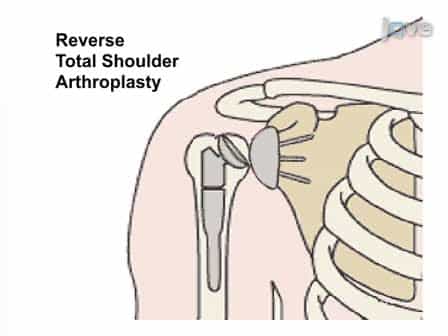
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
The Reduction in Stability From Combined Humeral Head and Glenoid Bony Defects Is Influenced by Arm Position
Piyush Walia1, Ronak M Patel2, Lionel Gottschalk3
1Department of Biomedical Engineering, Lerner Research Institute, Cleveland Clinic, Cleveland, Ohio, USA Department of Chemical and Biomedical Engineering, Cleveland State University, Cleveland, Ohio, USA Department of Orthopaedic Surgery, Cleveland Clinic, Cleveland, Ohio, USA.

Background:
Combined defects of the glenoid and humeral head are often a cause for recurrent shoulder instability.
Purpose/Hypothesis:
The aim of this study was to evaluate the influence of combined bony lesions on shoulder instability through varying glenohumeral positions. The hypothesis was that instability due to combined defects would be magnified with increasing abduction and external rotation.
Study Design:
Controlled laboratory study.
Methods:
Eighteen cadaveric shoulders were tested. Experiments were performed at combinations of glenohumeral abduction angles of 20°, 40°, and 60° and external rotations of 0°, 40°, and 80°. The various glenoid defect sizes created were 10%, 20%, and 30% of the glenoid width. Four humeral head defects were created based on humeral head diameter (6%, 19%, 31%, and 44%). Each experiment consisted of translating the glenoid in a posterior direction to simulate an anterior dislocation under a 50-N load. The instability was measured as a percentage of intact translation (ie, loss in translational distance normalized to the no-defect condition).
Results:
At 20° of abduction, instability increased from 100% to 85%, 70%, and 43% with increasing glenoid defect sizes of 10%, 20% and 30%, respectively, with a 6% humeral head defect. However, at a functional arm position of apprehension, these values were significantly decreased (P < .05) for humeral head defect sizes of 19%, 31%, and 44%, with translation values of 49%, 27%, and 2%, respectively.
Conclusion:
A humeral defect leads to rotational instability with the arm rotated into a functional position rather than a resting position. However, a significant glenoid defect can lead to loss of translation independent of changes in arm position. Combined defects as large as 44% of humeral head and 20% glenoid did not show instability at 20° of abduction and neutral position; however, defects as small as 19% humeral defect and 10% glenoid defect led to significant instability in the position of apprehension.
Clinical Relevance:
Instability at lower levels of abduction and external rotation clinically indicates larger bony defects and may need to be directly addressed, depending on the patient's age and function.
Related Concept Videos
 01:19
Bones of the Upper Limb: Humerus
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:27
Support Reactions in Three Dimensions
Ball and Socket Joint is one of the supports allowing free rotation about any axis. This freedom of rotation is...
 01:15
Bones of the Upper Limb: Ulna