Related Experiment Video
Updated: Mar 26, 2026
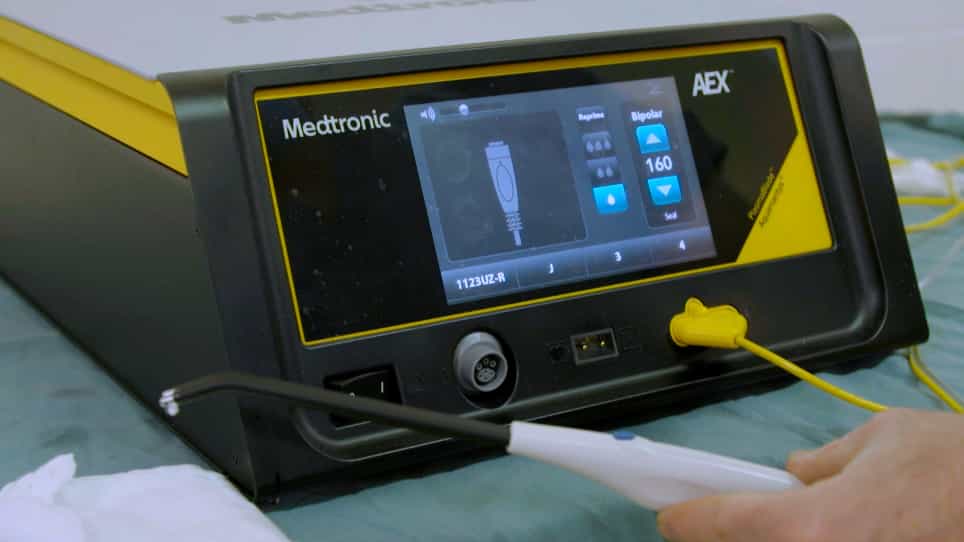
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
[Management of bleeding and infections in the context of visceral surgery]
D Böckler1, A Hyhlik-Dürr2, M Hakimi2
1Klinik für Gefäßchirurgie und Endovaskuläre Chirurgie, Universitätsklinikum Heidelberg, Im Neuenheimer Feld 110, 69120, Heidelberg, Deutschland. dittmar.boeckler@med.uni-heidelberg.de.

Abstract:
Bleeding and vascular infections are serious potential complications during abdominal general surgery. The management of bleeding depends on the extent and localization and can range from the application of hemostatics to vascular sutures, interpositioning and ligatures. The use of prosthetic biomaterials implanted endoluminally or during open reconstruction permits palliation of potentially fatal conditions. The overall incidence of infections involving vascular prostheses is relatively low because of routine antibiotic prophylaxis prior to surgery, refinements in sterilization and packaging of devices and careful adherence to aseptic procedural and surgical techniques. When infections occur detection and definitive therapy of the vascular prosthesis are often delayed and the management is complex and tedious. Infections involving vascular prostheses are difficult to eradicate and in general, surgical therapy is required often coupled with excision of the prosthesis. Keys to success include accurate diagnostics to identify the organism and extent of graft infections, specific long-term antibiotic therapy and well-planned surgical interventions to excise and replace the infected graft and sterilize the local tissue. Regardless of the technique used to eradicate graft infections, success is measured by patient survival, freedom from recurrent infection and patency of revascularization. Even when treatment is successful, the morbidity associated with vascular graft infections is considerable. Aortoenteric fistulas (AEF) are a rare (incidence < 1.5 %) but often fatal complication. Primary diagnosis of AEF remains difficult. Computed tomography (CT) and fluorodeoxyglucose positron emission tomography CT (FDG-PET-CT) are the diagnostic tools of choice. Therapy consists of an urgent individualized interdisciplinary surgical approach with primary axillofemoral bypass and secondary prosthesis explantation or in situ replacement and subsequent bowel resection. Endovascular aortic repair (EVAR) is reserved for primary aortoenteric fistulas in patients with no signs of infection or in emergency cases as a bridging method.
More Related Videos
 04:57
Author Spotlight: Advancing Spectral Characterization of Physiological and Malperfused Tissues
Published on: July 5, 2024
 05:22
Intraoperative Strategy under Complex Vascular Adhesion for Laparoscopic Radical Resection of Bismuth-Corlette Type IIIb Perihilar Cholangiocarcinoma
Published on: February 13, 2026
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:22
Aneurysm IV: Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:30
Venous Thrombosis IV: Nursing Management
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease