Related Experiment Video
Updated: Mar 26, 2026
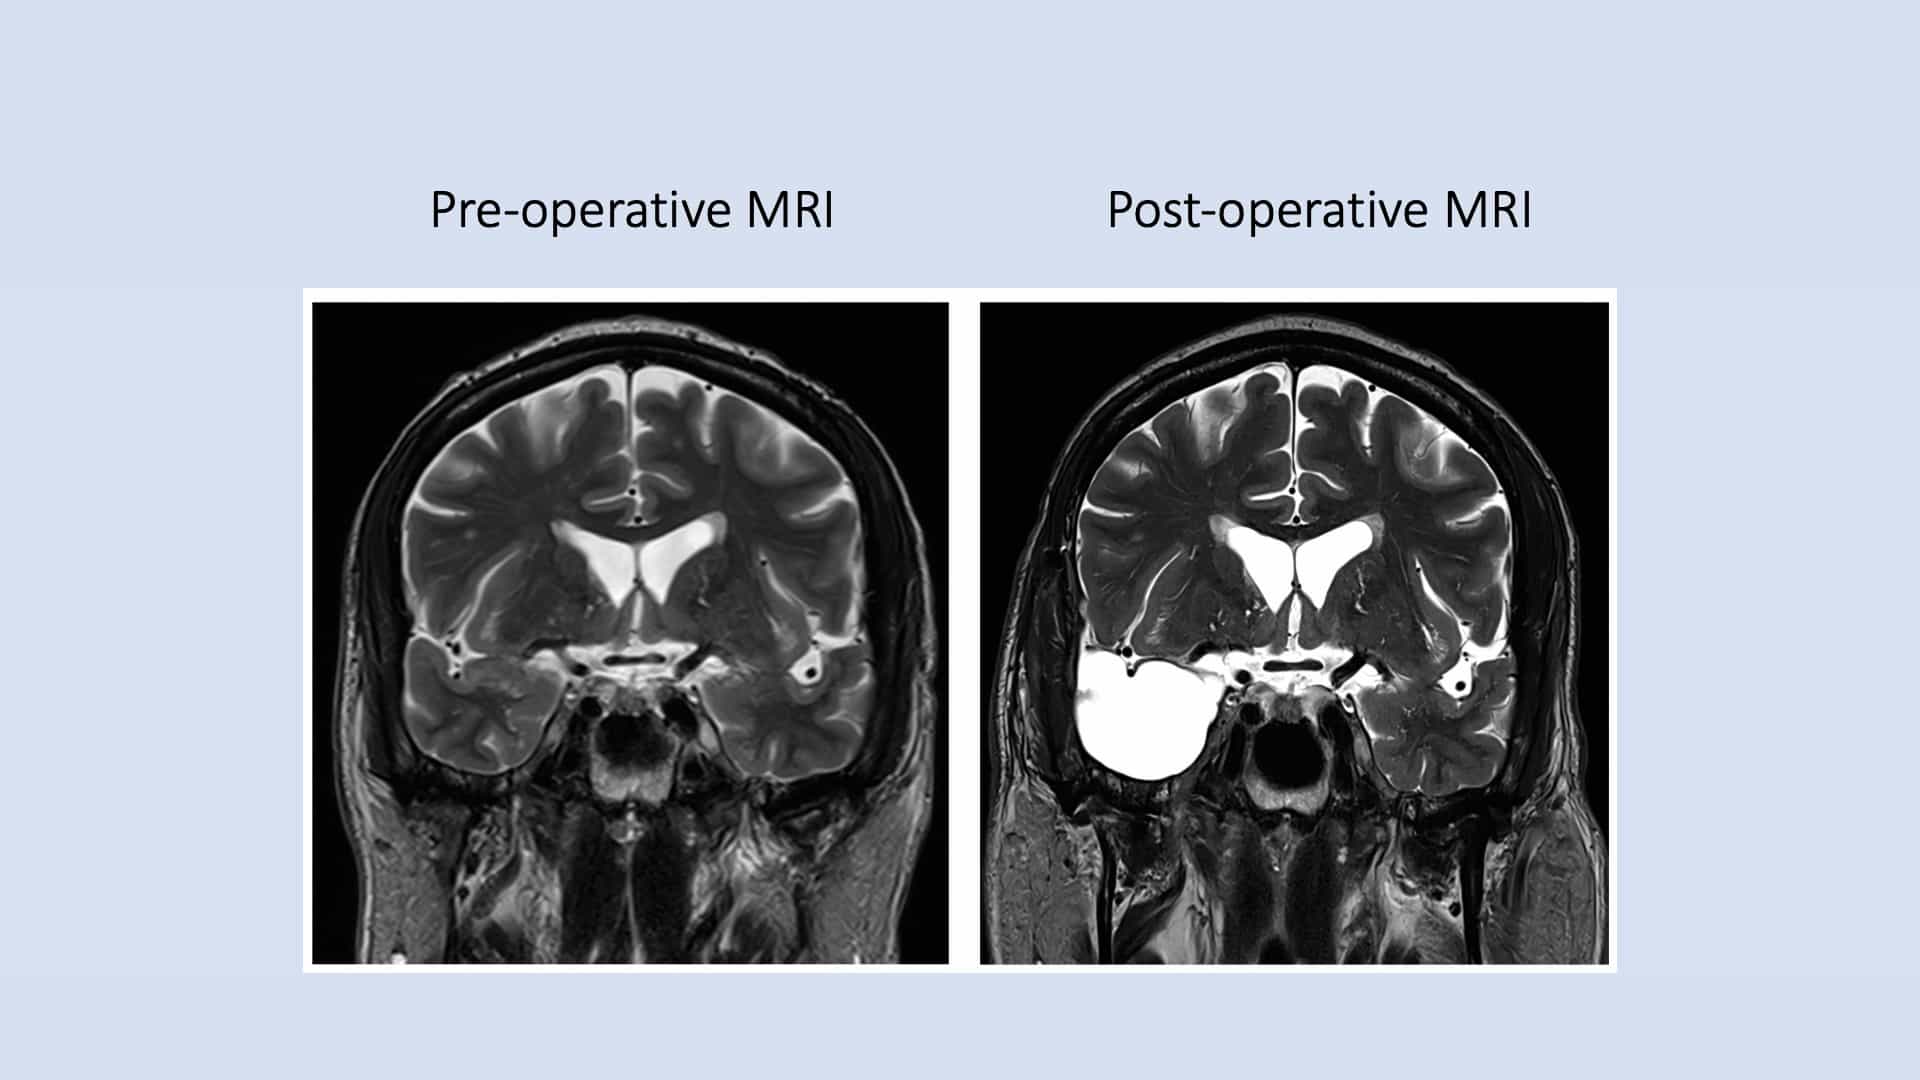
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Hippocampal internal architecture and postoperative seizure outcome in temporal lobe epilepsy due to hippocampal
Samia Elkommos1, Bernd Weber2, Pitt Niehusmann3
1Department of Molecular and Clinical Pharmacology, Institute of Translational Medicine, University of Liverpool, UK.

Purpose:
Semi-quantitative analysis of hippocampal internal architecture (HIA) on MRI has been shown to be a reliable predictor of the side of seizure onset in patients with temporal lobe epilepsy (TLE). In the present study, we investigated the relationship between postoperative seizure outcome and preoperative semi-quantitative measures of HIA.
Methods:
We determined HIA on high in-plane resolution preoperative T2 short tau inversion recovery MR images in 79 patients with presumed unilateral mesial TLE (mTLE) due to hippocampal sclerosis (HS) who underwent amygdalohippocampectomy and postoperative follow up. HIA was investigated with respect to postoperative seizure freedom, neuronal density determined from resected hippocampal specimens, and conventionally acquired hippocampal volume.
Results:
HIA ratings were significantly related to some neuropathological features of the resected hippocampus (e.g. neuronal density of selective CA regions, Wyler grades), and bilaterally with preoperative hippocampal volume. However, there were no significant differences in HIA ratings of the to-be-resected or contralateral hippocampus between patients rendered seizure free (ILAE 1) compared to those continuing to experience seizures (ILAE 2-5).
Conclusions:
This work indicates that semi-quantitative assessment of HIA on high-resolution MRI provides a surrogate marker of underlying histopathology, but cannot prospectively distinguish between patients who will continue to experience postoperative seizures and those who will be rendered seizure free. The predictive power of HIA for postoperative seizure outcome in non-lesional patients with TLE should be explored.


