Related Experiment Video
Updated: Mar 26, 2026


Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
Buried bumper syndrome: A complication of percutaneous endoscopic gastrostomy
Jiri Cyrany1, Stanislav Rejchrt1, Marcela Kopacova1
1Jiri Cyrany, Stanislav Rejchrt, Marcela Kopacova, Jan Bures, 2 Department of Internal Medicine - Gastroenterology, University Hospital Hradec Kralove, 50005 Hradec Kralove, Czech Republic.

Abstract:
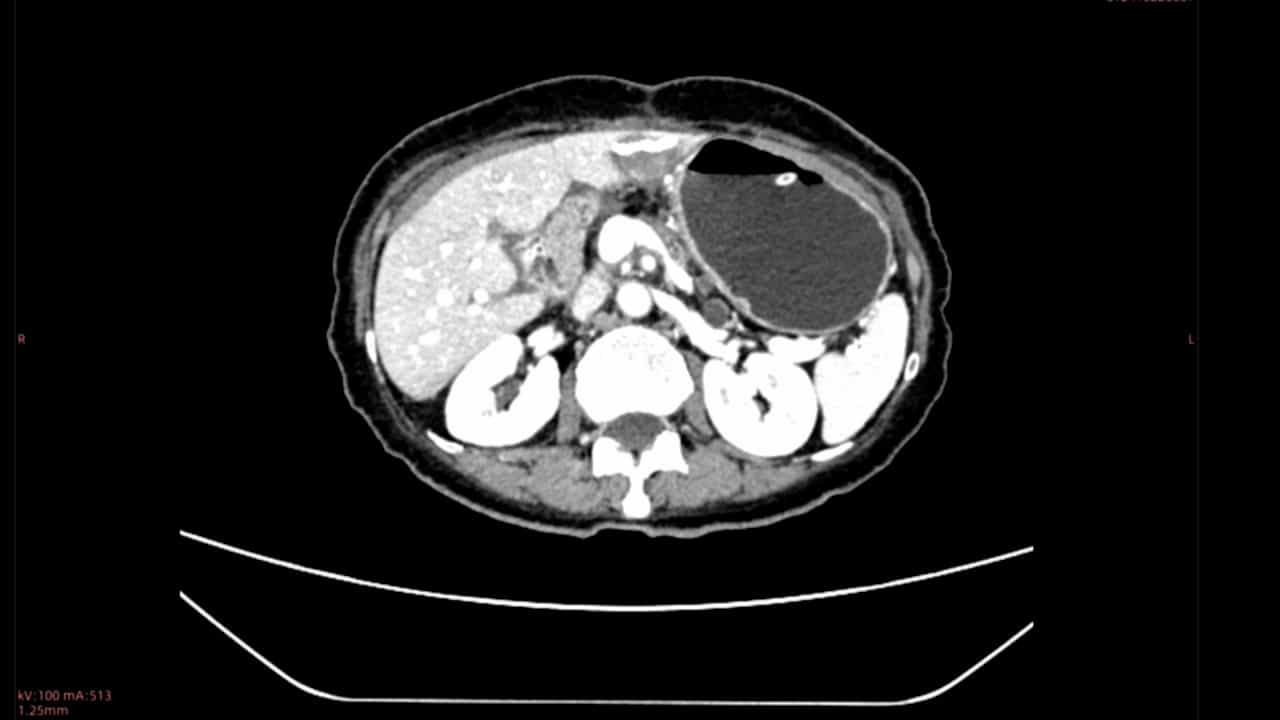
Percutaneous endoscopic gastrostomy (PEG) is a widely used method of nutrition delivery for patients with long-term insufficiency of oral intake. The PEG complication rate varies from 0.4% to 22.5% of cases, with minor complications being three times more frequent. Buried bumper syndrome (BBS) is a severe complication of this method, in which the internal fixation device migrates alongside the tract of the stoma outside the stomach. Excessive compression of tissue between the external and internal fixation device of the gastrostomy tube is considered the main etiological factor leading to BBS. Incidence of BBS is estimated at around 1% (0.3%-2.4%). Inability to insert, loss of patency and leakage around the PEG tube are considered to be a typical symptomatic triad. Gastroscopy is indicated in all cases in which BBS is suspected. The depth of disc migration in relation to the lamina muscularis propria of the stomach is critical for further therapy and can be estimated by endoscopic or transabdominal ultrasound. BBS can be complicated by gastrointestinal bleeding, perforation, peritonitis, intra-abdominal and abdominal wall abscesses, or phlegmon, and these complications can lead to fatal outcomes. The most important preventive measure is adequate positioning of the external bolster. A conservative approach should be applied only in patients with high operative risk and dismal prognosis. Choice of the method of release is based on the type of the PEG set and depth of disc migration. A disc retained inside the stomach and completely covered by the overgrowing tissue can be released using some type of endoscopic dissection technique (needle knife, argon plasma coagulation, or papillotome through the cannula). Proper patient selection and dissection of the overgrowing tissue are the major determinants for successful endoscopic therapy. A disc localized out of the stomach (lamina muscularis propria) should be treated by a surgeon.
Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: