Related Experiment Video
Updated: Mar 26, 2026


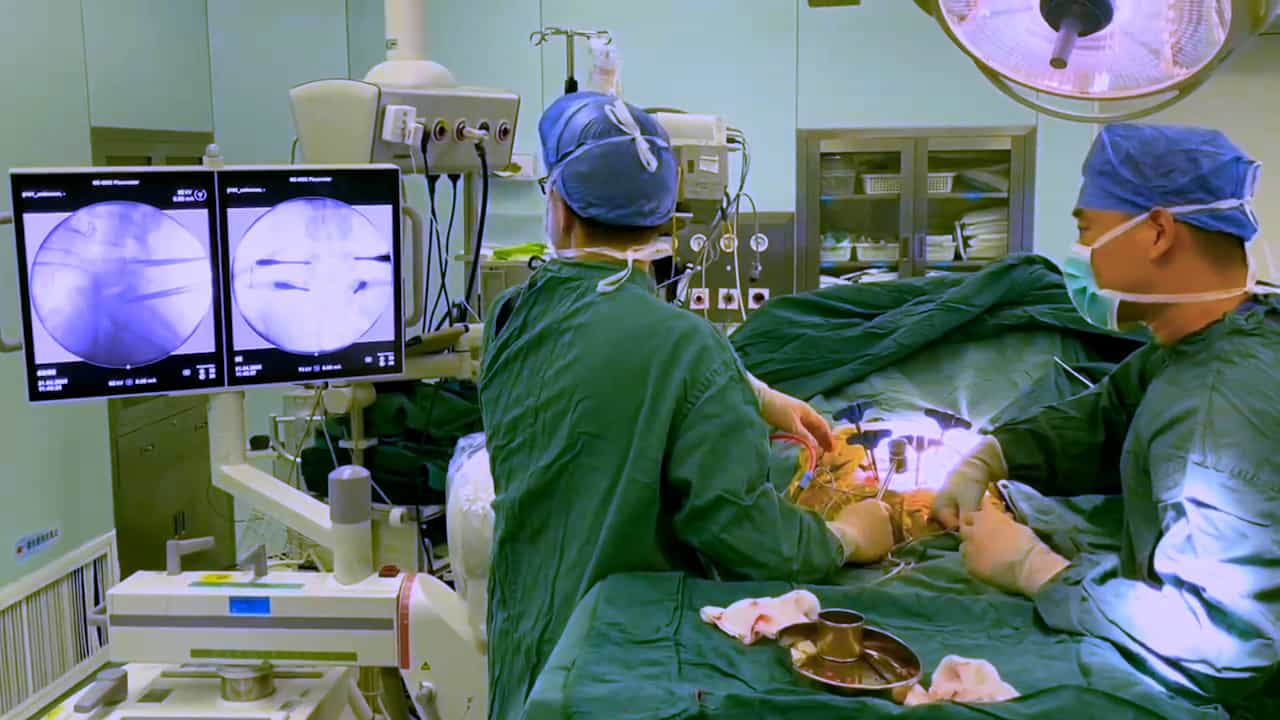
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Operative Timing and Management of Spinal Injuries in Multiply Injured Patients
Christian Hierholzer1, Volker Bühren, Alexander Woltmann2
1BG Trauma Center Murnau, Professor-Küntscher-Strasse 8, 82418, Murnau, Germany. chhierholzer@bgu-murnau.de.

Abstract:
Spinal injuries occurring in polytrauma patients are caused by high impact trauma. Due to high velocity mechanism, trauma of the vertebral column may be accompanied by injuries of adjacent body cavities such as thorax, abdomen, and pelvis. Neurologic examination is mandatory and has to be documented preferably using the ASIA/IMSOP-classification. Clinical symptoms may point towards spinal injury. However, absence of clinical symptoms is not sufficient to rule out spinal injuries. Two diagnostic pathways may be followed to assess the spine: (1) Conventional X-ray diagnostics of the entire spine followed by selective CT scanning of suspected lesions and CT scanning of the upper cervical spine region C0-C3 in unconscious patients. (2) Whole body polytrauma-multislice-spiral-CT scanning from head to pelvis without conventional Xray playing the key role in the algorithm of modern ER management. In this study, 287 polytrauma patients with associated spinal injuries were analyzed prospectively from a cohort group of 731 polytrauma patients treated from 2002 to 2004 in our institution. Indications for surgery include neurologic deficit, instability, as well as malalignment and dislocation. In polytraumatized patients, indication for primary surgery is given in complex spinal injuries with associated vascular, neurologic, or organ injuries as well as multilevel spinal fractures or unstable spinal injuries. In patients with unstable spinal injuries cardio-pulmonary instability and life threatening intracranial pressure are contra - indications for immediate spinal surgery. On the day of injury ventral spondylodesis of unstable cervical spine fractures of C3-C7 and dorsal spondylodesis of unstable thoraco-lumbar fractures using internal fixator are the standard procedures. Polytrauma patients benefit from early stabilization of spinal fractures including reduction of ventilation and ICU treatment, pneumonia rate, general complications, as well as hospital stay. However, it is controversial if mortality rate and neurologic outcome are affected by the time point of operative stabilization.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:22
Aneurysm IV: Nursing Management