Related Experiment Video
Updated: Mar 26, 2026
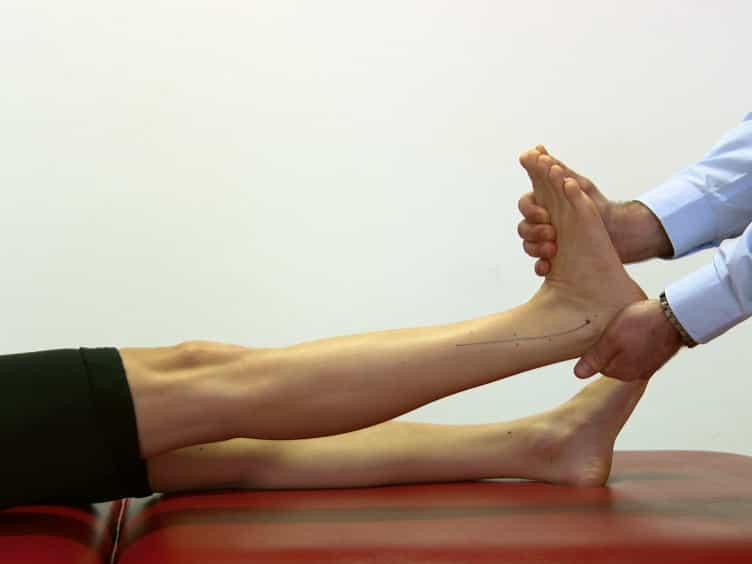
Diagnosis of Musculus Gastrocnemius Tightness - Key Factors for the Clinical Examination
Published on: July 7, 2016
The relationship of foot and ankle mobility to the frontal plane projection angle in asymptomatic adults
Narelle Wyndow1, Amy De Jong1, Krystal Rial1
1Division of Physiotherapy, School of Health & Rehabilitation Sciences, The University of Queensland, St. Lucia Queensland, 4072 Australia.

Background:
The frontal plane projection angle (FPPA) is frequently used as a measure of dynamic knee valgus during functional tasks, such as the single leg squat. Increased dynamic knee valgus is observed in people with knee pathologies including patellofemoral pain and anterior cruciate injury. As the foot is the primary interface with the support surface, foot and ankle mobility may affect the FPPA. This study investigated the relationship between foot and ankle mobility and the FPPA in asymptomatic adults.
Methods:
Thirty healthy people (aged 18-50 years) performed 5 single leg squats. Peak FPPA and FPPA excursion were determined from digital video recordings. Foot mobility was quantified as the difference in dorsal midfoot height or midfoot width, between non-weightbearing and bilateral weightbearing positions. Ankle joint dorsiflexion range was measured as the maximum distance in centimetres between the longest toe and the wall during a knee-to-wall lunge. Linear regressions with generalised estimating equations were used to examine relationships between variables.
Results:
Higher midfoot width mobility was associated with greater peak FPPA (β 0.90, p < 0.001, odds ratio [OR] 2.5), and FPPA excursion (β 0.67, p < 0.001, OR 1.9). Lower midfoot height mobility was associated with greater peak FPPA (β 0.37, p = 0.030, OR 1.4) and FPPA excursion (β 0.30, p = 0.020, OR 1.3). Lower ankle joint dorsiflexion was also associated with greater peak FPPA (β 0.61, p = 0.008, OR 1.8) and greater FPPA excursion (β 0.56, p < 0.001, OR 1.7).
Conclusions:
Foot and ankle mobility was significantly related to the FPPA during the single leg squat in healthy individuals. Specifically, higher midfoot width mobility, or lower ankle joint dorsiflexion range and midfoot height mobility, were associated with a greater FPPA. These foot mobility factors should be considered in the clinical management of knee-related disorders that are associated with a high FPPA.
More Related Videos
Related Concept Videos
 01:10
Ankle Joint
 00:51
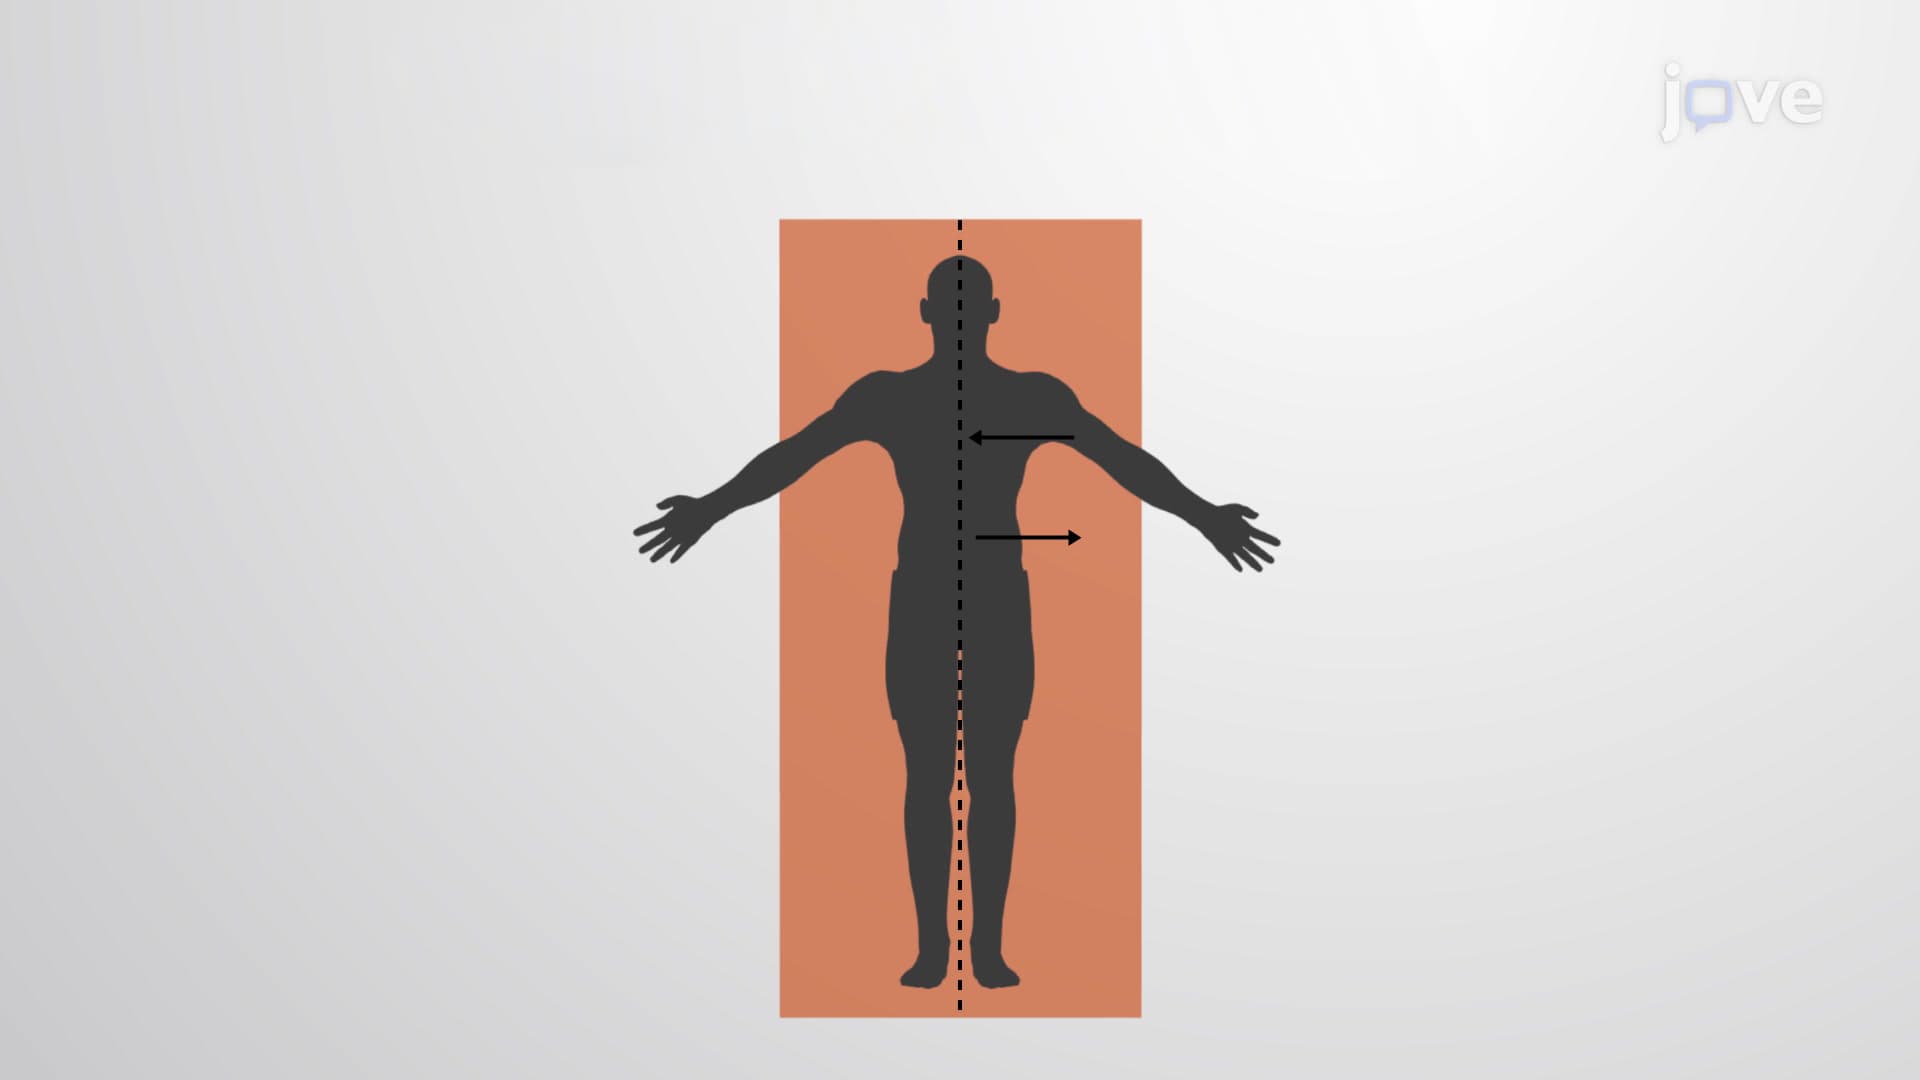
Anatomical Movements
Here are some common anatomical movements:
Flexion and extension motions are in the sagittal (anterior–posterior) plane of motion. These movements take place at the shoulder, hip, elbow, knee, wrist,...
 01:09
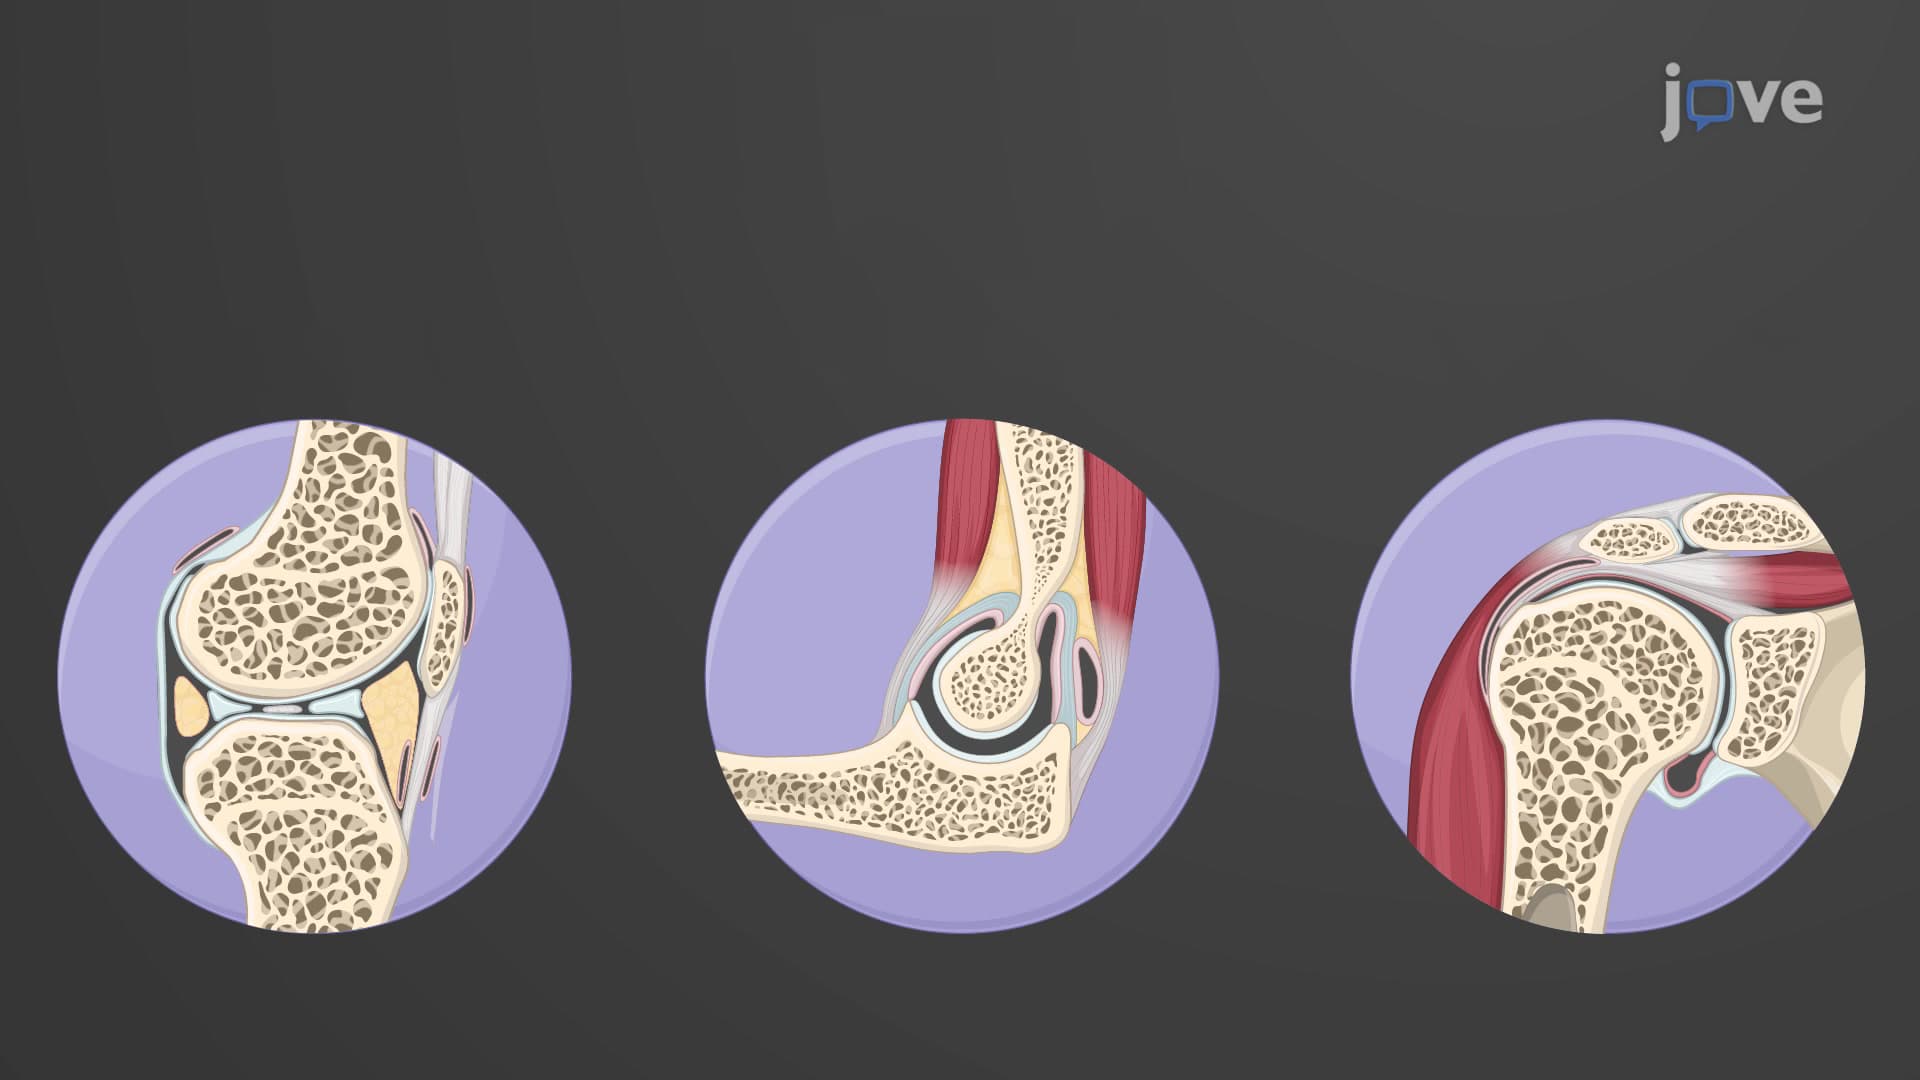
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...