Related Experiment Video
Updated: Mar 26, 2026


Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Efficacy of Low-Dose Chlorthalidone and Hydrochlorothiazide as Assessed by 24-h Ambulatory Blood Pressure Monitoring
Anil K Pareek1, Franz H Messerli2, Nitin B Chandurkar3
1Medical Affairs and Clinical Research, Ipca Laboratories Limited, Mumbai, India.

Background:
Thiazide and thiazide-like diuretic agents are being increasingly used at lower doses. Hydrochlorothiazide (HCTZ) in the 12.5-mg dose remains the most commonly prescribed antihypertensive agent in the United States.
Objectives:
This study compared chlorthalidone, 6.25 mg daily, with HCTZ, 12.5 mg daily, by 24-h ambulatory blood pressure (ABP) monitoring and evaluated efficacy. Because HCTZ has been perceived as a short-acting drug, a third comparison with an extended-release formulation (HCTZ-controlled release [CR]) was added.
Methods:
This 12-week comparative, double-blind, outpatient study randomized 54 patients with stage 1 hypertension to receive either chlorthalidone, 6.25 mg, (n = 16); HCTZ 12.5 mg (n = 18); or HCTZ-CR 12.5 mg (n = 20). ABP monitoring was performed at baseline and after 4 and 12 weeks of therapy.
Results:
All 3 treatments significantly (p < 0.01) lowered office BP at weeks 4 and 12 from baseline. At weeks 4 and 12, significant reductions in systolic and diastolic 24-h ambulatory and nighttime BP (p < 0.01) were observed with chlorthalidone but not with HCTZ. At weeks 4 (p = 0.015) and 12 (p = 0.020), nighttime systolic ABP was significantly lower in the chlorthalidone group than in the the HCTZ group. With HCTZ therapy, sustained hypertension was converted into masked hypertension. In contrast to the HCTZ group, the HCTZ-CR group also showed a significant (p < 0.01) reduction in 24-h ABP. All 3 treatments were generally safe and well tolerated.
Conclusions:
Treatment with low-dose chlorthalidone, 6.25 mg daily, significantly reduced mean 24-h ABP as well as daytime and nighttime BP. Due to its short duration of action, no significant 24-h ABP reduction was seen with HCTZ, 12.5 mg daily, which merely converted sustained hypertension into masked hypertension. Thus, low-dose chlorthalidone, 6.25 mg, could be used as monotherapy for treatment of essential hypertension, whereas low-dose HCTZ monotherapy is not an appropriate antihypertensive drug. (Comparative Evaluation of Safety and Efficacy of Hydrochlorothiazide CR with Hydrochlorothiazide and Chlorthalidone in Patients With Stage I Essential Hypertension; CTRI/2013/07/003793).


Related Concept Videos
 01:15
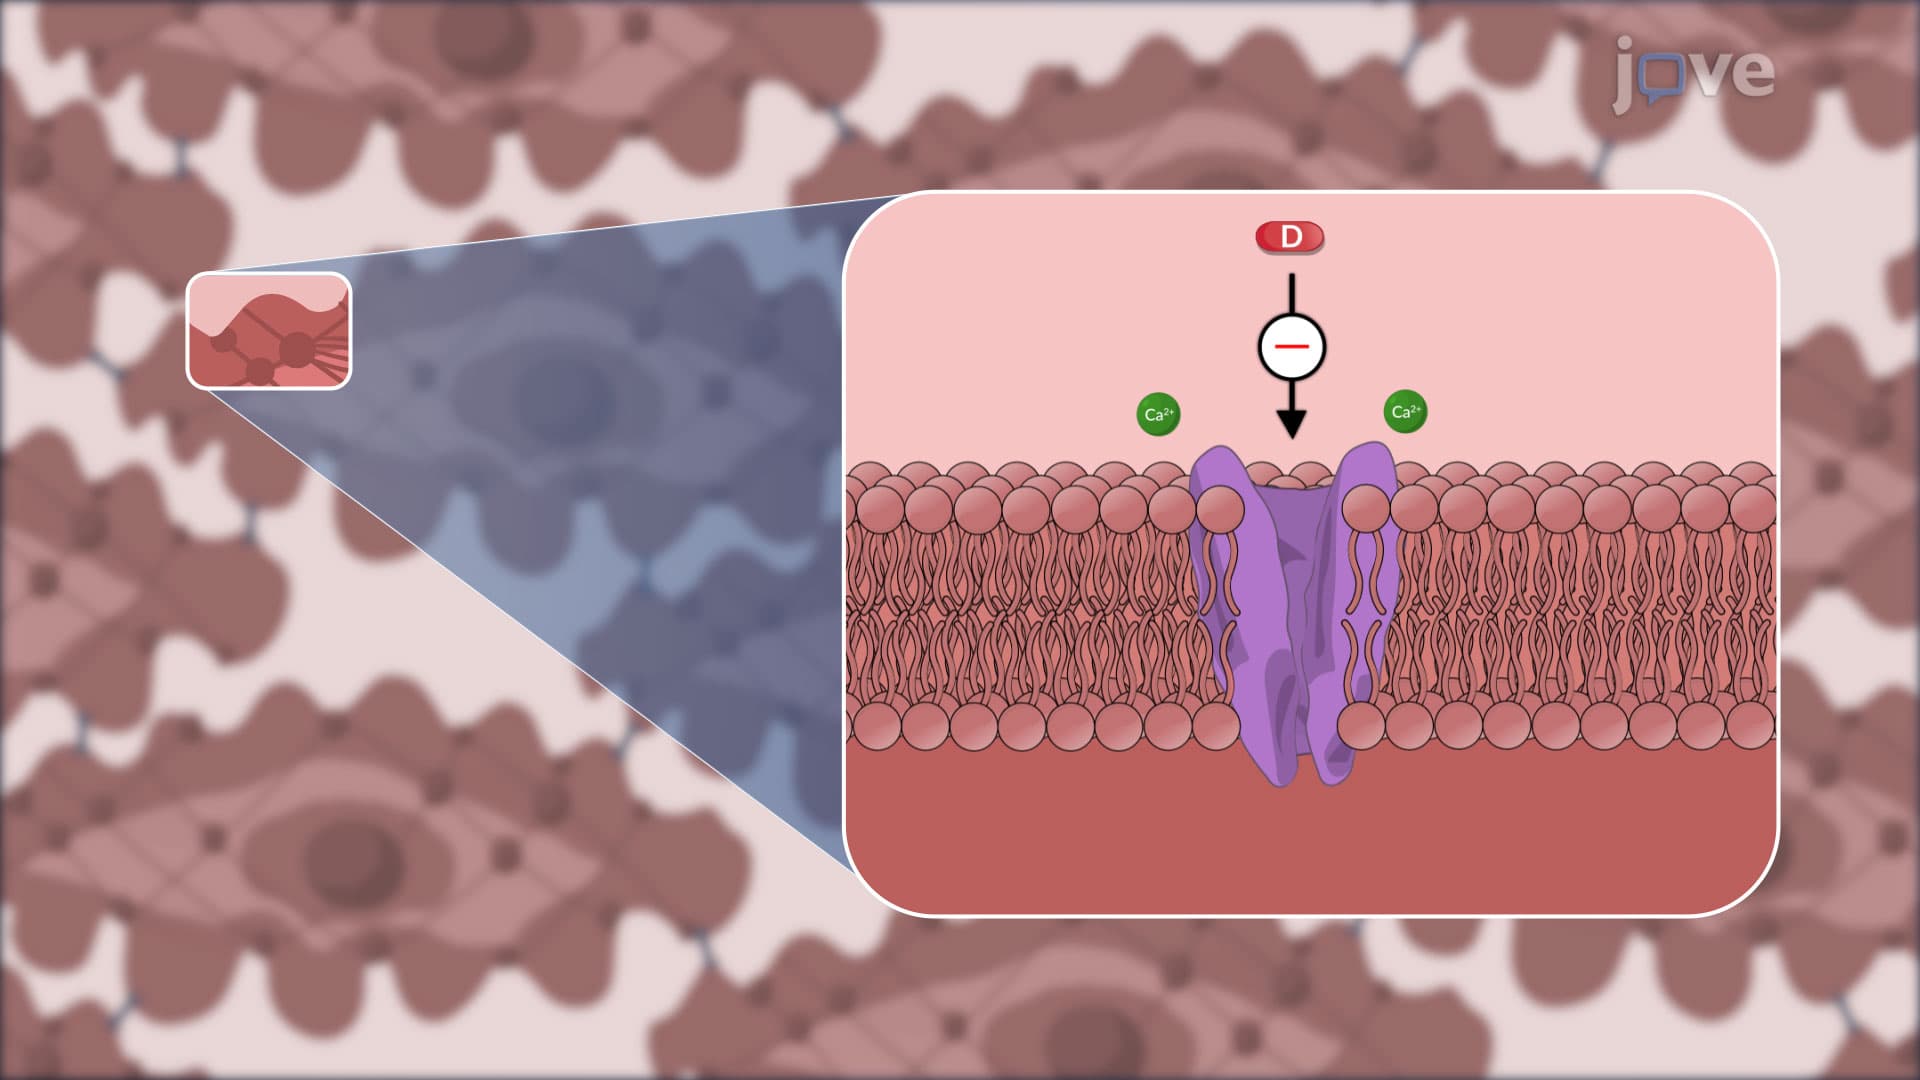
Antihypertensive Drugs: Thiazide-Class Diuretics
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:16
Antihypertensive Drugs: Action of Diuretics
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:15
Chronopharmacokinetics: Circadian Rhythms and Influence on Drug Response
The time of drug administration is an important factor to consider, as it can influence the toxic dose of a drug. For example, a study conducted by Prins et al. in 1997 examined the effects of the timing of...